CMS Issues Medicaid Guidance on Change Healthcare Hack

CMS

From the NAHC News Desk,

March 19, 2024

On March 15th, the Centers for Medicare & Medicaid Services (CMS) issued a Center Informational Bulletin (CIB) that provides guidance and flexibilities to mitigate the impacts on providers resulting from the Change Healthcare Hack. In the guidance, CMS advises state Medicaid agencies that certain requirements will not be enforced, until June 30th, to enable ongoing funds to flow to providers and to prevent disruption of access to Medicaid services, prevent associated negative health outcomes, and avoid solvency issues for providers.

The most important component of the guidance is the ability for states to make interim payments to providers to avoid operational disruptions. Federal law and regulation does not allow for “advance payments” in Medicaid fee-for-service systems, despite their availability in Medicaid managed care environments; however, states can make interim payments to providers subject to reconciliation with actual services delivered.

CMS stresses that such interim payments are not advanced payments or prepayments prior to services furnished by providers, but rather are payments for services furnished that are subject to final reconciliation once the state has access to individual claims data currently inaccessible due to the cybersecurity incident.

The flexibilities CMS discusses in the guidance include:

  • Modifying required timelines for public notice, public process, and Tribal consultation and to obtain an earlier effective date for certain kinds of SPAs than would otherwise be possible;
  • Use interim payment methodologies to pay providers without current period claims data, as long they are determined via current approved payment rates, limiting the interim payments to the amount expected for each specific provider based on recent history, and reconciling the interim payments with final payments based on the actual services provided once they can be properly identified. These could be effective retroactively to the date when claims payment processing was disrupted due to the cybersecurity incident and could last until June 30, 2024;
  • Suspend beneficiary cost sharing requirements described in their state plans when necessary to avoid service disruptions for Medicaid beneficiaries for services affected by the hack;
medicaid

CMS also includes language urging Medicaid managed care plans to make prospective payments to impacted providers and reiterating that plans do not need prior CMS authority to make prospective payments to providers. CMS also indicates that plans can:

  • Suspend or modify prior authorization requirements;
  • Allow early prescription refills and/or extend the length of prescription refills;
  • Extend existing prior authorizations;
  • Suspend out-of-network requirements; and
  • Modify or update cost-sharing requirements to be consistent with any changes that are made in the Medicaid state plan.

The full guidance is available online at: https://www.medicaid.gov/sites/default/files/2024-03/cib031524.pdf.

SNF Abuses Could be Selling Point for In-Home Care Providers

Clinical

by Tim Rowan, Editor Emeritus

For as long as I can remember, Home Health and Home Care owners and advocates, including their national and state associations, have struggled to develop concrete data to prove what we all know to be true: In-home care is a great deal for payers, both public and private. Underpaying our sector in a misguided attempt to reduce costs results in paying more in the long run. Buying more in-home care translates into lower overall cost.

This is one part of the story, and we continually search for the proof our sector so desperately needs. But there is another aspect to the Home Health, Home Care advantage that must not be overlooked as we focus on payer finances.

Patient care and safetyPhoto of a rundown nursing home room

One need look no further than our post-acute care neighbor, Skilled Nursing Facilities, to understand how much better off elderly citizens are when in-home caregivers and clinicians enabled them to stay in their own homes and avoid institutionalized care. A new, peer-reviewed study titles “Profits Over Patients” was published in the online collective The Conversation. If unfamiliar, think of it as The Huffington Post for scholars and researchers.

In the exposé, investigators Sean Campbell and Charlene Harrington reveal that for-profit organizations have been infiltrated by Wall Street investors and other venture capitalists, seeking quick turnarounds and handsome profits. Founders and other SNF owners gladly accept generous offers to be acquired or partner with investors who immediately begin to impose cost-cutting measures and maximize profits. The probe, which paired an academic expert with an investigative reporter, discovered a number of startling findings:

“The investigation revealed an industry that places a premium on cost cutting and big profits, with low staffing and poor quality, often to the detriment of patient well-being. Operating under weak and poorly enforced regulations with financially insignificant penalties, the for-profit sector fosters an environment where corners are frequently cut, compromising the quality of care and endangering patient health.”

Campbell and Harrington also looked at the ineffectiveness of state inspectors, who have limited ability to impose meaningful fines for violations. One startling example in the report is that of a Louisville SNF. The care was found to be “abysmal” when Kentucky inspectors filed their survey report.

“Residents wandered the halls in a facility that can house up to 250 people, yelling at each other and stealing blankets. One resident beat a roommate with a stick, causing bruising and skin tears. Another was found in bed with a broken finger and a bloody forehead gash. That person was allowed to roam and enter the beds of other residents. In another ase, there was sexual touching in the dayroom between residents, according to the [surveyor’s] report.

“Meals were served from filthy meal carts on plastic foam trays, and residents struggled to cut their food with dull plastic cutlery. Broken tiles lined showers, and a mysterious black gunk marred the floors.

“Overall, there was a critical lack of training, lack of staff, and lack of supervision.”

The report said state inspectors found 29 deficiencies, including six that put residents in immediate jeopardy of serious harm and three where actual harm was found. The fine imposed was $319,000 — more than 29 times the average for a nursing home. Payments from Medicare and Medicaid were suspended. The investors and owners chalked the fine up to a normal cost of doing business and, five months later, inspectors found six additional deficiencies “of immediate jeopardy,” the highest level.

The parent company of the Kentucky SNF, Infinity Healthcare Management, owns 58 facilities across five states. Since 2021, Infinity has been hit with nearly $10 million in fines, more than 4.5 times the national average.

Cut staff, save money, hide money

The investigation revealed an industry that places a premium on cost cutting and big profits, with low staffing and poor quality, endangering patient health. “Meanwhile,” the authors assert, “owners make the facilities look less profitable by siphoning money from the homes through byzantine networks of interconnected corporation

s. Federal regulators have neglected the problem as each year likely billions of dollars are funneled out of nursing homes through related parties and into owners’ pockets.”

The report points out that problems of this magnitude are found far less often in small, single-location facilities and in national chains and franchises. The sweet sport for abuse seems to be in the mid-range, for-profit organizations that have been taken over by far-away investors. Sadly, 72 percent of the SNF’s in this category are for-profit. “While such chains account for about 39 percent of all facilities, they operate 11 of the 15 most-fined facilities.

Relevance

A frequent message at Home Healthcare conferences in recent years has been the renewed interest in our sector from big money investors. While quick profits and the enticement of early retirement might bring Home Health and Home Care owners to the negotiating table, this exposé may be a reason to take a breath and think it through. Most of you who nurtured your company from startup to attractive acquisition target did so as much out of compassion as entrepreneurship. Would you not wonder, from your perch on the sun deck of a cruise ship, whether your legacy is being dragged in the mud and your patients and employees reduced to a Wall Street cost column?

Read the entire report here.

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com or Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

HHAeXchange Makes Leadership Changes

Vendor Watch

by Kristin Rowan, Editor

On February 21, 2024, HHAeXchange announced a change in leadership for the homecare management solutions company. Former Chief Revenue Officer Scott Schwartz was named Chief Operating Officer and new hire Lori Harrington came on board as the Senior Vice President of Product. You can read the press release from HHAeXchange here.

HHAeXchange provides management solutions for providers, MCOs, and state Medicaid agencies. The software was designed specifically for home and community-based services (HCBS) and connects state agences, MCOs, providers, and caregivers through its web-based platform. According to HHAeXchange, the personnel changes show the company’s “commitment to providing innovative solutions that some homecare industry challenges.

I had the opportunity to reach out to Scott and Lori to get, in their own words, their visions for the future of HHAeXchange and the industry.HHAeXchange

The Rowan Report: Thank you, Scott and Lori for taking some time to talk with The Rowan Report. First, congratulations to you both on your new roles. Can you each share a little about your background and career?

Scott Schwartz: For over 20 years, I’ve focused on system of record, vertical SaaS software and technology, with experience leading sales, marketing, client success and operations. I started my career as a process engineer and have held leadership positions at several SaaS companies, including as the founder and general manager of CampSite. I joined HHAeXchange in 2017 as vice president and have also served as senior vice president and chief revenue officer before stepping into my current role. As chief operating officer, my aim is to galvanize the organization around a shared vision of operational efficiency, innovative service delivery, and customer satisfaction.

Lori Harrington: I have enjoyed a career of over 20 years in healthcare with a background in product strategy and informatics. In my most recent role as vice president of product management at Teledoc, I led product strategy for value-based care initiatives. My passion for digital transformation in B2B2C markets has driven successful healthcare initiatives from ideation to commercialization. I believe that success in healthcare is really understanding your users and building solutions to solve their everyday problems in a seamless, understandable way.

RR: Scott, as part of your new responsibilities at HHAeXchange, how will you ensure effective communication and collaboration between internal departments to better serve customers?

Scott: We’re focused on enhancing our platform, which connects state agencies, managed care organizations, providers and caregivers, so cross-departmental communication and collaboration are vital. With shared services such as implementation, revenue cycle operations, integrations, technical customer care, training, and customer education under my purview, I plan to streamline communication pathways and ensure all teams are aligned with and working toward our common goals.
We want to leverage our teams’ diverse talents to drive transformation. My approach includes fostering an integrated work environment where interdepartmental meetings, clear information channels, and shared objectives are the norm. Regular check-ins and transparent leadership are key to ensuring every department understands how their work directly benefits our clients, the members they serve, and the company’s broader goals.

RR: And how will you ensure HHAeXchange’s solutions and product enhancements meet the needs of all homecare stakeholders – caregivers, provider agencies, members, and payers?

Scott: Engaging with stakeholders is critical. We involve provider agencies, caregivers, payers and others in our development process to ensure that our platform addresses real-world needs effectively. Our comprehensive engagement strategies support this with initiatives like periodic customer summits, road shows, and information sessions to capture a wide array of insights and feedback.
We monitor industry trends, regulatory changes, and technological advancements, which are factored into planned enhancements and solution updates. And with a team of reputable industry experts, we’re working to ensure that our products exceed the evolving needs of all homecare stakeholders.

Lori: We understand that stakeholders in the homecare space have diverse and critical needs. We keep a pulse on industry trends and challenges such as issues with caregiver turnover, regulatory & compliance changes, increasing volume of live-in caregivers, and an increase in diversification in home care utilization. With these observations, we aim to provide products that support healthcare agencies and caregivers as these trends evolve. Our solutions must be built with a nimbleness that accounts for a continuous change in regulations, EVV compliance requirements, and stakeholder expectations. Frequently engaging with stakeholders, conducting thorough market research, and incorporating feedback loops are integral to our product development processes.

RR: Lori, you mentioned the diverse needs of your stakeholders. What are the greatest problems your clients and prospects say they are looking to solve with improved homecare management software solutions and EVV platforms?

Lori: Our clients are prioritizing caregiver retention and looking for comprehensive solutions to streamline operational processes like billing, HR, and payroll while ensuring regulatory compliance and providing high-quality member care. They need tools to manage the diverse locations of members’ and workers’ schedules, foster strong member-caregiver matches, and enable transparent communications among provider teams.

Taking those challenges into consideration, HHAeXchange aims to equip our solutions with time-saving, stress-reducing features. Operational worklists, for example, alert agencies to important dates and actions their teams need to take regarding caregiver compliance and client authorizations. Our appointment module and case broadcasting feature reduce hassles associated with scheduling visits and quickly filling unexpectedly open shifts.

RR: Two questions, Lori. What trends are you seeing that are transforming homecare delivery models and, in addition to technology, are there any other trends shaping the homecare industry in 2024?

Lori: The ongoing caregiver shortage remains a concern, driving a shift toward more strategic technology investments and training opportunities. Homecare delivery is becoming more person-centered, suggesting the industry has adjusted to EVV and is using the technology to incorporate collaboration with families as caregiver participants. Additionally, there’s a growing emphasis on self-direction, with clients seeking more choice, flexibility and control in their care. Compliance is gaining more attention, with increased scrutiny to ensure standards of care are met across the board. Data and analytics will continue to be a primary enabler for how healthcare is shaped. We account for all of this in our product strategy and development plans.

RR: Final questions for you, Scott. How does HHAeXchange envision the homecare industry evolving in 2024 and, more specifically, how do you see the company’s innovations playing a role in that transformation?

Scott: The homecare industry is at a critical juncture. As Lori said, we’ve noted significant shifts toward value-based care, self-directed care, and person-centered approaches. At the same time, the fundamentals of homecare are as important as ever. HHAeXchange’s role is to stay ahead of trends while improving product offerings and customer experiences. We strive to balance innovative thought leadership with steady progress, continually enhancing the functionality of our foundational platforms to meet clients’ needs.
We’re investing in scalable technology, service improvements, customer education, and strategic integrations to accommodate the industry’s evolution. Our leadership is committed to empowering providers and payers alike with tools to improve caregivers’ efficiency and address fraud, waste and abuse in the industry. Through these efforts and plans, we aim to facilitate a more sustainable, higher-quality, and accessible homecare ecosystem for all involved, ensuring members have the option to receive care and treatment in the comfort of their own homes.

RR: Thank you both, again, for your time. I wish you both great success in your new roles.

# # #

Kristin RowanKristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Private Duty Home Care in Fraud Enforcers’ Crosshairs

Clinical

by Elizabeth E. Hogue, Esq.

Some owners and managers of private duty home care agencies mistakenly think that fraud and abuse prohibitions apply only to services paid for by the Medicare Program. In fact, fraud and abuse prohibitions apply to providers if they accept any state or federal funds, including, but not limited to, Medicaid, Medicaid waiver, VA, and Tri-Care. Many private insurers have adopted the prohibitions on fraud implemented by state and federal programs.

Private duty home care agencies are increasingly in the crosshairs of fraud enforcers if they receive reimbursement from Medicaid and/or Medicaid Waiver Programs. The reason for enhanced scrutiny is that both the federal government, which partially funds state Medicaid and Medicaid Waiver Programs, and state governments that also fund these programs are alarmed about the high costs of them.

Conventional wisdom says that there are big bucks to be saved if fraud and abuse in the Programs are controlled and ultimately eliminated. Conventional wisdom also says that enforcement actions in Medicaid Programs have just scratched the surface. According to this “wisdom,” there are big bucks to be recouped from “low-hanging fruit!”

A recent report from the Office of Inspector General of the U.S. Department of Health and Human Services seems to support this perception regarding private duty home care agencies based on the following:

  • Patient Fallen From Wheelchair AbuseBetween 2014 and 2023, at least 34% of fraud convictions in some years were based on private duty home care services. In some years, this percentage was as high as 48%.

  • In fiscal year 2023, there were 279 criminal convictions related to private duty home care services compared to 66 for registered nurses and 43 for home health agencies.
  • Recoveries from private duty home care agencies in 2023 totaled $26.4 million.
  • The amount of civil recoveries reached a 4-year high in 2023 and the combined criminal and civil recoveries were $1.2 billion, resulting in a return on investment of $3.35 for every $1 spent.

The return on investment of more than three times the amount spent is perhaps the most important figure of all. With a three to one return, regulators will not hesitate to “beef up” enforcement actions.

THE CONSEQUENCES OF FRAUD AND ABUSE ARE SEVERE WHEN SERVICES ARE PAID FOR BY THE MEDICAID AND OTHER STATE AND FEDERAL PROGRAMS!

Personal care private duty agencies, don’t believe the myth that only services paid for by the Medicare Program are subject to fraud and abuse enforcement. The consequences may be devastating, including the loss of businesses. Heads up!

©2024 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.
©2024 This article appeared in The Rowan Report. All rights reserved.

The Wrong Way to Use AI in Healthcare

Admin

by Tim Rowan, Editor Emeritus

Lawsuits are beginning to pile up against insurance companies participating in the Medicare Advantage program. The complaint? The wrong way to use AI in healthcare is with faulty algorithms to approve or deny claims. While AI can be extremely helpful in streamlining administrative tasks — comparing physician notes with Home Health assessments and nursing notes or reading hospital discharge documents — it seems not to be any good at deciding whether to approve or deny care.

The Wrong Way to Use AI in Healthcare Example 1

The Minnesota case, November, 2023, UnitedHealth Group:

    • An elderly couple’s doctor deemed extended care medically necessary
    • UnitedHealth’s MA arm denied that care
    • Following their deaths, the couple’s family sued UnitedHealth, alleging:
      • Straight Medicare would have approved the extended care
      • United uses an AI model developed by NaviHealth called nH Predict to make coverage decisions
      • UnitedHealth Group acquired NaviHealth in 2020 and assigned it to its Optum division
      • nH Predict is known to be so inaccurate, 90% of its denials are overturned when appealed to the ALJ level
      • UnitedHealth Group announced in October, 2023 that its division that deploys nH Predict will longer use the NaviHealth brand name but will refer to that Optum division as “Home & Community Care.”

The family’s complaint stated, “The elderly are prematurely kicked out of care facilities nationwide or forced to deplete family savings to continue receiving necessary medical care, all because [UnitedHealth’s] AI model ‘disagrees’ with their real live doctors’ determinations.”

The Wrong Way to Use AI in Healthcare Example 2

The Class-Action case, December 2023, Humana:

    • A lawsuit was filed on December 12, 2023 in the U.S, District Court for the Western District of Kentucky
    • It was filed by the same Los Angeles law firm that filed the Minnesota case the previous month, Clarkson
    • The suit notes that Louisville-based Humana also uses nH Predict from NaviHealth
    • The plaintiffs claim, “Humana knows that the nH Predict AI Model predictions are highly inaccurate and are not based on patients’ medical needs but continues to use this system to deny patients’ coverage.”
    • The suit says Medicare Advantage patients who are hospitalized for three days usually are eligible to spend as many as 100 days getting follow-up care in a nursing home, but that Humana customers are rarely allowed to stay as long as 14 days.
    • A Humana representative said Humana their own employed physicians see AI recommendations but make final coverage decisions.

What Makes This Possible

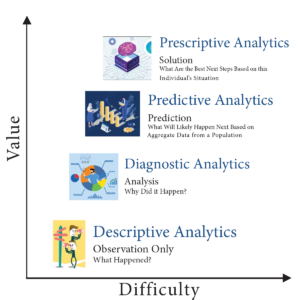
According to experts we speak with, there are many ways to use data analytics. The insurance companies named in the lawsuits use predictive decision making. This way of analyzing data compares a patient to millions of others and deduces what treatment plan might be suitable for one patient, based on what was effective for most previous patients. Opponents of this method have called it “data supported guessing.”

A superior analysis method experts are coming to understand  is prescriptive decision making. This is taking all of the available historical and current data surrounding a patient and making a clinical decision specifically designed to that patient’s age, gender, co-morbidities, doctor recommendations, and treatment records.The Power of AI with SmartCare

Until recently, predictive analysis was the preferred method because of its resource efficiency. Examining the data of every individual patient used to be prohibitively labor-intensive, requiring hours of reading hospital records, physician notes, and claims. Today, however, AI tools are able to do that work in seconds, making prescriptive analytics and customized plans of care possible.

Fix May Be in the Works

In a February 6, 2024 memo to all Medicare Advantage Organizations and Medicare-Medicaid Plans, CMS explained the difference between predictive and prescriptive analytics. The memo said these plans may not make coverage determinations based on aggregated data but must look at each individual:

“For Medicare basic benefits, MA organizations must make medical necessity determinations in accordance with all medical necessity determination requirements, outlined at § 422.101(c)1 ; based on the circumstances of each specific individual, including the patient’s medical history, physician recommendations, and clinical notes; and in line with all fully established Traditional Medicare coverage criteria.”

In response to a request for clarification, the CMS memo laid out its rule in specific language:Wrong AI in Healthcare Prescriptive Analytics

An algorithm or software tool can be used to assist MA plans in making coverage determinations, but it is the responsibility of the MA organization to ensure that the algorithm or artificial intelligence complies with all applicable rules for how coverage determinations by MA organizations are made. For example, compliance is required with all of the rules at § 422.101(c) for making a determination of medical necessity, including that the MA organization base the decision on the individual patient’s circumstances, so an algorithm that determines coverage based on a larger data set instead of the individual patient’s medical history, the physician’s recommendations, or clinical notes would not be compliant with § 422.101(c).
(emphasis added)

“Therefore, the algorithm or software tool should only be used to ensure fidelity with the posted internal coverage criteria which has been made public under § 422.101(b)(6)(ii).”

In further responses to questions in the same memo, CMS made it clear MA plans must make the same coverage decision original Medicare would make. The only allowable exception is that plans may use their own criteria when Medicare Parts A and B coverage criteria “are not fully established.”

Knowledge of this CMS directive may give Home Health agencies one more arrow in their quiver when going to battle with powerful, profit-oriented insurance companies over harmful, illogical AI algorithm decisions.

For information on the right way to use AI in healthcare, see our complimentary article in this week’s issue.


Tim Rowan, Editor EmeritusTim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

 ©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com