Cigna Divests Medicare Business

Regulatory

by Kristin Rowan, Editor,

On Wednesday, January 31, Cigna and HCSC signed an agreement to sell all of Cigna’s Medicare business — including traditional Medicare, supplemental benefits, Medicare Part D offerings, and CareAllies, a value-based care management subsidiary.  — to HCSC, a Blue Cross / Blue Shield partner with operations in Illinois, Texas, New Mexico, Oklahoma and Montana. The $3.3 billion deal will quadruple the size of HCSC’s Medicare Advantage population, which numbered 217,623 as of this month.

Medicare Advantage had not been a significant business for Cigna. CEO David Cordani explained that it required resources disproportionate to its size in the company. With 19 million insurance customers, Cigna had a little over a half million in its MA business, a little under a half million Medicare supplement members, and 2.5 million in Part D.

It had previously been reported that Cigna believed divesting its Medicare business would make its merger with Humana more acceptable to regulators. The company completed its HCSC deal even though negotiations with Humana had already broken down. Though inked today, the deal is  not expected to close until the first quarter of 2025.

# # #

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com


Is There an Answer to Paying for Palliative and Private Care?

Uncategorized

By Kristin Rowan, Editor

Last month, we published an article in partnership with Bob Roth of Cypress HomeCare Solutions in Scottsdale, AZ about paying for long-term care at home. Since then, I have come across some interesting information as we continue to tackle the issue of paying for care that is not reimbursed by the current Medicare/Medicaid system.

Medicare and Medicare Advantage have set pay rates for home health and hospice care. Home Health Value-Based Purchasing (HHVBP), implemented by CMS, was designed to incentivize agencies by paying more for quality care rather than a higher number of services provided. This is similar to giving advances and pay raises based on performance rather than longevity in a job, which I’m all for. However, the HHVBP overlooked palliative care altogether and neither the fee-for-service model nor the HHVBP model includes supportive (read private duty) care at home. Since these services are not reimbursed, there is no incentive to provide them nor way to get paid for them if the patient cannot pay out-of-pocket.

This causes two problems:

1. Home Health and Hospice Agencies are reluctant to provide unreimbursed care, with good reason, so the overall patient experience is less than ideal, rehospitalization rates increase, star-ratings and scores decrease, bonuses go away, and the agencies make less money than before.

2. Patients can’t get the care they need and want. Palliative care patients may receive Hospice care too early, or they may not receive care at all because they fall between home health and hospice. Patients who need supportive care at home can’t afford it so they either go without, causing increased complications or they rely on friends and family members who burn out under the stress of being a full-time caregiver.

Innovative care strategies can overcome the obstacles faced by agencies and patients alike. There may not yet be a perfect solution, but there are some innovative ideas out there and something has to disrupt the current pay model.

Palliative Care Partners

Medicare Advantage organizations and primary physician groups receive a “cost of care” analysis for the duration of the patient care. The organization takes on the risk of that patient costing more than what the MA plan will pay, but can make more money if patient care costs less than anticipated. Palliative care at home costs less. David Causby, President and CEO of Gentiva, a Hospice organization that operates in 35 states across the U.S. and has an average daily census of 26,000, has implemented a plan of care in cooperation with these organizations in what he calls Advanced Illness Management (AIM) Model for Risk-Based Partnerships. Designed for palliative care, Gentiva creates a plan of care that includes visit frequency and care needs and employs nurse practitioners, care managers, after hours RNs and social workers. The hospital pays Gentiva on a PMPM model with shared savings. The hospital still gets paid the full amount from MA but uses fewer resources, has lower costs, and sees reduced rehospitalizations, saving more than what they pay out. According to Gentiva, this partnership “provides value to contracted organizations by decreasing the overall end-of-life spend on this high-risk patient population.”

Supportive Care at Home Innovations

Supportive Care at Home (Private Duty Home Care, Private Pay, Non-medical home care) is not covered by Medicare, Medicare Advantage, or most health insurance plans. Limited Medicaid grants, VA plans, and long-term health insurance pay for some supportive care at home. Without one of these plans, patients and family members pay out-of-pocket for supportive care at home, averaging $22-$27 per hour with a 4-hour minimum. In some states it can cost up to $50 per hour. At $80 per day, that’s around $20,000 per year.

One software company we recently spoke with is upending the home care model with fee-for-service model that charges by the minute, rather than by the hour, making care more affordable for more people. You can see our product review of Caring on Demand here. By reducing the cost for customers and reducing the time for caregivers, agencies can onboard more customers without hiring more caregivers. The system is being used in facilities where these services are not provided, which allows a caregiver to visit several people in one stop. The agency and the caregiver can see the same income in the same time, spread out across multiple private payers.

Combining Innovation for a Win-Win-Win

I heard about Caring on Demand and spoke with its founder in August of 2023. I spoke with one Home Care agency owner who recently started working with Caring on Demand. “Times have changed,” the agency owner said. With fewer caregivers joining the workforce, increased levels of burnout since 2020, and CMS changes that overlook palliative and non-medical care, maybe there’s another way…

  • Partnerships with organizations and physician groups that have Medicare, MA, and traditional health insurance patients, non-medical home care agencies, and palliative care providers.
  • Localized groups of patients in limited areas like retirement villages, planned communities, neighborhoods, or small towns.
  • Cost sharing and care coordination that includes in-home palliative care visits, supportive care, communication with primary care providers and specialists
  • Preventative intercessions to avoid unnecessary ER visits and hospitalizations
  • Shorter visits per caregiver with multiple visits to a community each day
  • Cost sharing among patients splitting a 4-hour minimum visit among 4-8 patients
  • Shared savings from reduced hospital stays, shorter durations of hospice care, and nursing visits that are supplemented by supportive care

Gentiva has experienced some success already in using shared savings as a payment model. Can costs be decreased even more by adding supportive home care to this plan? Is there enough shared savings for three payees instead of two? I don’t have the answers to these questions, but I do believe providers of supportive care and palliative care have been in the background, overlooked by CMS and MedPAC for long enough. If they aren’t going to recognize the positive impact and cost savings of home care and palliative care and include them in the reimbursement model, we may have to do it for them.

We’d love to hear your feedback on this and other innovative ways to combat the crisis of paying for care at home.

# # #

Kristin Rowan

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com



Get Closer to Bonus Pay with the Net Promoter Score

Admin

by Kristin Rowan, Editor

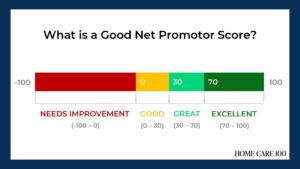
Medicare Advantage has multiple measures of success for payment bumps and bonuses. Rehospitalization rates has long been the most important measure of how well a care at home agency is performing, but there are additional measures that can help or hurt your agency. One that is gaining a lot of traction with MA and can impact your agency’s ability to survive is the overall patient experience. Measuring the patient experience can be subjective, but a great marketing tool to use is the Net Promoter Score (NPS). NPS is a calculation of patient responses regarding their likelihood to recommend you to others. A NPS score of “0” means that, overall, your clients are not going to speak positively or negatively about you; there just isn’t anything outstanding enough to bother saying anything. Anything above zero is better than nothing, but 30 and above is ideal.

During January’s HomeCare 100 Winter Conference, Tim Craig moderated the panel, “The MA Member Experience and Why it Matters” with a panel of experts. He posed this question to the audience:

“How well do home care providers perform when it comes to delivering on patient experience?”

Rating care provider performance on a scale of 1-5, the responses during the panel were somewhat surprising

  • 47% of those who responded rated the delivery on patient experience 3
  • 43% said 4
  • 6% responded 2
  • A mere 4% responded 5
  • There were no responses of 1

If we turn these answers into a Net Promoter Score, we get -6. If caregivers, administrators, and providers don’t believe we’re doing a good job, how can we expect our clients, patients, and families to be happy with the care they receive?

Statistics

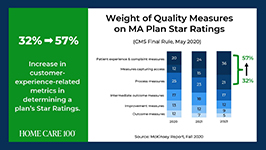
  • Patient experience and complaint measures count higher toward star rating than they have before
  • CAHPS Scores have changed weight from 1.5 to 4 since 2021
  • Star Ratings Determine Bonus Eligibility and Amount – starts at 4 stars and above
  • Number of plans that have a 4.0 or higher star rating dropped from 64% to 43%
  • Disenrollment is on the rise from 10% in 2017 to 17% in 2021

Net Promoter Score

Glen Moller, CEO of Upward Health, whose net promoter score is a whopping 86, said:
“The Member Experience has always been important. What has changed is the way we manage it, given the implication of the CAHPS rating, you can’t be a 4 star without high CAHPS scores.” Moller improved his patient experience with internal surveys to get actionable intel and asking open-ended questions. Look at change and innovation and how that could be disruptive to members. Member experience is at the center of all the other measures. No matter what benefits you’re offering, embed member experience measures at every step of the process.

Because your star rating directly impacts your ability to receive bonuses and because experience-related metrics are increasingly weighted in determining star ratings, you should be looking at the member experience more closely in all of your process. You should also be measuring the member experience and looking at ways to improve it.

Ways to measure ME

• HHCAHPS
• Quality of Patient Care Ratings
• Word of Mouth
• Net Promoter Score
• Glassdoor
• YelpCalculating a Net Promoter Score can be challenging, especially when trying to get older or infirmed patients to answer a survey. For the most accurate NPS, send a single question survey to all of your current and past customers asking them to rate, on a scale of 1 to 10, “How likely are you to recommend us to a friend or family member.” If you aren’t able to do this, you can still calculate a rough NPS using your other measures. You can use your Google and Yelp reviews with a simple formula: % of promoters – % of detractors = NPS. Three stars and below are detractors; four and five stars are promoters.The NPS score is more about comparative to the usual experience rather then the actual experience. A high score from a customer doesn’t necessarily meant it’s “great”, only that it’s much better than what they’re used to or what they expected.

The NPS is not the only measure of customer experience. To get the whole picture, use all the data you have to find out what interventions should be done and implement them. Whether the change is in training your staff, updating your scheduling process, using AI to help communicate directly with patients and families, or simply streamlining your website for a better user experience, you can improve your chances for higher ratings and bigger bonuses in a few easy steps.

I won’t often insert a shameless plug into an article, but if increasing patient satisfaction and member experience can help your agency survive the CMS pay cuts, and you need help with getting a NPS, understanding how to measure your patient experience, or getting online reviews, please contact me for more information. My marketing agency is happy to help get you started.

# # #

Kristin Rowan

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

 

New Players in Home Care

Admin

By Kristin Rowan, Editor

Home care is no stranger to mergers and acquisitions. It seems there is news almost daily about companies joining forces or selling parts of their company to new entities. Notably, we reported just last week that Cigna has dropped its entire Medicare Advantage book of business. This week, we have two M&A stories to share with you.

Acquisition

Texas-based agency Angels of Care, previously of Varsity Healthcare Partners, has been bought by Nautic Partners, a private equity company. Angels of Care provides pediatric home health, including private duty and skilled nursing services, along with physical and speech therapy, and respite care. Angels of Care operates in seven states, up from two states prior to their partnership Varsity Healthcare Partners, and employs more than 2,000 nurses, physical therapists, and other service providers.

Nautic Partners, based in Providence, RI, is already a backer of VitalCaring Group, a similar agency with locations across the southern United States, Integrated Home Care Services, providers of DME, home care, and infusion services in Puerto Rico, almost 30 additional healthcare companies. Nautic is a middle-market firm founded in 1986. They specialize in healthcare, industrials, and services.

Partnership

CVS’ Aetna has partnered with Monogram Health to offer in-home care services to Medicare Advantage members with chronic kidney disease. Nurses from Monogram will provide in-home and virtual appointments to eligible members. The two companies will also reportedly work to get timely referrals for kidney transplant evaluations.

Monogram Health is a tech start-up for in-home kidney disease management. Their latest growth funding round garnered $375 million in new funding from health care companies and financial backers, including CVS. Monogram has raised a total of $557 million. Monogram operates by creating value-based care deals with health insurance plans and risk-bearing providers to manage chronic and end-stage renal diseases.

If this model sounds familiar to you, it might be because we wrote last week about Gentiva, which is partnering with risk-based providers to offer palliative care services with risk-sharing benefits on both sides. I expect this is not the last time we will hear/write about risk-sharing partnerships to pay for services that aren’t covered by health care plans.

# # #

Kristin Rowan

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

Family Caregiver Tax Credit Bill

CMS

By Kristin Rowan, Editor

Republican and Democratic leaders joined forces to introduce the Credit for Caring Act (S. 3702, H.R. 7165) in support of family caregivers across the country. Family caregivers are those who are caring for a family member but are not nurses or employees of any home care agency. They are not eligible for Medicare or Medicaid payments, nor is there an employer paying them for the endless hours of support they provide. Family caregivers are often under a lot of emotional and financial stress. Some have full-time jobs in addition to the care provide. Others are caring for more than one family member, sometimes in different homes.

The Credit for Caring Act, a bipartisan effort to recognize the personal cost to family caregivers with a $5,000 federal tax credit for eligible working family caregivers. As is generally the case with government intercession, the “eligible” part will exclude many family caregivers. From Congress.gov:

“This bill allows an eligible caregiver a tax credit of up to $5,000 for 30% of the cost of long-term care expenses that exceed $2,000 in a taxable year. The bill defines eligible caregiver as an individual who has earned income for the taxable year in excess of $7,500 and pays or incurs expenses for providing care to a spouse or other dependent relative with long-term care needs.”

The bill also includes the caveat that eligible caregivers must incur qualified expenses, limited to goods, services, and supports. The language excludes the time and energy a family caregiver expends, essentially limiting the tax credit to repayment of money paid out of pocket for care that should have been covered by Medicare, Medicaid, or private health insurance, but isn’t. The cost of a direct care giver is included in eligible expenses, but doesn’t consider the family caregiver to be one.

As I break down the math in my head, I come up with this:

A tax credit of $5,000 is received if the caregiver has spent $16,600 in the previous year (5,000/.3). This leaves a total out of pocket amount of $11,100. Supportive home care services average $30/hour. $16,660 is equivalent to 555 hours of non-medical home care. That’s roughly 10 hours per week or 1-1/2 hours per day. This doesn’t include the costs for DME, doctor visits, lost wages from time off work, medication, or any of the other eligible expenses included in the bill.

This is getting us one step closer to paying for supportive in-home care and palliative care services, but I don’t think it goes far enough. An under-served, under-paid population who makes $7,500 per year cannot afford $16,000 in out-of-pocket expenses in order to qualify for the maximum tax credit. Once this bill is (hopefully) passed, we should move on to including additional services in the Medicare/Medicaid reimbursement model. The Rowan Report joins NAHC in its support of the Credit for Caring Act and urges you to reach out to your representatives to urge them to support the passing of the bill.

# # #

Kristin Rowan

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

 Read the article and statement from NAHC here

Read the full text of the bills: H.R. 3321 and S. 3702

Find your Senator here

Find your Representative here

Could Jimmy Carter’s Hospice Care Lead to Covered Palliative Care Services?

Clinical

By Kristin Rowan, Editor

The news this week has been filled with stories about former president Jimmy Carter, 99, who entered hospice care last year. His wife, Rosalynn Carter was in hospice care for only a few days before she passed away in November. Advocates and hospice providers are hoping that Carter’s length of care in hospice will help increase awareness of what hospice care really is.

Hospice care is a misunderstood service. Many people equate hospice care with dying. While it is true that patients are only eligible for hospice care if they have a life-ending illness with no hope of cure, hospice care involves a lot more than easing a patient through the end-of-life transition. Physical symptoms are eased with medicine and the patient’s emotional well-being is supported as well. Just as importantly, the family’s emotional needs are met through hospice care.

The Carter family’s high profile has shed some much needed light on hospice care in general. The vast difference in length of care between the former first lady (three days) and the former president (one year and counting) has also highlighted the degree to which hospice care can be administered.

The hope for many, in light of the public coverage of Carter’s hospice care, is a change in long-term care coverage to cover the gap between hospital care and hospice care. Medicare does not have a long-term care benefit, so patients either go without this needed care or pay for it out of pocket. Detractors argue that new taxes would have to be levied in order to fund this type of care, making the change politically difficult.

I would argue that long-term care benefits could be used to pay for step-down care instead of hospice care and would not need a separate budget. After all, isn’t that what palliative care aims to do? Home health care aids in recover and hospice care maintains quality of life during end-of-life care. Palliative care is the bridge that spans the two, when a patient is not going to recover, but isn’t ready or eligible for hospice care. Adding Medicare and Medicaid coverage for palliative would lower the overall cost of hospice care and add much-needed service for the patients that fall between the gap.

# # #

Kristin Rowan

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

Acute Hospital Care at Home

Clinical

By Kristin Rowan, Editor

Federal Waiver Program

In 2020, CMS launched a hospital care at home program to help increase patient capacity during the height of the Covid-19 pandemic. The study included 300 hospitals and thousands of patients receiving care in their home using a hospital at home waiver. Outcomes of the study showed that patients had greater ability to stand up and move around at home than would have had in a hospital and that in-home caregivers were better able to educate patients on home to care for themselves once they were able to see the social determinants of care in the home. CMS also reports only 7.2% of patients were required to be transferred to a hospital.

Hospital Study

Mass General Brigham conducted its own study alongside CMS and analyzing outcomes of diverse patients, including socially vulnerable and medically complex patients. The findings of their national analysis showed that within 30 days of discharge, 2.6% of patients used a SNF, 3.2% died, and 15.6% were readmitted. Findings were consistent among all groups, including those who generally have worse outcomes: patients of Black and Latine race and ethnicity, dual-eligible patients, and patients with disabilities.

Health System Study

In April of 2020, Kaiser Permanente conducted an 18-month study on the scalability of “Advanced Care at Home” (ACAH). The patients all required hospital-level care and were first admitted to the program through the emergency department. Some were admitted to the hospital, and some were instead admitted to the Kaiser ACAH program, where a team of nurses, physicians, nurse practitioners, and a pharmacist developed a care plan.

This study increased its daily census from 7.2 per day to 12.7 per day at the end of study. The average episode of care decreased from 7.43 days to 5.46 days and readmission rates dropped from 11.52 percent to 9.24 percent. These patients were less likely to experience delirium than patients admitted to traditional hospital settings. The researchers noted the limitation of the study as being too small to develop precise comparisons.

Limitations of Acute Hospital Care at Home

Currently, the only patients eligible for AHCaH are those who have been evaluated in a hospital or emergency department. Kaiser has extended this to patients seen in their own urgent care offices in areas where they don’t own a hospital. Kaiser has served a few thousand patients through this program, but they estimate there are more than 1.1 million eligible patients. Rural patients who don’t live near a hospital or emergency department have the same trouble accessing AHCaH that they do accessing hospital and physician care now.

The CMS waiver for AHCaH has been extended through December 2024. Beyond that, it is unclear how hospital care at home will be reimbursed. Some providers have offered hospital care at home to risk-based patients in a VBC model. Not all eligible patients will qualify for the waiver or VBC reimbursement. Without specific provisions from CMS to reimburse hospital care at home for all Medicare and Medicaid patients and coverage from private insurance, the hospital at home program will remain limited.

The current model for AHCaH includes technology support for the patient using a tablet, smartphone, or other device. This requires that the patient have a broadband internet connection in the home, which eliminates eligibility for rural patients who are already underserved.

Final Thoughts

There is a lot of support for Hospital Care at Home among providers, health systems, and consumer insurance companies. Support for home health, hospice, palliative care, and supportive home care has not been as strong. As these larger players start to see the cost and outcome benefits of care in the home, a few things may happen.

First, hospitals, payers, and physician groups may start to recognize the value of care at home and be more open to creating referral partnerships with care at home agencies. Home care is a small percentage of total care reimbursed by Medicare and Medicaid and we could see that increase.

Conversely, these providers may realize that care at home is lucrative and will extend their own AHCaH models to include post-acute and hospice care, cutting out home care agencies altogether. Care teams are constructed around a Hospital Care at Home patient. Including a post-acute nurse who is familiar with the patient history would provide additional continuity of care.

Either way, I see the support for the Hospital Care at Home program as beneficial to home health. Branches of health care that were previously averse to extending patient care into the home are now supporting it. Increased adoption of telehealth and other technology platforms increase the possibilities for integrating with home health and hospice providers. Interoperability between Hospital Care at Home and Post-Acute Care at Home may finally become a reality.

We will continue to report on the AHCaH waiver as the deadline to renew comes closer.

# # #

Kristin Rowan

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

 Sources:

CMS (2024) Acute Hospital Care at Home Data Release Fact Sheet. Retrieved from: https://www.cms.gov/newsroom/fact-sheets/acute-hospital-care-home-data-release-fact-sheet#:~:text=In%20response%20to%20challenges%20faced,inpatient%2Dlevel%20care%20at%20home.

Mass General Brigham (2024) Study of National Data Demonstrates the Value of Acute Hospital Care at Home. Retrieved from: https://www.massgeneralbrigham.org/en/about/newsroom/press-releases/study-of-national-data-demonstrates-the-value-of-acute-hospital-care-at-home#:~:text=In%20addition%2C%20within%2030%20days,and%20have%20fewer%20adverse%20events.%E2%80%9D

mHealth Intelligence (2023) Kaiser Permanente Study Shows Scalability of Hospital-at-Home model

Enforcers Target Discharge Planners/Case Managers Yet Again

Admin

By Elizabeth E. Hogue, Esq.

Case managers/discharge planners continue to come under fire from fraud enforcers for violations of the federal anti-kickback statute. This statute generally prohibits anyone from either offering to give or actually giving anything to anyone in order to induce referrals. Case managers/discharge planners who violate the anti-kickback statute may be subject to criminal prosecution that could result in prison sentences, among other consequences.

A U.S. District Judge in California sentenced an owner of a post-acute provider to eighteen months in prison for one count of conspiracy to commit health care fraud and one count of conspiracy to pay and receive health care kickbacks. From July of 2015 through April of 2019 the provider paid and directed others to pay kickbacks to multiple case managers/discharge planners for referrals of Medicare patients, including employees of health care facilities and employees’ spouses. Recipients of the kickbacks included a discharge planner/case manager at a hospital, and discharge planners at skilled nursing and assisted living facilities.

Payments of kickbacks resulted in over eight thousand claims to Medicare for patients referred to the provider. Medicare paid the provider at least two million dollars for services provided to patients referred in exchange for kickbacks. Because the provider obtained patient referrals by paying kickbacks, the provider should have not received any Medicare reimbursement. The discharge planners/case managers who received kickbacks from the provider also pled guilty and will be sentenced soon.

The Office of Inspector General (OIG) of the U.S. Department of Health and Human Services (HHS), the primary enforcer of fraud and abuse prohibitions, says that discharge planners/case managers and social workers cannot accept the following from providers who want referrals:

  • Cash
  • Cash equivalents, such as gift cards or gift certificates
  • Non-cash items of more than nominal value
  • Free discharge planning services that case managers/discharge planners and social workers are obligated to provide

Discharge planners/case managers and social workers provide extremely important services that are valued by many patients and their families, but their credibility and trustworthiness is destroyed when they make referrals based on kickbacks received.

A word to managers and all the way up the chain of command to CEOs: whether or not you know when case managers/discharge planners accept kickbacks, the OIG may also hold you responsible.

You may be responsible if you knew or should have known. The OIG has made it clear that your job is to monitor and to be vigilant. A good starting point is to put in place a policy and procedure requiring discharge planners/case managers to report in writing anything received from post-acute providers. Even better, how about a policy and procedure that prohibits all gifts?

Now a word to post-acute marketers: do not give kickbacks to discharge planners/case managers and social workers. It is simply untrue that you must give kickbacks in order to get referrals. The proverbial bottom line is: Do you like the color orange? Is an orange prison uniform your preferred fashion statement? Please stop now!

Reprinted with permission from ©2024 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

A Beacon of Hope in Recruitment and Retention

Clinical

by The National Minority Health Association,

Embracing Change, Empowering Caregivers

In the ever-evolving world of homecare, recruitment and retention pose significant challenges, particularly in California. However, FACT – Family, Adult and Child Therapies, a southern California-based homecare agency, has emerged as a beacon of hope, leveraging the innovative Caring4Cal program to enhance its workforce and service quality.

The Rising Star of FACT

FACT, dedicated to supporting individuals with developmental disabilities, has a rich history dating back to the 1980s. Originating& from a collaboration of dedicated professionals and parents, FACT has been at the forefront of providing exceptional care and support to a diverse clientele, including minors, adults, and families grappling with a spectrum of diagnoses.Caring4Cal

Caring4Cal: A Game-Changer in Caregiver Recruitment and Training

Under the leadership of its Board of Directors and their executive team: Tina Castro (Director of Adult and Employment Services), Lethia Perry (Director of Operations and Human Resources) and Spencer Ludgate (Director of School-Based Services and Controller), FACT has fully embraced the Caring4Cal community health worker recruitment program. This initiative has seen remarkable participation, with 39 staff members taking advantage of the opportunities it offers.

Eligibility and Scope

To participate in Caring4Cal, caregivers must:

  • Reside in California.
  • Currently work in or aspire to join an eligible job role in home- and community-based settings.
  • Eligible roles include a wide array of healthcare professionals like HHA, CNA, RN, LVN, and more.

Partnership and Funding

The National Minority Health Association (NMHA), a pivotal entity in reducing health disparities among minorities, received a substantial grant under the Caring4Cal initiative. Spearheaded by the California Department of Healthcare Access and Information (HCAI), this program is a concerted effort to reinforce the workforce in home- and community-based care. With a strategic collaboration with Nevvon, a leader in e-training solutions for healthcare, this initiative is set to revolutionize caregiver training and retention.

FACT: A Legacy of Excellence and Adaptability

FACT’s enduring commitment to providing holistic, affordable, and quality mental health care is well-aligned with the Caring4Cal program. Their person-centered care approach, accessible locations, and advocacy for independence resonate deeply with the program’s objectives. For over twenty years, FACT has not only adapted to societal changes but has also been a vanguard in accepting and appreciating diverse abilities.

The Future Outlook

With the Caring4Cal program, FACT is not only addressing the immediate need for skilled caregivers but is also shaping a future where comprehensive and compassionate care is accessible to all Californians. This initiative stands as a testament to FACT’s unwavering dedication to its mission and philosophy.

A Call to Action

The success of FACT with the Caring4Cal program is a clarion call to all agencies in the sector. With available funding and training opportunities, it is an opportune time for other agencies to participate and enhance their capabilities. The program not only offers financial incentives but also ensures that caregivers are equipped with state-of-the-art skills to meet the growing demands of the sector.

FACT, working with the NMHA and its successful integration of the Caring4Cal program, exemplifies how strategic partnerships and innovative training initiatives can effectively address the twin challenges of recruitment and retention in the homecare industry.

###

About the NMHA: The National Minority Health Association is a 501c3 non-profit organization founded in 1988. The NMHA delivers on its mission of heath equity through innovative programs including Health is for EveryBODY™ (www.healthisforeverybody.org), Operation Healthy You™, Equityville™ and The Art Alliance, to name a few. The lack of health equity in underserved, marginalized and hard to reach communities translates into lost lives, adverse health outcomes, higher costs, diminished productivity and declines in quality of life and well-being for everyone. For more information visit www.thenmha.org






