The Alliance Hosts Second Annual Advocacy Week

FOR IMMEDIATE RELEASE

Contact:                                                            Hannah Kristan
communications@allianceforcareathome.org
202-355-1647

Over 150 Advocates Convene on Capitol Hill to Champion Care at Home

National Alliance for Care at Home Hosts Second Annual Advocacy Week on Capitol Hill    

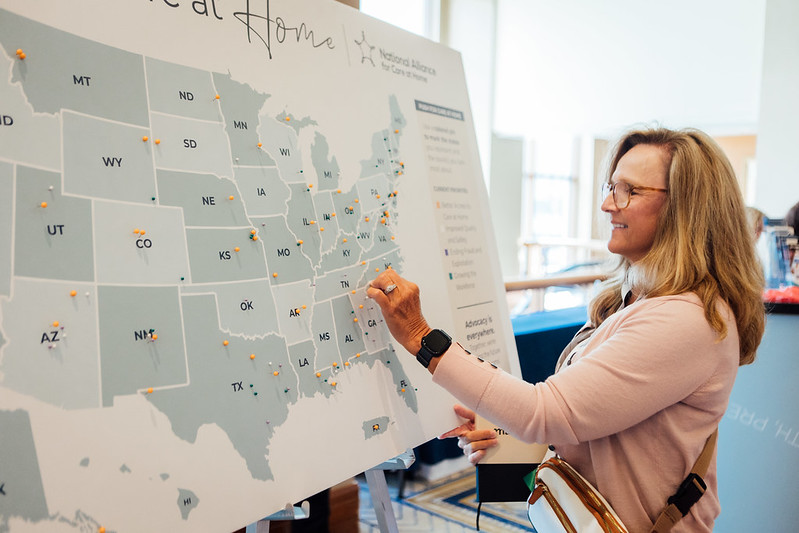
Alexandria, VA and Washington, DC, Sept. 16, 2026. – This week, more than 150 care at home advocates from across the country met with 285 congressional offices to discuss key legislative and regulatory priorities for expanding and protecting access to care at home. The meetings were part of the 2026 National Alliance for Care at Home Advocacy Week, an important opportunity to unite the entire care at home continuum under one voice.

Alliance Advocacy Week, now in its second year, offers a unique opportunity to bring together leaders, advocates, and supporters to amplify that home is where care happens, driving positive change and shaping the future of care to ensure that access to these essential services is protected and expanded.

"Our strength has always been our unity..." Jennifer Sheets

“This is a defining moment for care at home. When more than 150 advocates walk the halls of Congress together, speaking with one voice on behalf of patients, families, and providers, we send an unmistakable message. Care at home already has bipartisan support and recognition as a cost-effective, patient-preferred solution. As demand continues to grow, we are committed to being a strong partner with Congress to help federal policy grow with it,” said Jennifer Sheets, CEO of the Alliance. “Our strength has always been our unity, and Advocacy Week proves what we can accomplish when the entire continuum stands together to protect and expand access to the care people need, where they want to receive it most.”

Alliance Hosts Second Annual Advocacy Week

Key Issues

Advocates focused on five key issues during their congressional meetings:

End the home health and hospice provider moratoria and instead focus on implementing existing mechanisms to apply targeted, risk-based enforcement that roots out bad actors while protecting patients and legitimate providers.

Ensure that Medicare and Medicaid program integrity strategies are targeted and data-driven, focused on stopping fraudsters without harming legitimate providers or access to care, and supporting the Protecting Seniors and Stopping Fraudsters Act.

Stabilize Medicare home health payment rates by supporting the Medicare Home Health Payment Integrity and Protection Act to reverse an access crisis that has already left more than one-third of patients referred for home health without the care they need.

Protect and strengthen access to Medicaid HCBS by supporting policies and funding that let people receive care in their homes and communities, and that strengthen the direct care workforce making that possible.

Expand access to home care services by supporting the Credit for Caring Act to provide a federal tax credit of up to $5,000 to support family caregivers who provide 49 billion hours of unpaid care to relatives.

Alliance Hosts Second Annual Advocacy Week

Advocacy Week Activities

In addition to congressional meetings, Alliance Advocacy Week featured in-depth policy briefings, a training for first-time advocates, and a panel discussion with seasoned government affairs professionals. The Alliance celebrates another successful Advocacy Week on behalf of care at home providers across the country and looks forward to continuing its work with policymakers and key stakeholders.

# # #

About the National Alliance for Care at Home

The National Alliance for Care at Home (the Alliance) is the leading authority in advancing care in the home. We envision an America where everyone has access to the highest quality, person-centered healthcare wherever they call home. Through advocacy, education, and convening, we connect providers and stakeholders to strengthen care delivery across the home-based care continuum — spanning home care, home health, hospice, palliative care, and Medicaid home and community-based services. Learn more at www.AllianceForCareAtHome.org.

©2026 The National Alliance for Care at Home. This press release was issued by The National Alliance for Care at Home and is reprinted here with permission. For more information, please see contact information above.

The Alliance Responds to the Integrity and Protection Act

FOR IMMEDIATE RELEASE

Contact:                                                         Hannah Kristan
communications@allianceforcareathome.org
202-355-1647

The Alliance Celebrates the Introduction of the Medicare Home Health Payment Integrity and Protection Act of 2026

Alexandria, VA, August 7, 2026. Today, the Alliance applauds the introduction of the Medicare Home Health Payment Integrity and Protection Act of 2026 (S.B. 5250) by Senator Collins (R-ME) and Senator Blackburn (R-TN). This important piece of legislation will provide core payment integrity reforms by correcting the Centers for Medicare & Medicaid Services’ (CMS) flaws in calculating Medicare rate updates, while also streamlining program integrity measures to target fraud concerns early, stopping bad actors from entering the Medicare program. Critically, this legislation does not rely on sweeping enforcement strategies which risk further restricting access to care for Medicare beneficiaries and causing unintended harm to legitimate providers.  

The Medicare Home Health Payment Integrity and Protect Act seeks to restore the Medicare home health rate to what it would have been without consecutive years of compounding cuts. Those cuts were built on data entirely unrelated to the payment system adopted in 2020, along with data tainted by the inclusion of fraudulent providers in the rate analysis. This is an important step in modernizing the home health benefit, ensuring that beneficiary access is not disrupted by providing payment rates that better reflect the true cost of care. 

The program integrity reforms included in this legislation build on the industry supported bill from Representative Beth Van Duyne in the Protecting Seniors and Stopping Fraudsters Act (H.R. 8883), which gives CMS stronger tools to combat healthcare fraud without imposing unnecessary burdens on legitimate providers.

Medicare Advantage Stock Trump

“The National Alliance for Care at Home applauds the introduction of the Medicare Home Health Payment Integrity and Protection Act of 2026 by Senator Collins. This bill corrects longstanding flaws in home health reimbursement and takes a meaningful step toward a home health benefit that is stable and built for how care is delivered today. We strongly support the bill for its payment reforms, as well as measures to protect patients and preserve the integrity of the Medicare home health benefit.”

Jennifer Sheets

CEO, National Alliance for Care at Home

Sheets continues, “Consistent with our community’s commitment to provide the highest-quality, person-centered care in the home, we support the bill’s goal to strengthen access while focusing on targeted oversight, protecting the legitimate providers who serve patients every day. We look forward to working with Senator Collins, a long-time champion of care at home, to build support for this important and timely legislation.”

“When billions of dollars are improperly siphoned from the Medicare home health program, this can undermine the integrity of the payment system used to reimburse legitimate providers and threaten care for the seniors who depend on it. I have long been a strong supporter of home health care, which allows millions of Americans to remain in the comfort, security, and privacy of their own homes, while helping to avoid unnecessary hospitalizations and nursing home admissions,” said Senator Collins. “Fraudulent home health providers harm beneficiaries and diminish reimbursements for honest agencies that are already confronting workforce shortages and rising costs. My legislation would give CMS stronger tools to stop fraud before payments are made and prevent fraudulent spending from distorting the data used to reimburse honest agencies for medically necessary care.”

The Alliance will continue to serve as a key partner to lawmakers and regulators working to reform and protect the Medicare home health benefit, ensuring that payment rates better reflect the true cost of care.

# # #

About the National Alliance for Care at Home

The National Alliance for Care at Home (the Alliance) is the leading authority in advancing care in the home. We envision an America where everyone has access to the highest quality, person-centered healthcare wherever they call home. Through advocacy, education, and convening, we connect providers and stakeholders to strengthen care delivery across the home-based care continuum — spanning home care, home health, hospice, palliative care, and Medicaid home and community-based services. Learn more at www.AllianceForCareAtHome.org

© 2026 This press release was sent to The Rowan Report from the National Alliance for Care at Home and is reprinted with permission. For more information or to request permission to use this content, see contact information above.

LeadingAge Reacts to the Integrity and Protection Act

Leading Age React to Integrity and Protection Act

FOR IMMEDIATE RELEASE

Contact:                              Lisa Sanders
lsanders@leadingage.org
202-508-9407

PACE LeadingAge MA Reform

LeadingAge Statement on the Medicare Home Health Payment Integrity and Protection Act of 2026

August 7, 2026 Washington, DC—Statement from Katie Smith Sloan, president and CEO, LeadingAge, the association of nonprofit and mission-driven providers of aging services, including home health, on the Medicare Home Health Payment Integrity and Protection Act of 2026, recently introduced by Senator Susan Collins (R-ME):

“Access to health care and services is an important benefit today, as America grows older—by 2050, adults age 65 and older will increase from 17% to nearly 25% of the population. What’s more, care at home is what people prefer and it also delivers strong patient satisfaction and quality outcomes. Yet the valuable Medicare home health benefit is under threat. Senator Collins’ bill rightly seeks to rectify two contributors to that unfortunate situation: bad actors seeking to exploit the program, and…years of reductions due to a flawed methodology. “

Katie Smith Sloan

President and CEO, LeadingAge

Sloan continued, “A longtime champion of Medicare home health, Senator Collins appreciates the shortcomings of current payment approaches; we are particularly encouraged by the bill’s recognition that the standard prospective payment amount requires a recalibration. 

The Centers for Medicare and Medicaid Services’ (CMS) patient-driven groupings model (PDGM), in place since 2020, applies permanent and temporary payment adjustments, as required by Congress, premised on isolating “assumed versus actual” behavior change. The widely recognized problem is that in practice, neither CMS nor any other stakeholder, has managed to isolate the specific behavior due to PDGM from other factors that have also changed over the same time frame: patient acuity, referral patterns, staffing markets, the shift in post-acute utilization, potential fraud, and the lasting effects of the public health emergency.  

LeadingAge Reacts to Integrity and Protection Act

Rather than continue use of the problematic behavioral adjustments methodology, it makes sense to set a rate that reflects the patients agencies actually serve, and pause further assumption-driven adjustments. Home health providers need this relief, and the older adults and families who depend on care at home need the stability and access sensible rate-setting would deliver. 

We appreciate Senator Collins’ leadership in presenting a much-needed reset of the Medicare home health payment to promote its stability and ensure access. 

In addition, we also share the desire to address fraud in this setting. LeadingAge has long expressed concern about the increase of home health providers in Los Angeles County.  

This bill’s oversight provisions are reasonable, appropriately targeted policies that would help maintain the benefit’s integrity. Those, along with the important proposed payment changes, will help to ensure support for legitimate providers—including our nonprofit and mission-driven members. We look forward to working with Senator Collins to advance this legislation.”

About Leading Age

We represent more than 5,300 nonprofit and mission-driven aging services providers serving older adults and touching millions of lives every day. From our national headquarters in Washington, DC, and in collaboration with our state partners representing members active in 50 states, the District of Columbia, and Puerto Rico, we use advocacy, education, applied research, and community-building to make America a better place to grow old. Our membership encompasses the entire continuum of aging services, including skilled nursing, assisted living, memory care, affordable housing, retirement communities, adult day programs, hospice, Programs of All-Inclusive Care for the Elderly (PACE), and home-based care. We bring together the most inventive minds in the field to lead and innovate solutions that support older adults wherever they call home. For more information, visit leadingage.org.

© 2026 This press release was sent to The Rowan Report from LeadingAge and is reprinted with permission. For more information or to request permission to use this content, see contact information above.

Three Choices at the End of Life

by guest author Barbara Karnes, RN

Cure, Life-Sustaining, or Comfort Care

When someone is facing a life-threatening illness, they and their loved ones are often asked to make medical decisions they never expected to face. Unfortunately, most of us don’t fully understand the choices before us. Knowing the difference between cure, life-sustaining treatment, and comfort care can help you make decisions that honor the kind of life – and death – you want.

Cure, life-sustaining treatment, and comfort care. These are the three paths available when we are faced with a life-threatening illness.

Cure

Cure means providing a return to a “normal” functioning life. I put normal in quotes because the word can be misleading. What is normal for one person may not be normal for another. Cure implies being able to participate in and enjoy the activities of everyday living. It means the malady is gone or controlled.

Life-Sustaining Treatment

Life-sustaining treatment means keeping the physical body alive by whatever means are deemed necessary. Many people refer to these treatments simply as “life support.” They can include artificial nutrition and hydration, ventilators, dialysis, respirators, and other advanced medical procedures. The goal becomes preserving life, even when the quality of life is greatly diminished.

Quality Improvement Project Hospice Domains

Comfort Care

Comfort care focuses on the quality of the life you are living rather than simply the length of that life. It includes physical care along with emotional, mental, and spiritual support. Comfort care addresses what is most important to your well-being now that your body is no longer able to meet all of your needs. It also guides and nurtures your family and those closest to you as everyone prepares for the end of life while continuing to live fully each day.

"Fix" or Provide Care?

We often get so caught up in getting “fixed” at any price that we lose sight of what our goal really is. Treatment does not necessarily mean cure. Yet most of us assume that if we do everything possible, we will get better. Sadly, too often we sacrifice the quality of the life we have today while pursuing a cure that may no longer be possible.

When deciding between cure, life-sustaining treatment, or comfort care, information and knowledge are vital components to making decisions. We need honest conversations about the likely outcome of treatment, the chances of success, life expectancy, and quality of life. Once you’ve had those conversations and decided what kind of living is most important to you, share those wishes with your physician, your family, and those closest to you—and put your decisions in writing.

There is no right or wrong choice. There is only the choice that best reflects your values and how you want to live the time you have.

# # #

Tim Rowan The Rowan Report

Barbara Karnes, RN, is an award-winning end-of-life educator, award-winning nurse, NHPCO Hospice Innovator Award winner 2018, and 2015 International Humanitarian Woman of the Year

While at the bedside of hundreds of people during the dying process, Hospice Pioneer Barbara Karnes noticed that each death was following a near-identical script. Each person was going through the stages of death in almost the same manner, and most families came to her with similar questions. These realizations led Barbara to sit down and write Gone From My Sight, the “Little Blue Book” that changed the hospice industry.

Gone From My Sight is the original, and remains the most widely used, patient/family educational booklet on the signs of approaching death. It has been in print continuously since 1985 and has sold over 35 million copies worldwide. With its publication and distribution, Barbara created one of the most important tools in the end-of-life movement today.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

The Broadway Secret

by Aaron Marcum

The Home Care Back Stage

The Broadway secret every home care owner needs to know

A few years ago, I took my daughter to see “Wicked” in London’s West End.

From the moment the lights dimmed, we were transported. The performances were flawless, the choreography mesmerizing, and the vocals spine-tingling. For two and a half hours, we sat captivated by what appeared to be theatrical magic.

It looks like magic

But here’s what struck me as I watched: what we were experiencing wasn’t magic at all. It was the result of an incredibly sophisticated operation happening behind that curtain—an operation most audience members never think about.

Dan Sullivan, founder of Strategic Coach, calls this the “Front Stage” and “Back Stage” of your business. And it’s a framework that every home care owner needs to understand.

The Home Care Back Stage

What Makes Broadway, Broadway?

When you pay for a West End ticket, you’re not just paying for talented actors. You’re paying for a lighting crew coordinating hundreds of cues per show, costume designers managing dozens of quick changes, sound engineers balancing multiple wireless microphones in real-time, stage managers calling hundreds of technical cues with split-second precision, and a production team that rehearsed for months before opening night.

The Front Stage—what the audience sees—only shines because of an exceptional Back Stage.

Your home care business has the same dynamic

Front and Center

In our industry, the Front Stage is your care professional arriving at Mrs. Johnson’s home at 9 AM. It’s the smile, the gentle assistance with morning medication, the conversation during breakfast, and the compassionate help with bathing and dressing.

That’s what your clients see. That’s what their families remember. That’s how your business gets judged.

But we all know that caregiver showing up prepared, on time, and trained isn’t an accident.

Behind the Scenes

Your Back Stage makes it possible: 

  • Care Coordination ensures the right caregiver with the right skills is scheduled for the right client. When this system fails, clients feel it immediately.
  • Billing Systems that work seamlessly mean caregivers get paid accurately and on time—because nothing destroys Back Stage morale faster than payroll errors.
  • Compliance Infrastructure keeps you operating legally and safely, protecting both your clients and your business.
  • Recruitment and Hiring processes that attract quality candidates. With projections showing a national shortage of 151,000 caregivers by 2030 and 355,000 by 2040, your Back Stage recruiting determines whether you have anyone to put on the Front Stage. As a side note, I personally believe the shortages are greater than this.
  • Training Programs that don’t just check boxes but actually prepare caregivers for real situations. The 2025 Activated Insights Benchmarking Report found that agencies offering 8+ hours of orientation training had median revenue of $2.4 million compared to $2.03 million for those with 3 or fewer hours.
  • Retention Strategies because the average caregiver costs $2,600 to replace Activated Insights. Your Back Stage culture determines whether caregivers stay or leave.
Home Care Broadway Back stage
Home Care Broadway back stage

The Numbers Tell a Sobering Story

Here’s the reality: the home care industry’s turnover rate reached 79.2% in 2023 Home Health Care News—the highest it’s been in five years. Think about that. In an agency with 100 caregivers, you’re replacing nearly 80 of them every single year.

But it gets worse. Nearly four out of five caregivers leave their job within the first 100 days of employment. That means the caregivers you just spent weeks recruiting, screening, and training? Most of them won’t even make it through their first three months.

When your Back Stage is weak, these statistics become your reality.

The "Community Theater" Problem

We’ve all attended shows where you could tell the Back Stage was struggling.
Maybe you’ve seen a local production where an actor missed their entrance, the lighting was off, a scene change took too long, or the sound cut out.

You couldn’t see the Back Stage problems, but you absolutely felt them.
The same thing happens in home care.

A weak back stage

When your Back Stage is weak:

  • Caregivers show up late (or not at all) because scheduling is chaotic
  • Families receive incorrect bills because systems are disconnected
  • Care quality suffers because training is inconsistent
  • Your reputation erodes one Front Stage failure at a time

Your clients might not know your payroll system crashed or that your care coordinator called in sick for the 4th time this month, but they experience the consequences.

The Broadway Standard Question

So here’s the question every home care owner must ask:

Is your business operating at Broadway standards, or community theater? Be honest.

When you look at your Back Stage operations:

  • Can your care coordinators instantly access complete client information?
  • Do your caregivers have clear protocols for every situation they might encounter?
  • Is your billing accurate enough that families rarely question an invoice?
  • Do you have documented processes, or is everything “in someone’s head”?
  • Could your business run smoothly if your top coordinator was suddenly unavailable?

The best home care agencies—the ones with waiting lists and stellar reputations—aren’t just lucky. They’ve built Broadway-quality Back Stage operations.

They’ve invested in systems, training, and processes. They’ve documented their playbook. They’ve made the Back Stage so strong that the Front Stage can shine consistently, every single day.

Because here’s what I learned watching “Wicked”: excellence isn’t about one amazing moment. It’s about a thousand excellent decisions that happen when no one is watching. 

The question is: what's happening in your Back Stage?

Want to build your Broadway-worthy Back Stage?

Stay in the know with strategies, insights, and practical resources designed specifically for home care owners. Subscribe to receive updates, newsletters like this, and tools that will help you elevate both your Front Stage performance and Back Stage excellence. Because your caregivers—and your clients—deserve a five-star experience every single time.

# # #

Aaron Marcum Home care and Broadway

Aaron Marcum is an entrepreneur and thought leader who has dedicated his career to transforming the home care industry and nurturing business leaders.

As the founder of Home Care Pulse (now Activated Insights), he pioneered the Best of Home Care® program, revolutionizing quality standards in senior care across North America. His expertise as a Certified Blue Ocean Strategy practitioner and former Certified EOS Implementer has helped shape some of home care’s most respected brands.

© 2026 This article originally appeared in Aaron Marcum’s newsletter and is reprinted here with permission. For more information or for permission to use this material, please contact Aaron Marcum.

Hiring and Retaining Professional Caregivers

by Roger McManus, MBA

Hiring and Retaining Professional Caregivers

What Really Keeps People in This Work

People who work in home‑based care, whether licensed home health clinicians or trained home care aides, do something unusual in the healthcare world. They walk into a stranger’s home and step into the middle of that person’s daily life. Their role is to try to help them stay, or get, healthy, stable, safe, and dignified. All this happens in someone else’s environment. That fact impacts the hiring and retention challenge for agencies.

While somewhat overlapping, home health and home care are different fields. Home health visits are shorter, clinically focused, and built around medical goals. Home care shifts are longer, non‑medical by law, and often revolve around companionship, safety, and daily living support. But the shared denominator, the home environment, creates a common reality. Agencies must find and keep people who can handle the emotional, practical, and interpersonal demands of working inside a client’s private world.

Long-term retention depends significantly on the caregiver’s ability to adapt with a chameleon-like mindset. 

The Home Environment Changes Everything

A hospital or clinic has structure; a home does not. Workers deal with cluttered living rooms, anxious adult children, and unpredictable pets. They see clients who may be having a good day, a bad day, or something in between. They have to be able to read the situation, adjust their tone, and figure out how to help without dominating.

This is not a skill you can measure with a résumé alone. Agencies that hire well look beyond credentials. They look for temperament — calmness, respect, patience, and the ability to stay professional even when the environment may be anything but.

Retention starts with hiring people who can work in this setting.

Brown v D.C.
Hiring and Retaining caregivers

Why Turnover Hits Home Based Care Harder

Turnover in this field isn’t just inconvenient. It’s disruptive in ways that office‑based healthcare rarely experiences.

When a home health clinician leaves, cases get reshuffled, documentation gets delayed, and continuity of care suffers. When a home care aide leaves, long‑standing client relationships can collapse overnight. The Patient is most aware.  Families notice. Referral partners notice. 

Workers leave for predictable reasons:

  • Home health clinicians may feel isolated or overwhelmed by documentation and case complexity.
  • Home care aides may feel undervalued or stuck in roles with no visible progression.
  • Both groups may struggle with inconsistent schedules, long drive times, or emotionally draining cases.

Retention improves when agencies acknowledge these realities instead of treating turnover as “just part of the industry.”

Creating a Support System That Actually Works

The best retention strategies aren’t flashy. They’re consistent, practical, and rooted in what workers experience every day.

Home health clinicians need clinical leadership that is reachable. Not a voicemail box. Not a once‑a‑week check‑in. They need someone who answers the phone when a wound looks worse, when a medication list doesn’t match the chart, or when a family is spiraling. Caregivers knowing they have that backup reduces burnout more than any bonus ever will.

Home care aides need respect and inclusion. They may not have medical licenses, but they are the ones who see the client’s real daily life. Agencies that treat aides as essential contributors, not interchangeable labor, see stronger loyalty and longer tenure.

Across both groups, communication is the glue. Workers stay when they feel connected to a team that listens and responds. 

Logical Rewards

Incentives That Make Sense in the Field

Many agencies try bonuses, gift cards, or occasional “thank you” events. Those gestures are fine, but they rarely change long‑term behavior. Logical rewards do.

These incentives tie directly to the realities of home‑based work:

  • Readiness bonuses for workers who reliably take short‑notice visits.
  • Incentives for on‑time arrival, complete documentation, or strong client feedback.
  • Skill‑tier pay ladders that reward additional certifications or specialized training.
  • Continuity bonuses for maintaining long‑term client relationships without disruption.

These rewards reinforce the behaviors that stabilize the agency. They’re not random. They’re strategic.

Onboarding and Training:

The First Impression That Never Goes Away

Retention begins the moment a new worker walks through your door. A chaotic onboarding process sends a message that “this agency is disorganized.” A clear, supportive onboarding process sends the opposite message that “we know what we’re doing, and we want you to succeed.”

Home health clinicians need onboarding that covers real‑world clinical scenarios, documentation expectations, and the unpredictable nature of home visits. Home care aides need onboarding that prepares them for communication challenges, safety issues, and the emotional realities of working with seniors.

Ongoing training matters just as much. Workers stay when they see a path forward, something to grow into, not just a job to survive.

Retention Is Not HR, It is Strategy

Agencies that retain their workers don’t just solve staffing problems. They build a competitive advantage. Families trust agencies whose workers stay. Referral partners prefer agencies that don’t constantly reshuffle cases. Regulators appreciate agencies with consistent documentation and stable clinical outcomes.

Retention is not a side project. It is a core business function.

# # #

Roger McManus

Roger McManus is the author of several books on entrepreneurship, including “Entrepreneurial Insanity in the Home Care Business,” which he co-wrote with Tim Rowan. He advises Home Care owners and HR professionals on techniques for recruiting, retaining, and rewarding caregivers.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This excerpt was provided to The Rowan Report and is printed with permission. 

The Caregiver’s Mindset

by Roger McManus, MBA

This chapter is part of the upcoming book, The Intuitive Caregiver. It is designed to strengthen in-home caregiving skills with clear, practical, real‑world guidance.

The Caregiver's Mindset

Professional care begins long before knocking on the door

Caregiving does not start with a task list, nor does it begin when you help someone stand, prepare a meal, or assist with bathing. It begins the moment you walk through the door — with your attitude, your awareness, and the way you choose to show up.

A caregiver’s mindset is the foundation of every caregiving activity that follows. Yes, skills matter. Sure, training matters. But the mindset you bring into someone’s home determines whether your presence feels calming or stressful, respectful or intrusive, steady or unpredictable.

This chapter helps you understand what it means to “show up” as a professional caregiver — not just in what you do, but in how you think, how you observe, and how you treat the person and their home.

Enter with Humility and Respect

Professional caregivers enter with humility by:

  • looking before touching
  • asking before moving anything
  • treating every object as meaningful
  • remembering that routines exist for reasons you may not yet understand
  • Even something as simple as moving a chair or adjusting a blanket can feel like an intrusion if you do it without asking. Respect for the home is the first sign of respect for the client.

Caring Begins with Attitude

Your Job is Stability, Not Control

Many older adults feel vulnerable when someone new enters their home. They may worry about losing independence, privacy, or dignity. They may fear being judged. They may feel embarrassed about needing help.

Your role is not to take over.
Your role is to create stability.

Stability comes from:

  • predictable routines
  • calm communication
  • steady follow‑through
  • respecting the client’s pace and preferences
  • Caregiving is not about being fast. It’s about being reliable. When you move calmly and consistently, the client feels safer — and safety leads to cooperation.

Entering Someone Else’s World

A client’s home is not your workplace.
It is their private space — the place where they feel most themselves.

When you enter that space, you are stepping into someone’s history, habits, routines, and memories. You may see clutter, unusual décor, or ways of doing things that don’t match your own. None of that is your business (though it may suggest you send your agency’s Occupational Therapist to professionally assess safety issues). Your job is not to judge the home. Your job is to respect it.

You Are A Guest, Not A Manager

Even when a client needs significant help, the home remains theirs. You are there to support, not to run the household.

Professional caregivers avoid the trap of “fixing” everything. Instead, they:

  • collaborate rather than dictate
  • offer choices rather than instructions
  • adapt to the client’s rhythms rather than imposing their own
  • For example:
    Instead of saying,
    “Let’s get you dressed now.”
    You might say,
    “Would you like to get dressed before breakfast or after?”
    Choices restore control.
    Control restores dignity.
    Dignity builds trust.

Your Work is Emotional First, Before Physical

Caregiving is not just a list of tasks. It is a relationship.

Many clients are grieving — not always the loss of a person, but the loss of abilities, independence, or identity. They be frustrated by what their body can no longer do. They may be embarrassed to need help. They may be afraid of what comes next.

Your presence can either increase that fear or reduce it.

Emotional safety is the foundation of physical care. Caregivers support emotional safety by:

  • listening without judgment
  • acknowledging feelings without trying to “fix” them
  • offering reassurance through tone and patience
  • giving people time to process and respond
  • You are not just helping with daily activities.
    You are helping someone navigate a changing life.

Professionalism is A Daily Practice

Professional caregivers represent their agency, their training, and the caregiving profession itself. Clients notice everything — and they should. They are trusting you with their home, their health, and their dignity.

Professionalism shows up in:

  • punctuality
  • appearance
  • communication
  • boundaries
  • documentation
  • confidentiality

It also shows up in the small things:

  • put your phone away
  • stay focused on the client
  • avoid prying, personal conversations
  • maintain a calm presence even when the day is difficult

Professionalism is not about being perfect. It is about being consistent.

Understanding the Client's Reality

Before you ever walk through the door, the client is already living with pressures, fears, and adjustments to dependence that you may not see.

Loss of Control Is the Central Theme

Most clients do not ask for help because they want it. They ask because they no longer have a choice. That loss of control can feel humiliating, frightening, or deeply unfair.

Even small tasks — tying shoes, opening containers, getting out of a chair — may require assistance for the first time since childhood. Every request for help carries some emotional weight. Feeling like a helpless child carries more.

The Home Is Their Last Stronghold

For many clients, the home represents independence, identity, and safety. When a caregiver enters that space, the client may worry that:

  • their privacy will disappear
  • their routines will be disrupted
  • their preferences will be ignored
  • their home will no longer feel like their own

Respect for a person’s home environment is not optional — it is foundational.

Judge Not...

A caregiver may simply be observing the environment to understand needs, but the client may interpret that as criticism.

They may think:

  • “My home is a mess.”
  • “I’m not doing enough.”
  • “They must think I’m failing.”

Neutral language and gentle pacing reduce this fear.

Fear of Decline Is Always Present

Even when clients don’t say it, they are often thinking:

  • “What happens when I get worse?”
  • “Will I lose my home?”
  • “Will I become a burden?”

You cannot remove these fears, but you can avoid triggering them. Predictability and calmness go a long way.

The First Visit Sets the Tone

A caregiver’s first visit is more than an introduction — it defines the entire relationship. Clients quickly determine whether you will make them feel safe, respected, and understood.

Arrive Calm, Prepared, and Unhurried

Your arrival should feel like relief, not disruption.

Introduce Yourself Clearly

Clients should never have to guess who you are or why you’re there.

Observe Before You Act

The first visit is not the time to reorganize or “improve” anything. It is the time to learn.

Ask Permission for Everything

Even small actions require permission. Asking restores control.

Match the Client’s Pace

Your pace should never exceed theirs.

Keep the First Visit Simple

The goal is rapport, understanding, and emotional safety — not efficiency.

Heart of the Chapter

Caregiving begins with a mindset, not a task.
Caregiving begins with humility, awareness, and respect.
Caregiving begins with the attitude that you are entering someone else’s world — and your presence can either bring calm or create stress.

When you show up with steadiness, patience, and professionalism, you create the foundation for everything that follows.

# # #

Roger McManus

Roger McManus is the author of several books on entrepreneurship, including “Entrepreneurial Insanity in the Home Care Business,” which he co-wrote with Tim Rowan. He advises Home Care owners and HR professionals on techniques for recruiting, retaining, and rewarding caregivers.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This excerpt was provided to The Rowan Report and is printed with permission. 

Response to HHS Reports

FOR IMMEDIATE RELEASE

Contact:                       Colleen Knudsen
cknudsen@leadingage.org
202-508-1215

Post-Acute Care Medicare Advantage Coalition Statement on OIG Reports Confirming Barriers to Post-Acute Care in Medicare Advantage

Washington, D.C, June 16, 2026. The Post-Acute Care Medicare Advantage (PAC MA) Coalition issued the following statement in response to the U.S. Department of Health and Human Services (HHS) Office of Inspector General’s (OIG) two new reports, The Three Largest Medicare Advantage Organizations Denied Requests for Long-Term Acute Care and Inpatient Rehabilitation at Some of the Highest Rates and Medicare Advantage Organizations Overturned Nearly All Appealed Prior Authorization Denials for Skilled Nursing Facility Admission, Raising Concerns About Initial Denials:

Post-acute care MA Coalition

Coalition Statement

The PAC MA Coalition has long championed critical yet commonsense and necessary reforms to ensure Medicare beneficiaries’ access to medically necessary care across all post-acute settings. These June 2026 OIG reports provide important, independent confirmation of what providers and Medicare beneficiaries have experienced for years: Medicare Advantage (MA) plans are using prior authorization (PA) and similar tactics to restrict beneficiaries from receiving the services that Medicare Advantage Organizations (MAO) are legally required to provide. 

Across the post-acute care (PAC) continuum, OIG found concerning denial patterns, wide variation of the rate of denials among MA organizations, and high rates of successful appeals. Even when a denial is later overturned, the patient may still have faced unnecessary care delays, a prolonged hospital stay, an interruption in recovery, or placement in a less appropriate care setting. Given each PAC setting’s distinct role and value in the rehabilitation continuum, these outcomes can cause significant disruptions in patients’ recovery trajectory and place patients at higher risk for complications and readmissions – all of which produce poorer outcomes and increase costs for the Medicare program. 

For Medicare beneficiaries recovering from serious illness, injury, surgery, stroke, or other complex medical events, timely access to the right post-acute care setting is essential. These decisions are not simply administrative; care in the appropriate setting can affect whether a patient regains function, avoids complications, returns home safely, or receives the services needed to recover altogether. 

The Coalition is also concerned by OIG’s findings regarding third-party contractors and vendors involved in PA decisions. MAOs remain responsible for ensuring that their contractors, which may deploy algorithmic or artificial intelligence-supported tools in PA decision-making, comply with Medicare coverage rules. High denial overturn rates should prompt closer CMS oversight of whether these entities are applying Medicare standards accurately and enforcement with meaningful penalties when there are patterns of non-compliance. 

The OIG reports underscore the need for better data, transparency, and stronger accountability. The Coalition urges the Centers for Medicare and Medicaid Services (CMS) to implement OIG’s recommendations to collect detailed, request-level PA data–including standardized service type, contractor involvement, denial rationales, decision timelines, appeal outcomes, and information on continued-stay requests. CMS should make these data publicly available and also examine why denial and overturn rates vary so widely across plans and contractors and take corrective action, where appropriate. 

The Coalition further urges OIG and CMS to conduct a similar review of MA practices affecting home health services. Home health providers report that even when care is approved, MA plans frequently authorize fewer visits than clinically appropriate and reimburse at rates significantly below traditional fee-for-service (FFS) Medicare. As a result, patients may be left without the full scope of services they need to recover safely at home. 

MA plans are required to provide access to Medicare Part A and Part B services in a manner comparable to traditional FFS Medicare. The OIG reports make clear that stronger oversight, greater transparency, and more consistent enforcement are needed to ensure MA beneficiaries receive the post-acute care they are entitled to under Medicare, in the most clinically appropriate setting. Our groups collectively applaud the OIG’s observation that, “as enrollment in Medicare Advantage continues to grow, so does the urgency and importance of ensuring that MAOs are delivering on the value that the Federal Government pays them to provide.” 

The PAC MA Coalition therefore stands ready to work with CMS, Congress, OIG, MA organizations, and other stakeholders to address PA, reduce unnecessary administrative burden to providers, ensure adequate payment, and protect timely access to medically necessary post-acute care. 

The PAC MA Coalition renews its request for CMS to standardize post-acute care prior authorization procedures across MA plans. Greater consistency, compliance, and accountability are needed to ensure decisions reflect traditional Medicare FFS standards. Expedited PA is essential so beneficiaries receive timely, medically necessary services and avoid unnecessary delays in recovery.”

# # #

About the PAC MA Coalition

Post-Acute Care (PAC) is made up of approximately 15,000 skilled nursing facilities (SNFs), 11,500 home health agencies (HHAs), 1,200 inpatient rehabilitation facilities (IRFs), and 370 long-term acute care hospitals (LTCHs), among other provider types.

The Post Acute Care Medicare Advantage (PAC MA) Coalition is comprised of LeadingAge, the American Health Care Association and National Center for Assisted Living (AHCA/NCAL), the American Medical Rehabilitation Providers Association (AMRPA), the National Alliance for Care at Home (the Alliance), the National Association of Long Term Hospitals (NALTH), and the Center for Medicare Advocacy. Together, the Coalition represents the interests of PAC providers and the Medicare beneficiaries who require their services.

The Coalition’s objective is to ensure Medicare beneficiaries enrolled in MA and Special Needs Plans (SNPs) receive comparable and timely access to Medicare Part A and B services as their Traditional Medicare counterparts, while also ensuring the financial viability of providers who participate in MA networks through adequate payment and reduced administrative burden.

© 2026 PAC MA Coalition. This press release was issued by LeadingAge and is reprinted with permission. For more information or to request permission to print, see contact information above.

Alliance Responds to CMS

FOR IMMEDIATE RELEASE

Contact:                                                            Hannah Kristan
communications@allianceforcareathome.org
202-355-1647

The Alliance Responds to CMS’s Announcement of Nationwide Enrollment Moratoria on Hospice and Home Health Providers

Washington, D.C, May 13, 2026. On May 13, the Centers for Medicare & Medicaid Services (CMS) announced a six-month national moratorium on hospice and home health enrollment in response to program integrity concerns within the Medicare programs. While the National Alliance for Care at Home (the Alliance) strongly supports efforts to root out bad actors who exploit these essential programs, undermine confidence in care at home, and threaten the patients and families who depend on it, the Alliance has long advocated for targeted strategies that distinguish between high-fraud markets and communities where fraud is not an identified problem and patients already face shortages of providers.

Concerns

The Alliance welcomes the Administration’s focus on combatting fraud, waste, and abuse and appreciates that CMS has indicated providers will still be able to conduct face-to-face recertification visits via telehealth during the enrollment moratorium, which will help avoid unnecessary care disruptions for patients and families. However, an enrollment moratorium does not distinguish between bad actors and compliant providers and will ultimately reduce competition and slow innovation. More importantly, an enrollment moratorium raises serious access-to-care concerns in areas where patient demand is growing or existing capacity is already strained, leading to longer wait times, reduced service availability, and fewer choices for patients – particularly in rural or underserved communities.

Less Severe Recommendations

Public reports show that fraud is concentrated in specific geographies and among specific actors, signaling that targeted reforms and oversight strategies are needed to identify and remove fraudulent entities from the Medicare program. The Alliance and other national organizations have repeatedly provided CMS with recommendations that focus on preventing bad actors from entering the Medicare and Medicaid programs and better leveraging existing tools to fight fraud without creating unnecessary burden for good-faith providers who are already meeting program requirements.  

Alliance responds to CMS moratoria

From the Alliance CEO

“The majority of home health and hospice providers deliver compliant, patient-centered, and clinically appropriate care to individuals with complex needs, often in their most vulnerable moments. CMS must use data-driven, risk-based program integrity measures and focus resources on boots-on-the-ground surveys and enforcement of existing oversight mechanisms that root out the blatantly bad actors without potentially limiting patient access to care or punishing high quality providers operating in good faith.” 

Jennifer Sheets

CEO, National Alliance for Care at Home

Final Thoughts

This moratorium, effective May 13, applies only to new providers and certain changes of ownership, and may be extended if CMS deems it necessary.  

The Alliance has been and will remain a proactive, constructive partner to Congress and federal regulators on program integrity efforts. The Alliance will continue to engage with the Administration on a path forward that holds bad actors accountable while protecting patient access to the safe, high-quality care at home they need and deserve. 

# # #

About the National Alliance for Care at Home

The National Alliance for Care at Home (the Alliance) is the leading authority in transforming care in the home. As an inclusive thought leader, advocate, educator, and convener, we serve as the unifying voice for providers and recipients of home care, home health, hospice, palliative care, and Medicaid home and community-based services throughout all stages of life. Learn more at www.AllianceForCareAtHome.org. 

©2026 by the National Alliance for Care at Home. For more information or to request permission to reprint, please see contact information above.
Purpose-Built AI: from Theory to Practice

by Isaac Greszes, Eleos

Purpose-Built AI

From Theory to Practice

This 4-part series has outlined how to evaluate, test, and use AI solutions, emphasizing outcome relevance, workflow fit in regulated environments, architectural scalability, and governance discipline. That framework was intentionally rigorous. In a market crowded with pilots and proofs of concept, it reflects the reality that AI outcomes are not accidental; they are the result of deliberate design choices.

This final chapter shares a real-life story of AI implementation using the Polaris AI Engine.

A Reference Implementation

One example of how these principles are applied in practice is Eleos’ Polaris AI engine.
Polaris was developed over more than five years to support regulated conversational care. Rather than relying solely on general-purpose language models, it combines commercial-grade multimodal infrastructure with proprietary clinical intelligence layers that encode documentation logic, reasoning patterns, and safety heuristics.

Purpose-Built AI Eleos Polaris

Key elements of this approach include:

  • Layered architecture, separating foundational AI capabilities from clinical logic and governance controls.
  • Expert-led refinement, with licensed clinicians continuously validating and updating clinical rules.
  • Application-layer tuning, allowing the system to improve without retraining on customer data.
  • Governance-by-design, with explicit boundaries around data use, monitoring, and risk management.

Clinical Control

Importantly, Polaris is not positioned as a fully autonomous system. Clinicians remain in control, using AI as a collaborative tool that reduces administrative burden while preserving clinical judgment.

This design reflects a broader principle: in regulated care environments, trust and adoption depend as much on restraint and transparency as on technical capability.

Your content goes here. Edit or remove this text inline or in the module Content settings. You can also style every aspect of this content in the module Design settings and even apply custom CSS to this text in the module Advanced settings.

Applicability in Care at Home

Care at home workflows differ across home health, hospice, and other palliative care settings. Documentation standards, visit structures, and regulatory requirements vary. Validation within each context remains essential.

At the same time, platforms built to handle high-variability conversational care share structural advantages when entering care at home environments; they:

  • Are designed to operate in unstructured, field-based settings.
  • Encode clinical reasoning rather than relying on generic text generation.
  • Incorporate governance and safety controls suited to regulated care.

For executives navigating pilot fatigue, this distinction matters. Platforms designed as infrastructure — rather than experiments — are better positioned to adapt responsibly as care at home AI adoption matures.

Final Thoughts

AI is here and it’s here to stay. Care at home agencies need to look to AI solutions in order to stay competitive. Knowing which solutions to review, what to look for, and how to move beyond the pilot phase begin with finding Purpose-Built Ai. Many thanks to our friends at Eleos for their expertise on this topic. Read the 4-part series.

# # #

About Eleos

At Eleos, we believe the path to better healthcare is paved with provider-focused technology. Our purpose-built AI platform streamlines documentation, simplifies compliance and surfaces deep care insights to drive better client outcomes. Created using real-world care sessions and fine-tuned by our in-house clinical experts, our AI tools are scientifically proven to reduce documentation time by more than 70% and boost client engagement by 2x. With Eleos, providers are free to focus less on administrative tasks and more on what got them into this field in the first place: caring for their clients.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com