Viventium | Apploi: CEO Interview

Admin

by Kristin Rowan, Editor

Viventium CEO Interview: Adam Lewis

From time to time, The Rowan Report invites our partners to participate in a video interview. Earlier this year, we sat down with Viventium CEO Navin Gupta. Last week, we had the pleasure of speaking with Adam Lewis, Founder of Apploi and General Manager of Talent and Workforce Management at Viventium.

Adam brings years of experience and passion for care at home to Viventium after its acquisition of Apploi earlier in 2026. The Viventium and Apploi merger creates a seamless, end-to-end management platform from recruitment to the first paycheck.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com


 

Private Duty Fraud Enforcement

Admin

by Elizabeth E. Hogue, Esq.

The Future of Private Duty/Home Care

It Begins with Fraud Enforcement

Use of private duty/home care services continues to increase. It has become increasingly clear, however, that companies will not be permitted to care for patients who need these services without considerable additional oversight.

The proverbial “bottom line” is that private duty/home care companies will be under greater scrutiny and regulation. The instances of gross mistreatment of patients, some of which we have described in previous articles, are too shocking and lurid. And caregivers about whom lip service is given about their need for support have been mistreated by private duty companies.

And Then There's This:

The feds are convinced that there is rampant fraud in state Medicaid Programs to the tune of millions, if not billions, of dollars that has not been addressed. The number of fraud strike forces, task forces, etc. targeting companies that provide services to Medicaid recipients are now too numerous to count.

Fraud enforcement is definitely “in fashion” and enforcers are eager to put private duty/home care companies in the color orange! If this a fashion statement you want to make?

To Illustrate:

The National Fraud Enforcement Division of the U.S. Department of Justice (DOJ) recently announced that it has prosecuted 6200 defendants who collectively billed federal health care programs, including Medicaid, TriCare, the VA and others, $45 billion.

In a press release issued on August 4, 2026, the Division stated:

“Home care fraud is everywhere, and the victim is all of us taxpayers. Medicaid claims date and the experience of veteran prosecutors all point to the systematic exploitation of reimbursable home care programs….Today. we sound the alarm on the scale of this fraud by announcing some truly egregious cases, in which numerous people are charged with filing fraudulent claims for caregivers who were not actually providing home care services, but in fact were dead, in prison, or trafficking drugs. This racket ends today.”

And There's More!

“Let today’s announcement be a warning to those engaging in similar activity: if you seek to exploit our health care systems for personal profit, you should expect the FBI and our partners to uncover your scheme and bring it to an end. Every dollar stolen through fraud is a dollar diverted from patient care, and the FBI will continue its work to safeguard the public’s trust and hold accountable those who abuse these vital programs.”

Finally the press release promises that enforcers “…will pursue anybody who seeks to profit at the expenses of American taxpayers, regardless of whether the wrong doing is in the boardroom or in the sickroom.”

In other words, it’s not just the perpetrators who will be punished. The companies, owners and managers will also face punishment.

So, what are some of the offenses pursued so far?

Private Duty Fraud Enforcement

One of the defendants was captured on tape:

”This home health care is the best kept secret…I made a buck plus (each of) the last five years. That’s a half million dollars… ain’t checking on nobody.”

It may be tempting for owners and managers to say: “That’s on them.” Not so! Companies and management will be held accountable for the actions of their employers and contractors.

Private duty/home care companies will see a tsunami of regulation. Use of fraud and abuse prohibitions is just the beginning.

# # #

Elizabeth E. Hogue, Esq The Rowan Report

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2026 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. 

HHAeXchange Launches RCM Services

Admin

by Kristin Rowan, Editor

HHAeXchange Announces RCM Services

An Interview with Phil Feldman

In April of 2026, HHAeXchange unveiled their new end-to-end Revenue Cycle Management (RCM) service. HHAeXchange is a leading provider of homecare program management designed for Medicaid Home and Community-Based Services. (HCBS).

Addressing Top Concerns

HHAeXchange’s 2025 Provider Voice Survey asks homecare agencies about the pain points facing the industry. Administrative workload and cost are significant areas of concern for homecare agencies, cited by 41% of providers. RCM services address these concerns by removing administrative tasks from agencies, freeing up personnel to focus on growth, community outreach, referrals, and caregiver training. 

“Homecare providers are navigating diverse payers, rising costs, growing administrative demands, and an increasingly complex financial and regulatory environment. RCM Services relieves agencies of the operational burden of billing and collections while improving cash flow and business performance. By offloading revenue cycle management to experts who deeply understand homecare and the HHAeXchange platform, agencies gain clarity, efficiency, and more time to focus on care.”

Paul Joiner

CEO, HHAeXchange

From Submission to Resolution

End-to-end RCM services handle the full revenue cycle. The RCM Services team at HHAeXchange handles everything from the initial claim submission to handling discrepancies, resolving rejections, appealing denials, and shortening the cycle of aging receivables.

Improved Cash Flow

RCM services go beyond billing and collections. HHAeXchange uses operational intelligence to track denial trends, authorization issues, and payer challenges. With these issues addressed at the beginning, claims are cleaner, denials are reduced, and agencies stay in compliance. These are issues cited by 70% of homecare agencies. 

With improved cashflow, agencies have the resources to grow, to invest in their staff, to scale operations, and to create a more stable work environment.

HHAeXchange RCM Services

Phil Feldman, National Director of RCM

The Rowan Report sat down with Phil Feldman, the National Director of RCM for HHAeXchange. Feldman, and the RCM service platform, came from Sandata and joined HHAeXchange in the acquisition in 2024. We asked Feldman about RCM services: 

The Rowan Report:

What makes HHAeXchange’s RCM different?

Phil Feldman:

The RCM service platform is specific. It is specific to home care, specific to Medicaid, and specific to HHAeXchange. Agencies are connected to resources within the organization. We have existing relationships with payors that we can resolve directly. And the customer-facing team, the experts handling your revenue cycle, are employees of HHAeXchange, not a partner or a 3rd party.

RR:

What is the agency experience with HHAeXchange’s RCM service?

Feldman:

We are currently only offering the RCM services within the HHAeXchange platform. You have one vendor and one platform. When there’s a finger to point, it points right back at us. 

Every account has at least one RCM advisor who serves as the primary point of contact, working with the agency on their billing schedule, their time-keeping week, and the whole process from close to claim.

The intelligence in the platform goes beyond mechanically processing claims and takes a holistic approach. The system checks for demographic descrepancies from intake like member IDs, gender alignment, ID updates from new payors, overservicing on claims, providing services past the end date or outside allotted days. We look directly at the agency’s denial trends and go upstream in the revenue cycle to fix the whole process, not just one claim.

Results

With just under five months since the full launch, and nearly a year of data from beta test agencies, Feldman says their agency claims are in the 90% collection rate. Claim denials, clawbacks, and remit time are trending down. A full data set is forthcoming, but for now, Feldman is relying on anectodal evidence: Their customers are referring agencies that are looking for RCM solutions.

“You’re the best thing ever. I have a lot of friends that I consult with and help them run their business. I want to introduce them to you.”

– An Indiana Agency Owner

Final Thoughts

Hiring and retention issues, reimbursement rates, administrative workload, operational costs, denials, payor compliance, authorizations…these issues are universal across home care and aren’t going away any time soon. If you’re looking for ways to optimize your current workforce, reduce overhead costs and tasks, and create a steady cash flow for your agency, outsourcing RCM is one way to do it. If you’re already an HHAeXchange customer, well, it just makes good sense to work within the system you know, with advisors who take time to understand your agency, and the backing of decades of experience.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

The Broadway Secret

Admin

by Aaron Marcum

The Home Care Back Stage

The Broadway secret every home care owner needs to know

A few years ago, I took my daughter to see “Wicked” in London’s West End.

From the moment the lights dimmed, we were transported. The performances were flawless, the choreography mesmerizing, and the vocals spine-tingling. For two and a half hours, we sat captivated by what appeared to be theatrical magic.

It looks like magic

But here’s what struck me as I watched: what we were experiencing wasn’t magic at all. It was the result of an incredibly sophisticated operation happening behind that curtain—an operation most audience members never think about.

Dan Sullivan, founder of Strategic Coach, calls this the “Front Stage” and “Back Stage” of your business. And it’s a framework that every home care owner needs to understand.

The Home Care Back Stage

What Makes Broadway, Broadway?

When you pay for a West End ticket, you’re not just paying for talented actors. You’re paying for a lighting crew coordinating hundreds of cues per show, costume designers managing dozens of quick changes, sound engineers balancing multiple wireless microphones in real-time, stage managers calling hundreds of technical cues with split-second precision, and a production team that rehearsed for months before opening night.

The Front Stage—what the audience sees—only shines because of an exceptional Back Stage.

Your home care business has the same dynamic

Front and Center

In our industry, the Front Stage is your care professional arriving at Mrs. Johnson’s home at 9 AM. It’s the smile, the gentle assistance with morning medication, the conversation during breakfast, and the compassionate help with bathing and dressing.

That’s what your clients see. That’s what their families remember. That’s how your business gets judged.

But we all know that caregiver showing up prepared, on time, and trained isn’t an accident.

Behind the Scenes

Your Back Stage makes it possible: 

  • Care Coordination ensures the right caregiver with the right skills is scheduled for the right client. When this system fails, clients feel it immediately.
  • Billing Systems that work seamlessly mean caregivers get paid accurately and on time—because nothing destroys Back Stage morale faster than payroll errors.
  • Compliance Infrastructure keeps you operating legally and safely, protecting both your clients and your business.
  • Recruitment and Hiring processes that attract quality candidates. With projections showing a national shortage of 151,000 caregivers by 2030 and 355,000 by 2040, your Back Stage recruiting determines whether you have anyone to put on the Front Stage. As a side note, I personally believe the shortages are greater than this.
  • Training Programs that don’t just check boxes but actually prepare caregivers for real situations. The 2025 Activated Insights Benchmarking Report found that agencies offering 8+ hours of orientation training had median revenue of $2.4 million compared to $2.03 million for those with 3 or fewer hours.
  • Retention Strategies because the average caregiver costs $2,600 to replace Activated Insights. Your Back Stage culture determines whether caregivers stay or leave.
Home Care Broadway Back stage
Home Care Broadway back stage

The Numbers Tell a Sobering Story

Here’s the reality: the home care industry’s turnover rate reached 79.2% in 2023 Home Health Care News—the highest it’s been in five years. Think about that. In an agency with 100 caregivers, you’re replacing nearly 80 of them every single year.

But it gets worse. Nearly four out of five caregivers leave their job within the first 100 days of employment. That means the caregivers you just spent weeks recruiting, screening, and training? Most of them won’t even make it through their first three months.

When your Back Stage is weak, these statistics become your reality.

The "Community Theater" Problem

We’ve all attended shows where you could tell the Back Stage was struggling.
Maybe you’ve seen a local production where an actor missed their entrance, the lighting was off, a scene change took too long, or the sound cut out.

You couldn’t see the Back Stage problems, but you absolutely felt them.
The same thing happens in home care.

A weak back stage

When your Back Stage is weak:

  • Caregivers show up late (or not at all) because scheduling is chaotic
  • Families receive incorrect bills because systems are disconnected
  • Care quality suffers because training is inconsistent
  • Your reputation erodes one Front Stage failure at a time

Your clients might not know your payroll system crashed or that your care coordinator called in sick for the 4th time this month, but they experience the consequences.

The Broadway Standard Question

So here’s the question every home care owner must ask:

Is your business operating at Broadway standards, or community theater? Be honest.

When you look at your Back Stage operations:

  • Can your care coordinators instantly access complete client information?
  • Do your caregivers have clear protocols for every situation they might encounter?
  • Is your billing accurate enough that families rarely question an invoice?
  • Do you have documented processes, or is everything “in someone’s head”?
  • Could your business run smoothly if your top coordinator was suddenly unavailable?

The best home care agencies—the ones with waiting lists and stellar reputations—aren’t just lucky. They’ve built Broadway-quality Back Stage operations.

They’ve invested in systems, training, and processes. They’ve documented their playbook. They’ve made the Back Stage so strong that the Front Stage can shine consistently, every single day.

Because here’s what I learned watching “Wicked”: excellence isn’t about one amazing moment. It’s about a thousand excellent decisions that happen when no one is watching. 

The question is: what's happening in your Back Stage?

Want to build your Broadway-worthy Back Stage?

Stay in the know with strategies, insights, and practical resources designed specifically for home care owners. Subscribe to receive updates, newsletters like this, and tools that will help you elevate both your Front Stage performance and Back Stage excellence. Because your caregivers—and your clients—deserve a five-star experience every single time.

# # #

Aaron Marcum Home care and Broadway

Aaron Marcum is an entrepreneur and thought leader who has dedicated his career to transforming the home care industry and nurturing business leaders.

As the founder of Home Care Pulse (now Activated Insights), he pioneered the Best of Home Care® program, revolutionizing quality standards in senior care across North America. His expertise as a Certified Blue Ocean Strategy practitioner and former Certified EOS Implementer has helped shape some of home care’s most respected brands.

© 2026 This article originally appeared in Aaron Marcum’s newsletter and is reprinted here with permission. For more information or for permission to use this material, please contact Aaron Marcum.

Update: CMS Response to Arizona Hospice

Admin

by Tim Rowan, Editor Emeritus

Update: CMS Sides with NGS in Arizona Hospice Case

Letter Says "Typos Count"

We are sad to have to report that CMS has rejected the evidence that a hospice’s report of change of ownership was due to a typo. The consultant retained to help with their appeal received this letter.

The CMS Letter

Thank you for your email. Based on our review, we do not see any issues with the revocation decision. The provider did file a reconsideration, and on May 6, 2026, we issued a decision upholding the 42 C.F.R. § 424.535(a)(8)(ii) revocation. Their main argument is that there was no change in ownership and, as a result, they should not have been subject to PPEO. However, the applications submitted by the provider clearly reflected 100% changes in ownership. In addition, the provider had an 80% PPEO claim denial rate, and none of these denials were overturned on claim appeal. Please note that the provider filed an appeal with the ALJ on June 18th. Given that the case is pending, we should not take any other action until the appeal has concluded.

Best Regards,

Anaga Nmagu, JD.
Director, Division of Provider Enrollment Appeals
Provider Enrollment & Oversight Group
Center for Program Integrity
Centers for Medicare & Medicaid Services
Office: (410) 786-4690
Email: anaga.nmagu1@cms.hhs.gov

Hospice Arizona NGS

Home Health and Hospice Respond

The more stories we can collect about CMS contractors overstepping their authority, improperly denying claims, up to and including putting honest providers out of business, the more convincing we will be when we confront the perpetrators. We urge you to tell us your stories. We will never publish your name.

If you, a client, or someone you know has stories about CMS contractors, please reach out to editor@therowanreport.com or tim@rowanresources.com. 

# # #

Tim Rowan The Rowan Report

Tim Rowan is a 33-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Hiring and Retaining Professional Caregivers

Admin

by Roger McManus, MBA

Hiring and Retaining Professional Caregivers

What Really Keeps People in This Work

People who work in home‑based care, whether licensed home health clinicians or trained home care aides, do something unusual in the healthcare world. They walk into a stranger’s home and step into the middle of that person’s daily life. Their role is to try to help them stay, or get, healthy, stable, safe, and dignified. All this happens in someone else’s environment. That fact impacts the hiring and retention challenge for agencies.

While somewhat overlapping, home health and home care are different fields. Home health visits are shorter, clinically focused, and built around medical goals. Home care shifts are longer, non‑medical by law, and often revolve around companionship, safety, and daily living support. But the shared denominator, the home environment, creates a common reality. Agencies must find and keep people who can handle the emotional, practical, and interpersonal demands of working inside a client’s private world.

Long-term retention depends significantly on the caregiver’s ability to adapt with a chameleon-like mindset. 

The Home Environment Changes Everything

A hospital or clinic has structure; a home does not. Workers deal with cluttered living rooms, anxious adult children, and unpredictable pets. They see clients who may be having a good day, a bad day, or something in between. They have to be able to read the situation, adjust their tone, and figure out how to help without dominating.

This is not a skill you can measure with a résumé alone. Agencies that hire well look beyond credentials. They look for temperament — calmness, respect, patience, and the ability to stay professional even when the environment may be anything but.

Retention starts with hiring people who can work in this setting.

Brown v D.C.
Hiring and Retaining caregivers

Why Turnover Hits Home Based Care Harder

Turnover in this field isn’t just inconvenient. It’s disruptive in ways that office‑based healthcare rarely experiences.

When a home health clinician leaves, cases get reshuffled, documentation gets delayed, and continuity of care suffers. When a home care aide leaves, long‑standing client relationships can collapse overnight. The Patient is most aware.  Families notice. Referral partners notice. 

Workers leave for predictable reasons:

  • Home health clinicians may feel isolated or overwhelmed by documentation and case complexity.
  • Home care aides may feel undervalued or stuck in roles with no visible progression.
  • Both groups may struggle with inconsistent schedules, long drive times, or emotionally draining cases.

Retention improves when agencies acknowledge these realities instead of treating turnover as “just part of the industry.”

Creating a Support System That Actually Works

The best retention strategies aren’t flashy. They’re consistent, practical, and rooted in what workers experience every day.

Home health clinicians need clinical leadership that is reachable. Not a voicemail box. Not a once‑a‑week check‑in. They need someone who answers the phone when a wound looks worse, when a medication list doesn’t match the chart, or when a family is spiraling. Caregivers knowing they have that backup reduces burnout more than any bonus ever will.

Home care aides need respect and inclusion. They may not have medical licenses, but they are the ones who see the client’s real daily life. Agencies that treat aides as essential contributors, not interchangeable labor, see stronger loyalty and longer tenure.

Across both groups, communication is the glue. Workers stay when they feel connected to a team that listens and responds. 

Logical Rewards

Incentives That Make Sense in the Field

Many agencies try bonuses, gift cards, or occasional “thank you” events. Those gestures are fine, but they rarely change long‑term behavior. Logical rewards do.

These incentives tie directly to the realities of home‑based work:

  • Readiness bonuses for workers who reliably take short‑notice visits.
  • Incentives for on‑time arrival, complete documentation, or strong client feedback.
  • Skill‑tier pay ladders that reward additional certifications or specialized training.
  • Continuity bonuses for maintaining long‑term client relationships without disruption.

These rewards reinforce the behaviors that stabilize the agency. They’re not random. They’re strategic.

Onboarding and Training:

The First Impression That Never Goes Away

Retention begins the moment a new worker walks through your door. A chaotic onboarding process sends a message that “this agency is disorganized.” A clear, supportive onboarding process sends the opposite message that “we know what we’re doing, and we want you to succeed.”

Home health clinicians need onboarding that covers real‑world clinical scenarios, documentation expectations, and the unpredictable nature of home visits. Home care aides need onboarding that prepares them for communication challenges, safety issues, and the emotional realities of working with seniors.

Ongoing training matters just as much. Workers stay when they see a path forward, something to grow into, not just a job to survive.

Retention Is Not HR, It is Strategy

Agencies that retain their workers don’t just solve staffing problems. They build a competitive advantage. Families trust agencies whose workers stay. Referral partners prefer agencies that don’t constantly reshuffle cases. Regulators appreciate agencies with consistent documentation and stable clinical outcomes.

Retention is not a side project. It is a core business function.

# # #

Roger McManus

Roger McManus is the author of several books on entrepreneurship, including “Entrepreneurial Insanity in the Home Care Business,” which he co-wrote with Tim Rowan. He advises Home Care owners and HR professionals on techniques for recruiting, retaining, and rewarding caregivers.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This excerpt was provided to The Rowan Report and is printed with permission. 

Private Payors Against Fraud

Admin

by Elizabeth E. Hogue, Esq.

Private Payors Against Fraud

Join Enforcement Efforts

There seems to be a persistent myth among providers of private duty/homecare services that the federal anti-kickback statute applies to Medicare-certified providers only. On the contrary, the anti-kickback statute applies to providers who receive funds from any state or federal healthcare program; including the Medicaid Program, VA, TRICARE, etc. Private duty providers: This means many of you! Lately it has become clear that private payors have joined fraud enforcement efforts.

Guilty

In a recent case, a provider in Detroit pled guilty to conspiring to commit health care fraud. The conspiracy resulted in losses totaling $1.9 million to Medicare, Medicaid, and Blue Cross Blue Shield of Michigan. The investigation was conducted by the FBI and the Office of Inspector General of the U.S. Department of Health and Human Services, the primary enforcer of fraud and abuse prohibitions.

Ghost Services

At the plea hearing, the provider admitted to creating and operating a scheme to submit false and fraudulent claims that were medically unnecessary or not actually provided. In some instances, services billed were not ordered by physicians. The scheme continued for over five years. The provider used the proceeds of fraud for his personal use and to benefit others.

Consequences

After a presentence report is prepared, the provider faces a possible maximum sentence of ten years in prison, a fine of up to $250,000 and up to three years of supervised release following any term of imprisonment.

Private Payers Against Fraud

Federal and Private Prosecution

It is important to note that the provider was criminally prosecuted not only for fraud with regard to claims submitted to Medicare and Medicaid Programs, but also fraud committed against a private payor, Blue Cross Blue Shield.

Your Payor Could Report You

It now appears that providers who receive payments from third party payors must be concerned about fraud enforcement. Consequently, providers of private duty/home care services must develop, implement, and update Compliance Programs.

Compliance Programs

Compliance Programs are specific types of documents that routinely address issues that providers do not usually cover in internal policies and procedures. In addition, providers may not gain benefits related to fraud enforcement if there is no formal document called a Compliance Program.

More than Accreditation

Some providers think that accreditation means they are in compliance. On the contrary, providers may be accredited but fail to meet applicable compliance standards for fraud and abuse. Compliance Programs appropriately address potential fraud and abuse issues. They also include mechanisms for helping to ensure compliance, such as processes for identification and correction of potential problems that are not addressed during the certification process.

It Could Save You

Providers also need to know that developing, implementing, and updating Compliance Programs may make a considerable difference during fraud enforcement actions. If providers have Compliance Programs in place that are current and fully implemented, enforcers may be less aggressive in pursuing potential violations.

Corporate Integrity Agreement

When enforcers discover problems with fraud and abuse in organizations, providers are usually asked to develop and implement a Corporate Integrity Agreement (CIA). This type of agreement is likely to include processes for stringent monitoring on a continuous basis. These monitoring activities can be extremely burdensome to providers in terms of both time and money. Providers with valid Compliance Programs are not necessarily asked to develop and implement CIA’s.

Final Thoughts

Now is the time for all providers, including private duty/home care companies, to recognize and act upon the need to establish and maintain Compliance Programs. “Working on it” is no longer good enough.

# # #

Elizabeth E. Hogue, Esq The Rowan Report

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2026 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. 

Are Nurses Independent Contractors?

Admin

by Kristin Rowan, Editor

Are Nurses Independent Contractors?

Jury will decide intent

After investigation, the U.S. Department of Labor (DOL) sued Amazing Care Home Healthcare Services over misclassification of workers, recordkeeping violations, damages, and unpaid overtime. The court decided the workers were misclassified. 

Classification as Employee

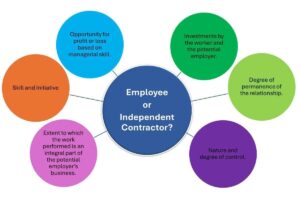
According to the decision, the workers were employees because the company had control over the work, set wages, required workers to report absences, and evaluated their performance. The DOL provides guidance on what constitutes an employee. Prior regulations use a “totality-of-the-circumstances” approach to classification, looking at the whole picture rather than a single determining factor. Other documents rely on an “economic reality” test that examines two core factors: the nature and degree of control a worker has over the work and the worker’s opportunity for profit or loss.

Summary Judgment

The DOL called for summary judgement, in which the judge would decide the case without a trial or jury due to “overwhelming” evidence. The judge partially agreed and granted summary judgement in favor of the DOL on worker classification, recordkeeping, and damages. The court declined summary judgement on the issue of overtime and intent. There is some question as to whether the workers were paid some overtime wages during the period in question and whether the misclassification was willful. These questions will be decided by a jury at trial. 

Economic Reality

The totality framework to determine worker classification came into use during the Biden administration. The DOL has recently proposed a return to the economic reality framework from 2020. Two core and three additional factors comprise the economic reality test. These two core factors are the primary determinants:

  • The nature of and degree of a worker’s control over their work
    • does the employer control scheduling, pay rates, and prices;
    • does the employer supervise performance and discipline workers
  • Opportunity for profit or loss
    • does the worker advertise services independently, negotiate contracts, decide when and where to work, have the ability to hire helpers to perform the work

These three additional factors are considered in classification analysis, but carry less weight than the two primary considerations:

  • The amount of skill required for the work
    • does the worker use their own specialized skills rather than relying on the company for training
  • –and–

    • does the worker use that skill to grow the business
  • The degree of permanence of the working relationship between company and worker
    • is the work sporadic, as needed, or project-based
  • –and–

    • is the company engaging in seasonal or temporary work or industry
  • Whether the work is part of an integrated unit of production
    • can the business operate without the work performed

Clear Answer

Using the economic reality test, can we classify home health nurses as independent contractors or employees without question?

Employee

Agency sets pay rate for the nurse
Supervised performance
Clients belong to the agency
Nurses do not hire and pay helpers
Nurses do not automatically make more when the agency grows
The business cannot operate without nurses

Independent Contractor

An agency could allow the worker to set their own schedule
Nurses use their own skills, degrees, and certifications
Work could be created as project-based where 1 client=1 project for 30 days

Final Thoughts

Without very careful planning and disruption of practice, it is pretty clear that home health workers are not independent contractors, but are employees. There may be significant differences in the operation of non-medical supportive care at home, but pay rates are still determined by the agency, performance is supervised, clients belong to the agency, and the business cannot operate without healthcare workers. The DOL sued for unpaid overtime amounting to $5.9 million on behalf of both LPNs and Home Health Aides. 

Are nurses independent contractors

If you do now or plan to in the future engage any worker as an independent contractor, review all current FLSA and DOL requirements to ensure you are not misclassifying your workers.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

VA Updates Community Cares Contracts

Admin

by Kristin Rowan, Editor

VA Issues RFP

Updates to Community Care Contracts

Some Veterans receive care from VA providers. Non-VA providers can still provide care for Veterans through a Community Care contract with the U.S. Department of Veterans Affairs (VA). In late 2025, the VA released a Request for Proposal (RFP) for new CC contracts. The new contracts are designed to substantively change non-VA provider care to Veterans.

According to the VA, the new contracts are intended to:

  • Increase choice through an IDIQ model that allows multiple health plans to compete to serve Veterans
  • Raise quality of care by requiring plans to follow broad standards of care adopted by major health systems
  • Improve oversight and quality of care using better data, technology, and real-time management
  • Add flexibility so the VA can issue competitive task orders and remove underperforming contractors

How Does This Impact Care at Home?

The primary contractor, and therefore the ones responsible for bidding and ensuring quality of care are the health plans. So, how does this change impact home care and home health providers? Here’s how:

  • Fast changes in network participation along with sudden shifts will inevitably come as a result of plans competing and task orders changing
  • Plans will need to align with VA targets, so expect waves of onboarding, recurring pushes for credentialing, and increased local networking
  • Because the plans will be held to quality standards, you can expect that those standards will flow through provider documentation, timeliness, claims accuracy, and EVV and FWA compliance
  • IDIQ is specifically designed to allow changes in the middle of care, which means the VA and health plans can add or change rules or portal, and make revisions to edit sets during the contract

Get Ahead of the Changes

Plan to make some changes before these new Community Care contracts come to your local health plans. In order to comply with the contract requirements, your credentialing packets need to be updated to include up-to-date CAQH, insurance, licenses, and compliance. This will help minimize the lag-time before getting paid.

Anticipate Expectations

The health plans will be competing for contracts, so they will expect you to compete as well. Awarded contracts will likely be fulfilled by agencies who have a high clean claim rate and quick response to edits and denials. Whatever you are using for coding, documentation, and rules need to be validated before the new care contracts start. Complete documentation will comply with the VAs focus on better data and real-time management. Make sure your team is executing precise reports; centralize your records, documentation, and audits to prove performance records and decrease issue resolution time.

Get Ahead of the changes

Final Thoughts

Non-VA providers who want to be considered to provide care to Veterans need to show alignment with the VA’s goals to expand choice, raise quality, and increase oversight. Planning ahead by meeting those standards early will make the transition process smoother one the new contracts roll out. We will continue to provide resources and information on these Community Care contracts as they are available.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Overtime Law Changes: An Interview with Angelo Spinola

Admin

by Kristin Rowan, Editor

Overtime Law Changes

An Interview with Angelo Spinola

Recent Department of Labor (DOL) changes to the overtime law appear to be at odds with a court ruling. Last week, The Rowan Report reported on Pennsylvania’s 3rd circuit court decision allowing the DOL to interpret meaning and create the rule that 3rd party employers cannot use the exemption to overtime rule. They must pay overtime according to the Fair Labor Standards Act (FLSA). The decision is in direct opposition to the DOLs intent to revert back to allowing the exemption and to its statement that it will no longer uphold the rule. The Rowan Report reached out to care at home attorney Angelo Spinola to get his take on the Pennsylvania court’s decision and how it impacts care at home.

Prior Statements

Angelo was a presenter at last year’s National Alliance for Care at Home (The Alliance) annual meeting, during which he discussed the DOL proposal to change the FLSA. In his remarks, Spinola emphasized that the exemption change is huge for home care. He also provided some specific examples showing how the change will benefit caregivers.

From the DOL

Overtime law changes, according to the DOL, will:

  • Reduce labor costs
  • Provide greater scheduling flexibility
  • Expand access to home care services
  • Reduce overhead for agencies

In Practice

Angelo added additional context from a real-world perspective.

First, you can still pay overtime. Payroll policies of any agency with an overtime program in place will supercede the DOL rule. However, those policies need to be written and part of your contractual agreement with the caregiver.

Secondly, some states have their own overtime laws, which also override the FLSA. Not every state will be impacted by the change.

Additionally, removing the overtime requirement brings back day rates instead of hourly pay, which can be beneficial for caregivers and patients. This reinstatement also impacts bonus payments. Currently, gift cards, bonuses, on-call premiums, and similar incentives are incorporated into rates for overtime. Without the exemption, agencies can bring back bonuses designed to encourage longevity, productivity, or other behaviors, and those incentives will not be subject to overtime rules.

The practical reality is, with overtime rules in place, many agencies will not allow caregivers to work more than 40 hours. Thus, patients end up with more unique caregivers, which leads to less continuity of care. The other consequence is that caregivers seek to make up those hours at other agencies or by taking on another part time job. Without the exemption, caregivers can work more hours, the patient gets fewer unique caregivers and benefits from improved continuity of care. Scheduling is less complicated without having to consider the part-time job.

In His Own Words

With the DOL proposal still undecided and its potential conflict with the recent Pennsylvania court decision, we sat down with Angelo to get his take on the decisions and the impact both would have on home care.

The Rowan Report:

Angelo, thank you for joining us today. I appreciate you taking the time to talk about the overtime rules. With the DOL no longer enforcing the rule as it stands and the Pennsylvania court case upholding it, we want to make sure we are relaying the right information and that our readers are following the right recommendations.

Overtime Rule Changes interview Angelo Spinola

Angelo:

It definitely seems like it’s two different views on the same issue, and I think we will see that for a while, until and unless the Department of Labor actually issues new regulations and interpretations. They have alluded that they are going to do that, maybe by simply not enforcing the rule. Still, at the end of the day, it is the current rule, there is the requirement to pay overtime.

RR:

Can you speak to the PA decision, then, as it relates to that?

RR:

Can you speak to the PA decision, then, as it relates to that?

RR:

Does this case have any impact, then, on the DOL reverting back to pre-2013 when 3rd party agencies could take the exemption?

wAngelo:

If this court is taking the position that the DOL can decide, then that should not impact the DOL’s next subsequent decision to decide again that third parties can use the exemption.

Remember, this is just a Court of Appeals decision, and the court itself says that it is not precedential. What I wonder is, what happens now if the Department of Labor in the future decides that they no longer think that agencies should use these exemptions? Does this pave the way for that kind of future action? Prior to this case, the Chevron deference probably would apply, because the authority all points to the ability for third parties to be able to use the exemption.

When you look at when the exemptions were applied to the FLSA, there was no limitation of who could use them. The limitation was about what kind of work the employee performed, who they performed it for. If it was assistance with ADLs and IADLs in a personal home, then you could rely on the exemptions.

Then came the efforts to limit those exemptions over several years, via Congress and a Supreme Court challenge. In the Koch decision, in the early 2000s, the Supreme Court said, “Third-party employers can rely on the exemption, because there is nothing in the language that suggests they cannot.”

In response, the DOL took it in their own hands and changed it, before there was a limitation from the Chevron deference. Now they want to change it back. I think that is where the weight of authority is, so I think they will be able to survive any deference challenge.

I think this case actually supports that argument: “We get to decide what we want to do. Look at what Pennsylvania said.” Nevertheless, I still believe it’s going to be a challenge for the DOL to flip it back again. They will have to go through all that history of what Congress had said, and what the Supreme Court said. Still, this decision certainly helps any future administration, should they choose to flip things back to the way they sit today. All this assumes that the DOL does, in fact, change it, which I think they will.

Overtime Law Changes divides care at home industry

A House Divided

RR:

There is a portion of the home care industry that wants the exemption to stay as it is, and another that says, no, it needs to go back to the way it was. I wonder if that is in any way going to impact whether or not the Department of Labor in this administration moves forward, or maybe pauses on changing that language.

Angelo:

I think there’s a growing understanding of what the reinstatement of the exemptions would mean. There is a narrative that it must mean that caregivers will lose their right to overtime pay, and will therefore be compensated unfairly, meaning less. Agencies are coming around to understanding that isn’t going to happen, because the market will not allow it to happen. This explains why caregiver rates have increased in recent years. They will go work somewhere else if you don’t compensate them fairly. So, the nature of the compensation is likely to change. It may look more like bonuses, or incentives, or things that you would do for exempt employees.

RR:

I want to make sure I am presenting this correctly here. When this changes, will it open up some possibilities in home care? If a family is paying for 10 or 12 hours per day, paying for overtime makes a huge difference and they would likely opt for fewer hours or a second caregiver. But, with the exemption, you have fewer caregivers on one case, better continuity of care, and possibly more care hours.

Angelo:

That is exactly right. What agencies do now is they often limit the caregiver to 40 hours, and then that caregiver has to go find a job at a second agency if they want to work 70 or 80 hours. In that scenario, caregivers bounce around multiple clients, who have to utilize multiple caregivers, especially if they require a lot of hours. A lot of those clients have memory issues and a vulnerable immune system. On top of mental confusion issues, the more exposure you have to different people, the more unique bacteria and germs come into the house, the more at risk you are.

You can see how much better it is, on several levels, for a caregiver to work many hours with one client. That is usually the client’s preference anyway. 

RR:

You said you think it’s pretty certain at this point that the Department of Labor is going to change that ruling back to the 1974 version. Do you anticipate lawsuits against that change?

Angelo:

I think we’re probably going to. It’s such a big deal, I would expect to see something. I would think that the advocacy groups and the unions are already likely prepared for that. When the change in 2013 was announced, the industry rallied, and we were prepared to file. So, it would not shock me in any way, if that same response returned.

RR:

I appreciate your time and helping all of the industry understand these sometimes very confusing changes in labor laws. I anticipate that once the Department of Labor makes their final decision, we’ll be back in touch to talk again about what it means, when it will be enforced, and what any pending lawsuits will have to say about it. We’ll keep everybody abreast of what these changes are going to mean for the industry.

Angelo:

Yeah, this will be one to track for sure. We are going be tracking this for the next 12 months at least.

RR:

I think for the industry and for the agencies that we talk to, the most important thing is following the law as it stands, regardless of what it is. What do they need to follow right now? What is the date on which they need to change what they’re doing, and whether or not a rule change gets overturned in another court case. They want to be in compliance, and we want to ensure what we report helps our readers to do just that.

Today, the overtime rule is in effect and agencies are required to pay overtime. That will continue to be true until the Department of Labor actually implements this change they’re talking about, regardless of what anybody else is saying.

Angelo:

That’s right. The only thing that really has changed right now is that the Department of Labor themselves are not enforcing the 2013 rule per the field assistance bulletin that went out, but that has no impact on private litigation.

RR:

Thank you so much. I really appreciate you taking the time to talk, and I’m sure I’ll see you next week.

Angelo:

Absolutely, I’ll see you at Home Care 100.

# # #

With two decades of legal experience, Angelo Spinola’s practice focuses on employment litigation with a special interest in the home health, home care and hospice industry. Bringing a wide breadth of knowledge across the health care spectrum, he works with an array of home-based care clients, including Fortune 500 organizations and franchisors, small businesses, and franchisees across multiple industries. Additionally, Angelo works closely with private equity firms and investment groups with respect to labor and employment issues that may arise during acquisitions and activities in these sectors.

Overtime Law Changes Angelo Spinola
Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Death of ALF Resident

Admin

by Kristin Rowan, Editor

Death of ALF Resident Forces Sale

5-year care ban

The 2024 death of assisted living facility (ALF) resident forces the sale of the facility by its owners and imposes a 5-year ban on the care of vulnerable adults. The owners of Brookhaven on 131st Assist Living, Levi and Holly Walker, were accused of wrongful death by the family Robert Pollmann. The Attorney General later joined case, adding neglect and consumer fraud to the charges.

Unattended and Unnoticed

85-year-old Pollmann, who suffered from dementia, was a resident of Brookhaven. His family sought a facility for his care because his dementia had made him an increased flight risk. Brookhaven assured the family they could care for Pollmann and handle the flight risk. Despite those reassurances, in June of 2024, Pollmann wandered out the door of the facility alone and his departure went unnoticed for 40 minutes. Pollmann was found 1/4 mile from the facility two days later dead from heat exposure. Search efforts were unsuccessful due in part to the extreme heat rendering thermal imaging ineffective. 

Warning Bells

Arizona law requires ALFs to have door alarms. These alarms are the first warning and best defense against residents wandering and leaving the facility. According to prosecutors, the facility doors had alarms installed, but they were not functioning for at least six months prior to the incident and for at least a month after.

Learning Experience

In addition to the 5-year ban, the Walkers have to notify the AZ Attorney General if they ever apply to run a care home or provide care after that. The Pollmann family said in a statement that they hope their case will lead to stronger regulations and better enforcement to protect facility residents.

Death of ALF Resident forces sale

Final Thoughts

Aging in place is more comfortable for our loved ones, has a lower risk of infection and disease, lowers instances of delirium, and reduces hospitalization risk. Unfortunately, it is not always possible or advisable to keep a loved one at home when the dangers are high. When assisted living facilities become the better option, strong regulations and safeguards to ensure our most vulnerable populations are in the best hands are imperative. 

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Fraud and Abuse Compliance

Admin

by Elizabeth E. Hogue, Esq.

Fraud and Abuse Compliance

Why All Providers Should Have One

Providers may have heard or read about the importance of Fraud and Abuse Compliance Programs in their organizations. Despite the wealth of available information about Compliance Programs, many providers continue to express uncertainty about their value. 

Coincidentally, as we are preparing to publish this article, HHS publishes this report on the compliance audit of Guardian Home Care, LLC. 

Here are some of the questions providers often ask about Compliance Programs:

Why should we have a Fraud and Abuse Compliance Program?

First

The Office of Inspector General (OIG) of the U.S. Department of Health and Human Services (HHS) has clearly stated that all providers are now required to have current Compliance Programs that are fully implemented. 

Next

As a practical matter, when providers establish and maintain Compliance Programs, it clearly discourages regulators from pursuing allegations of fraud and abuse violations. Jody Hunt, formerly of the DOJ, says providers should create robust fraud and abuse compliance programs. Then providers can argue that they shouldn’t be liable for violations because their compliance programs demonstrate that they had no intent to commit fraud.

Technically speaking, the Federal Sentencing Guidelines make it clear that establishment and implementation of Compliance Programs is considered to be a mitigating factor. That is, if accusations of criminal conduct are made, the consequences may be substantially less severe as a result of a fully implemented Compliance Program.

Additionally

Providers with Compliance Programs are more likely to avoid fraud and abuse. This is because Programs routinely establish an obligation on the part of every employee to report possible instances of fraud and abuse and include training for all employees.

Compliance Programs may also help to prevent qui tam or so-called “whistleblower” lawsuits by private individuals, rather than by government enforcers, who believe that they have identified instances of fraud and abuse. There are significant incentives to bring these legal actions since “whistleblowers” receive a share of monies recovered as a result of their efforts. Some “whistleblowers” have received millions of dollars.  Compliance Programs make it clear that employees have an obligation to bring any potential fraud and abuse issues to the attention of their employers first.

Also…

The federal Affordable Care Act (ACA) requires providers to have Compliance Programs. In short, it’s the law!

Finally

The Deficit Reduction Act (DRA) requires providers who receive more than $5 million in monies from state Medicaid Programs per year to implement policies and procedures, provide education to employees and put information in their employee handbooks about fraud and abuse compliance. These requirements can be met through implementation of Fraud and Abuse Compliance Programs.

We don't receive reimbursement from the Medicare or Medicaid Programs.

Do we still need a Compliance Program?

Statutes and regulations governing fraud and abuse also apply to providers who receive payments from any federal and state healthcare programs, including Medicaid, Medicaid waiver and other federal and state health care programs, such as Tri-Care. Many private insurers have followed the federal government’s “lead” in terms of fraud and abuse enforcement.  So private duty providers must have compliance programs, too.

Should we just use the model guidance that is applicable to us?

We hear that the OIG has provided guidance for various segments of the healthcare industry regarding Compliance Programs. Specifically, the OIG has already published guidance for clinical laboratories, hospitals, home health agencies, skilled nursing facilities (SMFs), hospices, physicians’ practices, third-party billing companies and home medical equipment companies. The OIG will publish updated guidance for all providers, It has already done so for SNFs.

The answer is “No!” Guidance from the OIG is not a model Compliance Program. Guidance from the OIG consists of general guidelines and does not constitute a valid Compliance Program. In addition, the OIG has made it clear that Programs must be customized for each organization. 

Do we have to conduct internal audits first?

We have read that, before implementing Compliance Programs, providers must conduct expensive internal audits that can take many months to complete. Is this true?

While beginning the compliance process with an extensive internal audit is certainly one way to proceed, it is not the only viable way to work toward compliance. It is equally valid to begin with Compliance Programs that are customized for the organization that includes training for all employees about fraud and abuse and Compliance Programs. Then all staff members can subsequently participate in internal compliance activities, including audits, with a process in place to handle any issues that arise as a result of the audits.

We already have policies. Why do we need a Compliance Program too?

Compliance Programs are specific types of documents that routinely address issues that providers do not usually cover in internal policies and procedures. In addition, providers may not gain benefits under the Federal Sentencing Guidelines described in the first question above if there is no formal document called a Compliance Program.

We're accredited. Doesn't that mean we are in compliance?

On the contrary, Compliance Programs appropriately address potential fraud and abuse issues. They also include mechanisms for helping to ensure compliance such as processes for identification and correction of potential problems that are not addressed during the certification process. In other words, organizations may be accredited but fail to meet applicable compliance standards for fraud and abuse.

Will it help with investigations?

Will the fact that our organization has a Compliance Program make any difference with regard to the outcome of fraud and abuse investigations and the imposition of Corporate Integrity Agreements (CIA’s)? 

Yes, it may make a considerable difference based on statements from the OIG. If providers have Compliance Programs in place that are current and fully implemented, the OIG may be less aggressive in pursuing potential violations. When the OIG actually discovers problems with fraud and abuse in organizations, providers are usually asked to develop and implement a Corporate Integrity Agreement (CIA). The OIG often requires CIA’s to include a process for stringent monitoring by the OIG on a continuous basis. These monitoring activities can be extremely burdensome to providers in terms of both time and money. Providers with valid Compliance Programs are not necessarily asked to develop and implement CIA’s. 

Fraud and Abuse Compliance

Final Thoughts

Now is the time for all providers to recognize and act upon the need to establish and maintain Compliance Programs. “Working on it” is no longer good enough.

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. 

What can Providers Give to Patients, Part 7

Admin

by Elizabeth E. Hogue, Esq.

What Providers can Give to Patients

Providers, including marketers, are tempted to give patients and potential patients free items and services. While providers usually have good intentions, they must comply with applicable requirements.

OIG Advisory Opinion

This article provides an example from OIG Advisory Opinion No. 09-11 that shows how the OIG applies exceptions described in this series of articles.

A Case Example

The request for this Advisory Opinion was submitted by a hospital that provides free blood pressure checks to anyone who requests the service during certain hours. The hospital said that it does not advertise free blood pressure checks, which are provided by a member of the nursing staff who follows specific guidelines and procedural checklists.

The hospital also said that free blood pressure checks are not conditioned on use of any other goods or services from the hospital or any other particular provider. No discounts are offered for follow-up services. Recipients of blood pressure checks are advised to see their own practitioners when results are abnormal. The hospital does not bill any payor, including the Medicare and Medicaid Programs, for this service.

OIG advisory opinion

OIG Analysis

In its analysis, the OIG first referenced the exception for preventive services described in Part 5 of this series.

The OIG then pointed out that the fair market value of this service, especially if recipients use the service more than once, may exceed the limits of $15 per service or $75 per year described in Part 2 of this series. Therefore, said the OIG, the services may constitute a kickback.

According to the OIG, blood pressure checks are preventive services. The key question, however, is whether the free care promotes the provision of other, non-preventive care reimbursed by the Medicare and/or Medicaid Programs.

Is It Promotional?

In this case, the OIG said that it is unlikely that free blood pressure checks will result in the provision of other services. The factual basis for this conclusion in the Advisory Opinion was that the hospital did not:

  • Make appointments with its practitioners for individuals with abnormal results
  • Offer individuals discounts for additional covered services
  • Otherwise promote its particular programs

Crafted with Care

“In sum,” said the OIG, “the Arrangement is appropriately crafted so as to avoid improper ties to the provision of other services…For these same reasons, we conclude that we would not impose administrative sanctions arising in connection with either the anti-kickback statute or the CMP on the Hospital in connection with the Arrangement.”

Final Thoughts

The 7 parts of this series describe and summarize the laws and exceptions to providing incentives, gifts, and help to patients in accordance with the Anti-Kickback Statute and the Civil Monetary Penalties Law. As long as you are following these regulations, providers should certainly use all of the exceptions available to them to provide better quality of care for patients.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. 

What Can Providers Give to Patients, Part 5

Admin

by Elizabeth E. Hogue, Esq.

What Can Providers Give...

Recap

Providers, including marketers, are tempted to give patients and potential patients free items and services. While providers usually have good intentions, they must comply with applicable requirements. 

Part 1

As Part 1 of this series indicates, there are two applicable federal statutes: the Anti-Kickback Statute (AKS) and the Civil Monetary Penalties Law (CMPL). Part 1 also makes it clear that there are a number of exceptions. If providers meet the requirements of applicable exceptions, they can give patients and potential patients free items and services that would otherwise violate applicable requirements. 

Part 2

Part 2 describes an exception for items and services of nominal value with a retail value of no more than $15 per item or $75 in the aggregate per patient on an annual basis that may be given by providers to beneficiaries. Providers may not, however, give cash or cash equivalents.

Part 3

Part 3 describes the circumstances under which providers may give free items and services to patients with demonstrated financial need.

Part 4

Part 4 summarizes recent guidance from the Office of Inspector General (OIG) about giving incentives to promote vaccination against COVID-19.

Care & Services

According to the OIG, providers may also give patients free preventive care items or services. The definition of remuneration under the CMPL regulations excludes incentives given to patients/potential patients to promote the delivery of preventive care services so long as the delivery of such services is not directly or indirectly related to the provision of other services reimbursed in whole or in part by the Medicare Program or other state and federal healthcare programs. Preventive services include:

  • Prenatal services or postnatal well-baby visits, or specific clinical services described in the current U.S. Preventive Services Task Force’s Guide to Clinical Preventive Services
  • Services that are reimbursable in whole or in part by the Medicare Program, or other federal and state care programs

Incentives

However, incentives related to preventive services may not include:

  • Cash or instruments convertible to cash
  • Incentives of value that are disproportionally large in relationship to the value of the preventive care services in terms of either the value of the services or the future health care costs reasonably expected to be avoided as a result of preventive care
What Can Providers Give to Patients

Preventive

Any tie between provision of exempt covered preventive care services and covered services that are not preventive may, therefore, violate the CMPL and the AKS.

The OIG has stated that some free or discounted services may fit within the preventive care exception described above. These services may include free blood sugar screenings and cholesterol tests.

Anti-Kickback Exceptions

The AKS does not include an exception similar to the provisions of the CMPL described above. In commentary to Supplemental Compliance Guidance for Hospitals, however, the OIG said:

From an anti-kickback perspective, the chief concern is whether an arrangement to induce patients to obtain preventive care services is intended to induce other business payable by a Federal health program. Relevant factors in making this evaluation would include, but not be limited to: the nature and scope of the preventive care services; whether the preventive care services are tied direct or indirectly to the provision of other items or services and, if so, the nature and scope of the other services; the basis on which patients are selected to receive the free or discounted services; and whether the patient is able to afford the services.

Final Thoughts

Based upon the above, the OIG is unlikely to challenge the provision of free preventive services given to patients and potential patients, under either the CMPL or the AKS, so long as the above requirements are met.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. 

What Can Providers Give to Patients, Pt 2

Admin

by Elizabeth E. Hogue, Esq.

Provider Kickbacks

Exceptions

Providers, including marketers, are tempted to give patients and potential patients free items and services. While providers usually have good intentions, they must comply with applicable requirements. As Part 1 of this series indicates, there are two applicable federal statutes: the anti-kickback statute and the civil monetary penalties law. Part 1 also makes it clear that there are a number of exceptions or “safe harbors. If providers can meet the requirements of an applicable safe harbor or exception, they can give patients and potential patients free items and services that would otherwise violate applicable requirements. 

Limit Increase

The Office of Inspector General (OIG) of the U.S. Department of Health and Human Services, the primary enforcer of fraud and abuse prohibitions, announced that; effective on December 7, 2016; the limits on free items and services given to beneficiaries increased. Specifically, according to the OIG, items and services of nominal value may be given to patients or potential patients that have a retail value of no more than $15 per item or $75 in the aggregate per patient on an annual basis. The previous limits were $10 per item or $50 in the aggregate per patient on an annual basis.

Undue Influence

Under section 1128A(a)(5) of the Social Security Act, persons who offer or transfer to Medicare and/or Medicaid beneficiaries any remuneration that they know or should know is likely to influence beneficiaries’ selection of particular providers or suppliers of items or services payable by the Medicare or Medicaid Programs may be liable for thousands of dollars in civil money penalties for each wrongful act. “Remuneration” includes waivers of copayments and deductibles, and transfers of items or services for free or for other than fair market value.

In the Conference Committee report that accompanied the enactment of these requirements, Congress expressed a clear intent to permit inexpensive gifts of nominal value given by providers to beneficiaries. In 2000, the OIG initially interpreted “inexpensive” or “nominal value” to mean a retail value of no more than $10 per item or $50 in the aggregate per patient an annual basis.

Kickbacks for Referrals

Needed Items, not Cash

Provider Kickbacks

The OIG also expressed a willingness to periodically review these limits and adjust them based on inflation. Consequently, effective on December 7, 2016, the OIG increased the limits of items and services of nominal value that may be given by providers and suppliers to beneficiaries to a retail value of no more than $15 per item or $75 in the aggregate per patient on an annual basis.

 Providers may not, however, give cash or cash equivalents.

 These amounts may still seem paltry to many providers. According to the OIG, providers who see that patients need items worth more than these limits should establish relationships with charitable organizations that can provide items and/or services that are not subject to these limits. In other words, work together to meet the needs of patients!

Final Thoughts

With time and the emotional context inherent in home health and hospice, clinicians may want to offer gifts to their clients. Low reimbursement rates and workforce shortage may cause HHAs to consider gifts and incentives as a way to keep clients and get referrals to new ones. If you find yourself in this situation, make sure you’re staying under the legal threshold, and engage 3rd parties to fill larger needs.

This is part 2 of a 4-part series. Come back next week for the third installment.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved.