by Tim Rowan | May 22, 2024 | Admin, CMS, Regulatory
by Tim Rowan, Editor Emeritus
For the last time, NAHC President Bill Dombi is spending another Spring on airplanes. It is state association meeting season, and the Bill Dombi Spring Tour has been bringing his regular Capitol Hill update from coast to coast, this time adding the announcement that he will retire at the end of the year.
After 40 years with NAHC, the lengthy standing ovation Californians gave him at the end of his Tuesday speech was well-deserved.
Advocacy and Change
Bill’s core message has not changed, though the details of his ongoing battle to force CMS to take HHAs and Hospices more seriously has its 2024-2025 nuances. “Letting Congress know that you are an important healthcare sector, and clearly the most popular sector, is not NAHC’s job alone. Every one of you has power. Use it. Make your voices heard.”
Meetings with the Senate Finance Committee
To illustrate the point, he related a story about his recent visit to Portland to meet with the Chair of the Senate Finance Committee, Ron Wyland (D-OR).
“Senator Wyden has been one of the major roadblocks to Medicare agencies getting fair payment rates. I went to see him with a group of agency owners and workers to describe the hardships the current and planned pay rate cuts will impose, and to explain the exact problems with the dumb formula CMS is using to calculate those pay rates.
“The Senator said, ‘But MedPAC says you make too much money and rates should be cut. Were they wrong? Or has something changed?’
Reaching Agreement…Almost
“Both, the group and I harmonized. One by one, each agency representative told him about the growing demand of an aging population, the difficulty hiring staff with the salaries our low pay rates allow them to pay, and a full litany of all the problems with Medicare Advantage.
“By the end of our meeting, we hadn’t turned him 180 degrees, but I could see he was beginning to turn.”Later, Dombi added, he met with Senator Debbie Stabenow (D-MI), who is not only a member of the same Finance Committee but the fourth in line in the Senate pecking order. She offered to have a conversation with her colleague, and that turned Senator Wyden the rest of the way toward changing his position 180 degrees.
You Can Make a Difference
“If you think you as an individual owner have no power in Sacramento, Congress, or the White House,” Dombi concluded, “think again.”
See sidebar for the complete list of Finance Committee members. Everyone has power, but if you are a voter in one of their states, you have an even more powerful voice.
The Bill Dombi Spring Tour will continue throughout the year until his retirement. Join Dombi at the 2024 Financial Management Conference & Expo in Las Vegas, July 21-23 and at the 2024 Home Care and Hospice Conference and Expo in Tampa, October 20-22.
Senator Ron Wyland (D-OR)
SENATE FINANCE COMMITTEE MEMBERS
Chair: Ron Wyland (D-OR)
Ranking Member: Mike Crapo (R-ID)
Debbie Stabenow (D-MI)
Chuck Grassley (R-IA)
Maria Cantwell (D-WA)
John Cornyn (R-TX)
Robert Menendez (D-NJ)
John Thune (R-SD)
Thomas Carper (D-DE)D-
Tim Scott (R-SC)
Benjamin Cardin (D-MD)
Bill Cassidy (R-LA)
Sherrod Brown (D-OH)
James Lankford (R-OK)
Michael Bennet (D-CO)
Steve Daines (R-MT)
Bob Casey (D-PA)
Todd Young (R-IN)
Mark Warner (D-VA)
John Barrasso (R-WY)
Sheldon Whitehouse (D-RI)
Ron Johnson (R-WI)
Maggie Hassan (D-NH)
Thom Tillis (R-NC)
Catherine Cortez Masto (D-NV)
Marsha Blackburn (R-TN)
Elizabeth Warren (D-MA)
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
by Tim Rowan | May 16, 2024 | Admin, Artificial Intelligence, Clinical, New Tech, Outcomes, Product Review, Vendor Watch
by Tim Rowan, Editor Emeritus
For better or worse, healthcare has begun the inevitable adoption of Artificial Intelligence. Before you consider adopting AI technology, know that there is a wrong way and a right way to use AI in healthcare. In a companion article this week, we describe the criticism insurance companies are getting for deploying AI in healthcare to harm patients. As a balance, here is a review of a product that we find to be using AI in healthcare to help both patients and Home Health Agencies.
The Problem
Home Health referral documents from physicians or hospitals can consist of more than 100 electronically transmitted pages. Some agencies report occasional packets exceeding 1,000 pages, often in a variety of data formats. Some are standard data formats, such as a face sheet, but most are unstructured, consisting of images or narrations, sometimes in paragraphs, sometimes in incomplete sentences. Worse, patient data interoperability can be limited by unstructured data.
More often than not, most of these pages are never read. Thoroughly interpreting that much data is nearly impossible for a human. Consequently, nurses too often approach an admission evaluation visit with an incomplete picture of a patient. The result can be gaps in care or treatment, inaccurate OASIS assessments, incomplete or poorly sequenced diagnosis codes, and improper care plans. These obstacles can impact both patient outcomes and agency revenue.
One Newly Available Solution for the Right Way to use AI in Healthcare
We recently attended a product demonstration and followed it up with updated descriptions to learn details about new product developments. Over the next three months, Select Data, in full disclosure one of our sponsors, will be introducing an AI-powered suite of products that has been designed over many years of development to support clinical, data driven decision-making. One by one, it addresses the problems described above.
The new system, SmartCare, empowers clinicians to harness previously hidden insights while reducing bias and cognitive overload. It enables them to steer their decisions with enhanced precision while maintaining their pivotal role in patient care, eliminating one of the common reasons many Home Health administrators hesitate to invite AI into agency processes. It does, however, make the care team’s job easier and facilitates better decision-making.
- AI can read those 100 to 1,000 page referral documents in minutes, where a human may require days.

- SmartCare uses AI to synthesize relevant medical history to provide a care snapshot highlighting the key diagnosis, focus and considerations for care, and recommended OASIS clinical discipline. It highlights any areas for clarification needed from physician or admitting nurse.
- Clinicians can search and index specific words in unstructured data, such as narratives, to instantly identify any detail of a patient’s condition in an easy-to-read interface. Nurses approach the initial OASIS visit armed with all of a referring clinician’s relevant care findings.
- Recommendations for diagnostic codes strictly follow Medicare PDGM guidelines.
Suite of Tools
1 – RISE stand for Rapid Intake Summary & Evaluation. This component of the suite summarizes all clinical data from referral sources and your EHR. It compiles this data to provide clinically relevant diagnoses, focus of care, and recommendations for skilled disciplines. This is the part of the tool that reads referral documents and supports informed decision-making. The advantages we detected go a bit beyond the technical.
When clinicians, reviewers, coders, and office staff all have access to the same patient information, it would seem that communication among disciplines would improve and that care coordination would be enhanced. It also seems logical that continued experiences of advanced access to previously hard-to-find physician comments would gradually break through the AI fear barrier reported by so many clinicians and other professionals. Select Data will provide us with actual client experiences to verify our assumptions once they have been compiled.
2 – ACE, or Admission Clinical Evaluation is SmartCare’s clinical support summary tool. It deploys AI to understand accepted OASIS assessment criteria. It then uses this knowledge to extract assessment and narrative data from nursing and therapy evaluations. With streamlined, pertinent data at the point of care, the entire care team has the same patient data. Having the same patient data enables more informed decision-making.
ACE links all patient data back to its source assessment. Doubt about the AI’s credibility should gradually diminish, even among the most AI-resistant users. Every analysis and recommendation is explained in clear language so that clinicians are likely to understand the rationale behind them. The goal is to replace every “I’m not going to let a machine tell me what to do” with “I’ll take this information into consideration with my human insights.”
Pricing
We are honoring Select Data’s request to allow them to build personalized price quotes to every prospective client. They will be represented at several state and national conferences this year. Alternatively, interested HHA representatives can contact EVP Ted Schulte at Ted.Schulte@SelectData.com
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
by Tim Rowan | May 16, 2024 | Admin, Artificial Intelligence, CMS, Medicare Advantage, Regulatory
by Tim Rowan, Editor Emeritus
Lawsuits are beginning to pile up against insurance companies participating in the Medicare Advantage program. The complaint? The wrong way to use AI in healthcare is with faulty algorithms to approve or deny claims. While AI can be extremely helpful in streamlining administrative tasks — comparing physician notes with Home Health assessments and nursing notes or reading hospital discharge documents — it seems not to be any good at deciding whether to approve or deny care.
The Wrong Way to Use AI in Healthcare Example 1
The Minnesota case, November, 2023, UnitedHealth Group:
-
- An elderly couple’s doctor deemed extended care medically necessary
- UnitedHealth’s MA arm denied that care
- Following their deaths, the couple’s family sued UnitedHealth, alleging:
- Straight Medicare would have approved the extended care
- United uses an AI model developed by NaviHealth called nH Predict to make coverage decisions
- UnitedHealth Group acquired NaviHealth in 2020 and assigned it to its Optum division
- nH Predict is known to be so inaccurate, 90% of its denials are overturned when appealed to the ALJ level
- UnitedHealth Group announced in October, 2023 that its division that deploys nH Predict will longer use the NaviHealth brand name but will refer to that Optum division as “Home & Community Care.”
The family’s complaint stated, “The elderly are prematurely kicked out of care facilities nationwide or forced to deplete family savings to continue receiving necessary medical care, all because [UnitedHealth’s] AI model ‘disagrees’ with their real live doctors’ determinations.”
The Wrong Way to Use AI in Healthcare Example 2
The Class-Action case, December 2023, Humana:
-
- A lawsuit was filed on December 12, 2023 in the U.S, District Court for the Western District of Kentucky
- It was filed by the same Los Angeles law firm that filed the Minnesota case the previous month, Clarkson
- The suit notes that Louisville-based Humana also uses nH Predict from NaviHealth
- The plaintiffs claim, “Humana knows that the nH Predict AI Model predictions are highly inaccurate and are not based on patients’ medical needs but continues to use this system to deny patients’ coverage.”
- The suit says Medicare Advantage patients who are hospitalized for three days usually are eligible to spend as many as 100 days getting follow-up care in a nursing home, but that Humana customers are rarely allowed to stay as long as 14 days.
- A Humana representative said Humana their own employed physicians see AI recommendations but make final coverage decisions.
What Makes This Possible
According to experts we speak with, there are many ways to use data analytics. The insurance companies named in the lawsuits use predictive decision making. This way of analyzing data compares a patient to millions of others and deduces what treatment plan might be suitable for one patient, based on what was effective for most previous patients. Opponents of this method have called it “data supported guessing.”
A superior analysis method experts are coming to understand is prescriptive decision making. This is taking all of the available historical and current data surrounding a patient and making a clinical decision specifically designed to that patient’s age, gender, co-morbidities, doctor recommendations, and treatment records.
Until recently, predictive analysis was the preferred method because of its resource efficiency. Examining the data of every individual patient used to be prohibitively labor-intensive, requiring hours of reading hospital records, physician notes, and claims. Today, however, AI tools are able to do that work in seconds, making prescriptive analytics and customized plans of care possible.
Fix May Be in the Works
In a February 6, 2024 memo to all Medicare Advantage Organizations and Medicare-Medicaid Plans, CMS explained the difference between predictive and prescriptive analytics. The memo said these plans may not make coverage determinations based on aggregated data but must look at each individual:
“For Medicare basic benefits, MA organizations must make medical necessity determinations in accordance with all medical necessity determination requirements, outlined at § 422.101(c)1 ; based on the circumstances of each specific individual, including the patient’s medical history, physician recommendations, and clinical notes; and in line with all fully established Traditional Medicare coverage criteria.”
In response to a request for clarification, the CMS memo laid out its rule in specific language: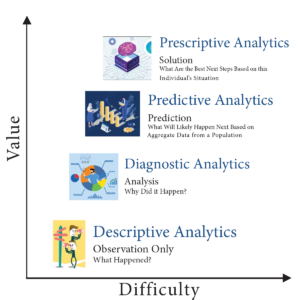
An algorithm or software tool can be used to assist MA plans in making coverage determinations, but it is the responsibility of the MA organization to ensure that the algorithm or artificial intelligence complies with all applicable rules for how coverage determinations by MA organizations are made. For example, compliance is required with all of the rules at § 422.101(c) for making a determination of medical necessity, including that the MA organization base the decision on the individual patient’s circumstances, so an algorithm that determines coverage based on a larger data set instead of the individual patient’s medical history, the physician’s recommendations, or clinical notes would not be compliant with § 422.101(c).
(emphasis added)
“Therefore, the algorithm or software tool should only be used to ensure fidelity with the posted internal coverage criteria which has been made public under § 422.101(b)(6)(ii).”
In further responses to questions in the same memo, CMS made it clear MA plans must make the same coverage decision original Medicare would make. The only allowable exception is that plans may use their own criteria when Medicare Parts A and B coverage criteria “are not fully established.”
Knowledge of this CMS directive may give Home Health agencies one more arrow in their quiver when going to battle with powerful, profit-oriented insurance companies over harmful, illogical AI algorithm decisions.
For information on the right way to use AI in healthcare, see our complimentary article in this week’s issue.
 Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
by Tim Rowan | May 2, 2024 | Admin, Privacy and Security, Regulatory, Telehealth
by Tim Rowan, Editor Emeritus
You know the routine. Everyone does. You log into your bank, airline account, or health insurance web portal, enter the correct password, and are directed to look on your smartphone  for a code to enter to fully authorize your login. The name for this is Multi-Factor Authentication, or MFA. Lack of MFA procedures leaves your company at risk, which UnitedHealth discovered when it was grilled by Congress about the cyberattack on Change Healthcare.
United Health Grilled by Congress
In his testimony to the House Energy and Commerce Committee Wednesday, UnitedHealth Group CEO Andrew Witty blamed the absence of MFA as the weak link that allowed a ransomware attack to cripple subsidiary Change Healthcare in February. The breach had ripple effects throughout healthcare, given Change’s role as fiscal intermediary for thousands of providers. Healthcare systems on every level were unable to file claims and receive payments.
Asked by the committee why Change Healthcare, which United acquired in late 2022, did not have MFA in place, Witty testified, “Change Healthcare was a relatively older company with older technologies, which we had been working to upgrade since the acquisition. But for some reason, which we continue to investigate, this particular server did not have MFA on it.”
CBS News reported that Change Healthcare processes 15 billion transactions a year. “The scale of the attack,” their report stated, “meant that even patients who weren’t customers of UnitedHealth were potentially affected. Personal information that could cover a ‘substantial portion of people in America’ may have been taken in the attack.” The breach has already cost UnitedHealth Group nearly $900 million, plus the $22 million ransom Witty decided to pay to the hackers.
The Russia-based ransomware gang, ALPHV, or “BlackCat,” claimed responsibility for the attack, bragging that it stole more than six terabytes of data, including “sensitive” medical records. The attack triggered a disruption of payment and claims processing around the country.
We followed up our initial report on the attack with CMS guidance on March 20, 2024 and an update on April 11, 2024, with reports that Change Healthcare was being blackmailed again by another ransomware gang, RansomHub, who claimed to have 4TB of data from Change Healthcare and demanded another ransom payment.
Walmart & Optum, UnitedHealth Trouble Spots?
UnitedHealth Group is also in headline news this week for two other reasons. The company’s Optum division, which owns home care giant CenterWell, formerly Kindred at Home, and which is awaiting government approval for its bid to acquire Amedisys, has quietly been executing a reduction in force. Reports are that the bulk of the layoffs are hitting “Optum Virtual Care,” the name given to naviHealth following its $1 billion acquisition in 2020. Following a surge in demand during the pandemic, the company is apparently abandoning telehealth services.
A planned 10-year collaboration between UnitedHealth and Walmart to provide virtual healthcare services ended Tuesday after only one year. On April 30, the retail giant announced that it will close its 51 health centers across five states due to the “challenging reimbursement environment” and rising operating costs, which have resulted in a lack of profitability. Like Optum Virtual Care, the centers were providing virtual services via telehealth.
A sign of the post-pandemic times? Perhaps. We will keep watching.
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
by Tim Rowan | Apr 11, 2024 | Clinical, Editorial, Telehealth
by Tim Rowan, Editor Emeritus
In 2020, doctors flooded telehealth companies with requests for help caring for patients reluctant to leave home to come to their appointments. Following suit, many Home Health agencies that had never considered investing in home telehealth before, opened up their wallets to acquire equipment, from simple wearables to high-end, HIPAA-compliant video systems.
In addition to the need to provide care at a safe distance, many HHA leaders knew the added service would attract the attention of hospitals desperate to discharge recovering Covid victims as well as non-Covid patients. Some HHAs established relationships with hospitals they had not had before, given the chance to demonstration Home Health’s unique advantages over extended hospital stays and discharges to institutions such as SNFs that had become virtual death sentences during the height of the pandemic.
All Things Must Pass
 With the introduction and widespread free availability of Covid mRNA vaccines, the death rate graph line began to tilt downward. Then came the discovery that the SARS-CoV-2 and its variants are transmitted through the air and not through unwashed surfaces. People stopped disinfecting their counter tops after unloading groceries. And they started in-person doctor visits again. Patients returned to allowing nurses into their homes.
In regions where vaccination and booster rates were high, hospitals found themselves with more and more empty beds. They took down tented treatment centers in their parking lots and sent refrigerated trailers back to trucking companies. Desperation referrals to Home Health tapered off, as did the need for virtual visits.
Isaac Newton said every action has an equal and opposite reaction. If that holds true in the healthcare business as it does in physics, the reaction to Covid easing is seen in Remote Patient Monitoring tech companies. According to Fierce Healthcare, the New York Stock Exchange told one RPM company, Amwell, formerly known as “American Well,” to raise its stock price or be delisted. Fierce added detail about the company’s woes:
“Despite decimating its workforce at the end of 2023 to cut expenses, the company still projects a 2024 loss between $160 million and $155 million amid incremental revenue growth. The company’s market cap was a stone’s throw from $6 billion at the height of its valuation, when shares were trading for more than $42 each. Amwell shares were trading at $0.72 as of market close on April 5, giving the company a current market cap of about $208.6 million.
Another market leader fared no better, Fierce Healthcare found. “Telehealth giant Teledoc, which has been in operation for 20 years, has struggled in the stock market and is facing headwinds as the virtual care market has become crowded with digital health players. Shares dropped 22 percent in February as the company missed fourth-quarter revenue estimates and offered a downbeat forecast for the rest of the year.”
Teledoc’s 15-year CEO, Jason Gorevic, resigned last week after the company reported a net loss of $220 million for 2023, following 2022’s historic loss of $13.7 billion, mostly from a write-off related to the plummeting value of its ill-advised Livongo acquisition. According to Fierce Healthcare, Teladoc shelled out $18.5 billion for the digital chronic condition management company, a record in digital health.
Gorevic’s rationale that the telehealth field has become too crowded may not be far off. Last July, Becker’s Hospital Review published an industry survey titled “280+ Telehealth Companies to Know.” The list included a half dozen names we recognized from past Home Health conferences, including Health Recovery Solutions, AMC, Vivify, and FoneMed.
Do Hospital Woes Translate Down to Home Health?
 Making comparisons between telemedicine companies that focus on hospitals and physicians and those who focus on post-acute providers is hampered by the fact that few in our sector are publicly traded and do not share their numbers. UnitedHealth, which acquired Vivify in 2019 and assigned it to its Optum division, does not separately report Vivify revenue.
Health Recovery Solutions, one of the best-known names in post-acute RPM, is privately held by its founding CEO and seven investors. Its most recent influx of $800,000 occurred in January, 2022, making it impossible to determine whether it was motivated by investor confidence or the need for cash as Covid began its decline.
Analysis
This publication has promoted the advantages of remote patient monitoring for its entire 25-year existence. We have covered startups and established tech companies offering every technology from PERS to Zo monitors to automated phone calls, in-home cameras and microphones. We have followed the evolution of two-way communications and vital sign detectors from tabletop devices to tablets and smartphones. We have even tested a few robots. We have seen HHAs experience great success, and we have seen devices collecting dust on shelves.
Throughout, we have maintained that, when selected, implemented, and deployed properly, monitoring patients 24/7 instead of once or twice a week can improve patient outcomes, boost agency reputation, and, more often than not, produce a healthy ROI. The end of the latest pandemic may mean the end of demand for Remote Patient Monitoring systems, but that would be unfortunate.
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com or Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com
by Tim Rowan | Apr 4, 2024 | Clinical, Editorial
by Tim Rowan, Editor Emeritus
For as long as I can remember, Home Health and Home Care owners and advocates, including their national and state associations, have struggled to develop concrete data to prove what we all know to be true: In-home care is a great deal for payers, both public and private. Underpaying our sector in a misguided attempt to reduce costs results in paying more in the long run. Buying more in-home care translates into lower overall cost.
This is one part of the story, and we continually search for the proof our sector so desperately needs. But there is another aspect to the Home Health, Home Care advantage that must not be overlooked as we focus on payer finances.
Patient care and safety
One need look no further than our post-acute care neighbor, Skilled Nursing Facilities, to understand how much better off elderly citizens are when in-home caregivers and clinicians enabled them to stay in their own homes and avoid institutionalized care. A new, peer-reviewed study titles “Profits Over Patients” was published in the online collective The Conversation. If unfamiliar, think of it as The Huffington Post for scholars and researchers.
In the exposé, investigators Sean Campbell and Charlene Harrington reveal that for-profit organizations have been infiltrated by Wall Street investors and other venture capitalists, seeking quick turnarounds and handsome profits. Founders and other SNF owners gladly accept generous offers to be acquired or partner with investors who immediately begin to impose cost-cutting measures and maximize profits. The probe, which paired an academic expert with an investigative reporter, discovered a number of startling findings:
“The investigation revealed an industry that places a premium on cost cutting and big profits, with low staffing and poor quality, often to the detriment of patient well-being. Operating under weak and poorly enforced regulations with financially insignificant penalties, the for-profit sector fosters an environment where corners are frequently cut, compromising the quality of care and endangering patient health.”
Campbell and Harrington also looked at the ineffectiveness of state inspectors, who have limited ability to impose meaningful fines for violations. One startling example in the report is that of a Louisville SNF. The care was found to be “abysmal” when Kentucky inspectors filed their survey report.
“Residents wandered the halls in a facility that can house up to 250 people, yelling at each other and stealing blankets. One resident beat a roommate with a stick, causing bruising and skin tears. Another was found in bed with a broken finger and a bloody forehead gash. That person was allowed to roam and enter the beds of other residents. In another ase, there was sexual touching in the dayroom between residents, according to the [surveyor’s] report.
“Meals were served from filthy meal carts on plastic foam trays, and residents struggled to cut their food with dull plastic cutlery. Broken tiles lined showers, and a mysterious black gunk marred the floors.
“Overall, there was a critical lack of training, lack of staff, and lack of supervision.”
The report said state inspectors found 29 deficiencies, including six that put residents in immediate jeopardy of serious harm and three where actual harm was found. The fine imposed was $319,000 — more than 29 times the average for a nursing home. Payments from Medicare and Medicaid were suspended. The investors and owners chalked the fine up to a normal cost of doing business and, five months later, inspectors found six additional deficiencies “of immediate jeopardy,” the highest level.
The parent company of the Kentucky SNF, Infinity Healthcare Management, owns 58 facilities across five states. Since 2021, Infinity has been hit with nearly $10 million in fines, more than 4.5 times the national average.
Cut staff, save money, hide money

The investigation revealed an industry that places a premium on cost cutting and big profits, with low staffing and poor quality, endangering patient health. “Meanwhile,” the authors assert, “owners make the facilities look less profitable by siphoning money from the homes through byzantine networks of interconnected corporation
s. Federal regulators have neglected the problem as each year likely billions of dollars are funneled out of nursing homes through related parties and into owners’ pockets.”
The report points out that problems of this magnitude are found far less often in small, single-location facilities and in national chains and franchises. The sweet sport for abuse seems to be in the mid-range, for-profit organizations that have been taken over by far-away investors. Sadly, 72 percent of the SNF’s in this category are for-profit. “While such chains account for about 39 percent of all facilities, they operate 11 of the 15 most-fined facilities.
Relevance
A frequent message at Home Healthcare conferences in recent years has been the renewed interest in our sector from big money investors. While quick profits and the enticement of early retirement might bring Home Health and Home Care owners to the negotiating table, this exposé may be a reason to take a breath and think it through. Most of you who nurtured your company from startup to attractive acquisition target did so as much out of compassion as entrepreneurship. Would you not wonder, from your perch on the sun deck of a cruise ship, whether your legacy is being dragged in the mud and your patients and employees reduced to a Wall Street cost column?
Read the entire report here.
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com or Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com
by Tim Rowan | Mar 20, 2024 | CMS, Editorial
by Tim Rowan, Editor Emeritus
This week, we look at the state of the healthcare industry, vis a vis payers that do not pay.
While Home Health and Hospice leaders talk at every gathering about refusing to accept Medicare Advantage clients, some large Integrated Healthcare Systems are actually doing it. Other hospitals are responding to difficult payers by laying off staff, or even closing. The HHS Office of Inspector General repeatedly fines insurance companies for upcoding to gain inflated, unjustified monthly payments. Meanwhile, insurance companies report record profits, with their MA divisions leading the way. The fines go into the “cost of doing business” column.
March, 2024, Becker’s Hospital Review: Bristol (Conn.) Health will eliminate 60 positions, 21 of which are currently occupied and will result in layoffs at Bristol Hospital. The hospital’s CEO, Kurt Barwis, told a local newspaper a lack of reimbursement from insurers left the hospital without a choice but to cut staff.
October, 2023, NPR: Since 2010, 150 rural hospitals have closed. Under CMS’s “Critical Access” designation, Medicare pays extra to those hospitals to compensate for low patient volumes. MA plans do not. Instead, they offer negotiated rates that are lower than what traditional Medicare would pay.
December, 2023, Becker’s Financial Management: 13 additional hospital systems cut ties with Medicare Advantage plans since October.
What is going on?
The Medicare Payment Advisory Commission, MedPAC, believes it has learned the answer. In its March 15, 2024 report to Congress, the Commission called for a “major overhaul” of Medicare Advantage policies. It says it found that the program, designed to lower costs and extend the lifespan of the Medicare trust fund, does not save money but costs the fund more than if all beneficiaries were on traditional Medicare, $83 billion more in 2024.
Calling it, too politely, “coding intensity,” MedPAC concurs with the OIG that MA plans routinely exaggerate patient conditions. The report claims it will amount to MA clients appearing to need 20% more healthcare than fee-for-service beneficiaries, when they do not. Padded coding, MedPAC says, will increase Medicare premiums by $13 billion in 2024.
“A major overhaul of MA policies is urgently needed for several reasons,” the commission wrote in its report. MedPAC cited several problems that need to be addressed, including the disparity in costs between beneficiaries in fee-for-service Medicare and MA, a lack of information on the use and value of supplemental benefits, and challenges setting benchmark payment rates.
A proposal currently making its way through Congress would reduce supplemental payments to insurers, who threaten to raise premiums and cut benefits if their inflated benchmark payments are lowered.
“If payments to MA plans were lowered, plans might reduce the supplemental benefits they offer,” MedPAC wrote in its report. “However, because plans use these benefits to attract enrollees, they might respond instead by modifying other aspects of their bids.” The barrage of TV ads, featuring aging celebrities, have been found to be deceptive and too often backed by shady front companies representing brokers, not insurance companies. The brokerage company behind the Joe Namath ads, for example, has reorganized and changed its name three times.
Pushback from AHIP, the insurance industry lobbying organization, has been as expected. “MedPAC’s estimates are based on ‘speculative assumptions’ and ‘overlook basic facts about who Medicare Advantage serves and the value the program provides.'”
MedPAC asserts that its estimates are based on history, not speculation.
Healthcare Providers Beg to Differ
A lack of payments from Medicare Advantage plans is one reason the Connecticut hospital is laying off staff, the Hartford Courant reported March 14. CEO Kurt Barwis told the newspaper Medicare Advantage plans have been denying claims more frequently while delaying payments for the claims they do approve. “Our primary care is to take care of patients, their single focus is shareholder value and profits,” Mr. Barwis told the Courant. “The Medicare Advantage abuse is outrageous.”
The strategy insurance companies deploy to avoid providing care, Barwis continued, is excessive prior authorizations, coupled with delayed payments. This obstacle to care is directly in opposition to CMS policy. MA divisions of large insurers respond that they are private insurance and allowed to impose their own treatment approval policies. MedPAC says this claim is incorrect.
Richard Kronick, a former federal health policy researcher and a professor at the University of California-San Diego, said his analysis of newly released Medicare Advantage billing data estimates that Medicare overpaid the private health plans by more than $106 billion from 2010 through 2019 because of the way the private plans charge for sicker patients. Kronick added that there is “little evidence” that MA enrollees are sicker than the average senior, though risk scores in 2019 were 19 percent higher in MA plans than in original Medicare. That gap continues to widen.
Where does this excess taxpayer money go?
2023 Medicare Advantage business division profits and 2022 CEO compensation reported by publicly traded companies:
UnitedHealth Group: $22.4 B (Andrew Witty $20,865,106)
Aetna (CVS): $8.3 B (Karen Lynch $21,317,055)
Elevance Health (Anthem): $6 B (Gail Boudreaux $20,931,081)
Cigna: $5.1 B (David Cordani $20,965,504)
Centene: $2.7 B (Sarah London $13,246,447)
Humana: $2.5 B (Bruce Broussard $17,198,844)
We found one curious outlier. Molina Health, with annual revenue 10 percent of UnitedHealth Group’s income and 2.16 percent of the market, paid its CEO $22,131,256 in 2022.
Download the entire MedPAC 2024 report here. Chapter 7 is the Home Health section. A summary of MedPACs recommendations begins the chapter thus, “For calendar year 2025, the Congress should reduce the 2024 Medicare base payment rates for home health agencies by 7 percent.”
# # #
 Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
by Tim Rowan | Mar 6, 2024 | Admin, Clinical
by Tim Rowan, Editor Emeritus
[Editor’s note: this article is based on a recorded video interview with Barbara Karnes. To see the full conversation in her own words, click here.]
For longer than most of us have been in home care, in fact, for longer than some home care workers have been alive, Barbara Karnes has lived and breathed hospice. From young nurse in 1980 to administrator to author and video producer, she continues into her mid-80’s to teach young nurses and distraught families about the dying process and the grief experience.
Last autumn, however, she was suddenly transported to the other side of the classroom. The death of her husband, a longtime chain smoker, introduced her to cancer, hospice, death, and grief from the perspective of the heart, after decades of dealing with it only intellectually. Barbara graciously agreed to speak with me late last month. Having been through the experience myself, I thought it best to wait a few months after his death to extend my interview invitation.
“I have always been the kind of person who operates out of the head more than the heart,” she began. “Putting on the shoes of a spouse caregiver, and suddenly living what I have taught for decades, put a whole different perspective on it. Even though I knew better, I sometimes did things I tell people not to do.”
She told me about the urge to do those things. “I kept pushing food and the need for nutrition on him,” she remembered. “Then, one day, I finally realized I was trying to keep him alive while his body was trying to die. And with that realization, I began to do what I always recommend everyone else do, always offer and never force.”
“As a professional, I observe the dying and grieving processes. With my husband, I was feeling it. I was in the shoes, and I responded like a family member, not like a hospice expert.”
I Wanted to Know, But He Did Not
Barbara talked about the anguish of not knowing how much time her husband had left once he was diagnosed. “When he decided that he was not going to treat his cancer with chemotherapy, that included the decision not to bother with a lung biopsy just to see what type of cancer he had. ‘If I’m not fighting it, what difference does it make what kind it is?’ he said, and I couldn’t argue. There are fast and slow kinds [of lung cancer] and I wanted to know which it was so I could prepare myself. With my knowledge, I could have estimated how long his death process would take and known when to begin hospice care. I hoped it was one of the slow-growing types rather than small-cell carcinoma, but I realized that was a wish on my part, not realistic, and not what he wanted.”
Hospice Has Changed
In a side conversation, Barbara reminisced about the way hospice care was conducted in her early years as an RN and turned it into advice for today’s nurses.
“Our goal was always to be there with the family at the moment of the patient’s death. Today, hospice is much more medical, more medication oriented. I like the “End-of-Life Doula” movement today. Their companion model reminds me of the way we used to do hospice.”
As it turned out, he was diagnosed in May and passed away in September. He entered hospice right after Labor Day, even though she called to arrange services the Friday before. “Hospices should not do that,” she asserted. “When people are dying, holidays should not be a reason to delay starting care.” Nevertheless, due to this combination of circumstances, a fast-acting cancer and a slow-acting hospice, the husband of a foremost expert on death and grieving was in hospice for the all too common two weeks.
“To be fair, he was driving himself to massage appointment through August,” she clarified. “It was the day he was unable to get off the massage table that we knew it was time.”
Sometimes the Heart Wins
“It was as though I had a split personality,” she said, as I tried to gently encourage her with more personal questions. “There were parts of me that, from the day he was diagnosed, were thinking about him dying. There were parts of me, intellectually, that knew but didn’t want to see all that was unfolding. It’s a kind of confusion.”
Finally, the renowned Barbara Karnes offered the conclusion I had hoped to hear but was reluctant to directly ask. “I don’t know if my knowledge helped or not. There were signs, but I didn’t want to see them. When you’re in it, it is a different experience than when you’re teaching about it.”
# # #
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
by Tim Rowan | Feb 7, 2024 | Admin, Vendor Watch
by Tim Rowan, Editor Emeritus,
Advertising in The Rowan Report comes with a few perks! Our CEO interview with Tim is one of them. Advertisers with a full-year contract receive one annual CEO interview with Tim. If you’re not an advertiser, CEO interviews can be purchased as well. Highlight the expertise of your leadership with a one-on-one industry overview and company update with Tim, published on The Rowan Report website, social media, and YouTube channel.
Click on these titles to view each episode of our “Meet the CEO” video interview series.
Andre Gomez, Bedrock Healthcare at Home, January 2024
Rich Berner, Complia Health, December, 2022
Emmet O’Gara, Sandata, September, 2022
Roger Shindell, Carosh Compliance Solutions, June, 2022. HIPAA risk assessment workshops
Michael Gelman, CareConnect, May, 2022, Workforce Management
Jim Bland, Seniors Home Services, November, 2021, A menu of products from remote patient monitoring to home modifications, all with revenue sharing for home care partners
Ashley Wharton and Jenna Schwartz, Savii, March, 2021, Private Duty Agency Management Software
Eric Becker, CEO, MiliMatch, on technology to improve recruiting and retention
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com
© 2024. All content is produced by The Rowan Report. All rights reserved.
by Tim Rowan | Jan 31, 2024 | Clinical, Marketing
by Tim Rowan, Editor Emeritus
Counter-intuitive but true. Over-the-top customer service, intended to delight rather than merely satisfy, creates no more customer loyalty than very good customer service.
Speaking to a crowded room at last week’s Home Care 100, Ian Goddard, of Challenger Performance Optimization, Inc., raised a lot of eyebrows when he presented findings of an extensive research project that surveyed 125,000 customers and 5,000 customer service reps across a range of unrelated industries.
- Lousy customer service discourages return customers.
- Good customer service increases customer loyalty.
- Great service leads to a high level of loyalty, but that is as high as it goes.
Over-the-top, he called it “delight service,” results in the same level of loyalty as great service.
Most people have heard the stories. Anyone who has taken a sales training class know about the Nordstrom’s employee who refunded money to a customer who was dissatisfied with a tire. She had bought the tire at that location when the building housed a tire store, before it was a Nordstrom’s.
Goddard told a similar one about a stuffed giraffe that was left behind at a Ritz-Carlton when the family left for the airport. At bedtime, the giraffe’s poor little owner was distraught. Dad called the hotel and soon began to receive photos of the giraffe “on vacation” but coming home soon. The enthusiastic employee took pictures of the giraffe sunning himself by the pool, having a drink at the cafe, and sleeping in a big comfortable bed. The little guy was at peace and slept well. The father flooded social media, singing the praises of Ritz-Carlton. “I’ll never stay anywhere else,” he proclaimed.
According to the Challenger survey, that enthusiasm does last for a while, but not forever. If that grateful dad’s next vacation is in a city without a Ritz-Carlton, or if there is another upscale hotel with a better price, loyalty takes a back seat. His social media campaign, of course, has a long-lasting ripple effect. Word of mouth today is online, not over the backyard fence.
Effortless Customer Service
The survey discovered that there is, however, one customer service experience that impacts loyalty more than any other, even more than service that delights a customer. “Your customers do not want to talk to you,” Goddard asserted. “The most important experience is the one that requires the least effort on the part of the customer. The customer service rep who acts as your advocate cuts through red tape, solves your problem, and takes steps to avoid you having to call again about the same thing. Advocacy is the characteristic of the rep who creates loyalty. Think of your own customer service experiences. If you have to work, or wait on hold, to get a problem solved or to fix something broken, you come away unhappy, meaning less loyal to the brand, even if your issue is finally resolved.
Out of eight personality types typically found in customer service positions, Goddard said, the “controller” type is the most effective. This is the agent who says, “Hold on, I’m going to take care of this for you,” and then comes back a few minutes later with, “all done, problem solved.”
Avoid the Next Service Issue
Goddard told the story of the customer with a broken vacuum cleaner belt. The service rep recognized the issue and told him, “Your replacement part is already on its way.” When he received two belts instead of one, he called back. She said, “We have learned that some customers have trouble installing the belt and they break it the first time. So, we send two, hoping they will learn what they did the first time and install it correctly with the second part.”
“Thinking forward like this vacuum cleaner company does cost a few extra cents with every replacement, but avoids a far more expensive service rep interaction in the future and cements customer satisfaction,” Goddard explained.
Effortless Service in Home Care
Ryan Iwamoto, owner of 24 Hour Home Care, interpreted this way of thinking about customer loyalty for our industry. Asking, “How do we get effortless experience into our organization?” he partnered with a company called Tethr that listens to and analyzes phone conversations. It then coaches the customer service person on ways to improve effectiveness, think like an advocate, and improve satisfaction. Realizing that his caregivers are much like customers, he uses Tethr for them as well.
From the start of the Tethr implementation to the present, advocacy on all calls increased from 26.3% to 34.1%. Difficult calls decreased from 8.3% to 7.9%. Average call length decreased from 4 minutes, 15 seconds to 3 minutes, 52 seconds. Customer Effortless Score, which was tracked at the company, region, office, and individual level, increased 39 percent. Phone calls tracked came from all customers: clients, caregivers, and referral sources.
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com
©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com