
Accountability and Sustainability in Medicare Advantage

CMS

by Kristin Rowan, Editor

Accountability and Sustainability

CMS Finalizes 2027 Medicare Advantage and Part D Changes

As part of its ongoing efforts to reduce unneccessary payments, CMS issued the 2027 Medicare Advantage (MA) and Part D announcement to “improve payment accuracy” in both programs. The changes aim to make MA sustainable, allow beneficiaries to choose the best health coverage for their needs with maximum value, and make Medicare coverage more affordable.

“CMS’ vision for Medicare Advantage and Part D is clear: a great choice for seniors and a smart deal for taxpayers. The Rate Announcement improves payment accuracy and strengthens competition based on quality—not on coding practices—helping put the program on a more sustainable path for the long term.”

Chris Klomp

Director of Medicare and Chief Counselor, U.S. Department of Health and Human Services

Rate Changes for MA Risk Adjustment Model

The Rate Announcement policy changes address coding differences between MA and traditional Medicare. MA is moving toward a risk adjustment system guided by:

  • Reducing administrative burdens for plans and providers
  • Equalizing competition for all MA plans regardless of size or resources
  • Achieving payments that accurately reflect health risk
  • Facilitating the efficient use of healthcare resources, enhanced program integrity, and greater accountability
CMS will continue using the 2024 risk adjustment model in pursuit of these changes. However, CMS will exclude diagnosis information from unlinked chart review records from risk score calculation. There is an exception from the exclusion for beneficiaries who switch MA providers. The exclusion does not apply to PACE organizations, which will continue to use a blend of the 2017 and 2024 risk adjustment models. CMS expects this change to lower payments to MA plans by more than $7 billion in 2027.

Part D Risk Adjustment Model

Deductible

Part D beneficiaries cover 100% of the costs of their prescriptions, except insulin and recommended vaccines, until the deductible is met.  The 2027 deductible will increase from $615 to $700.

Out-of-pocket maximum

After sunsetting the coverage gap phase in 2025, beneficiaries no long have an initial coverage limit. The initial coverage phase lasts until the annual out-of-pocket (OOP) maximum is reached. CMS is also using the API indexing method to establish the annual OOP threshold. The annual OOP will increase from $2,100 to $2,400 in 2027.

Calculation method

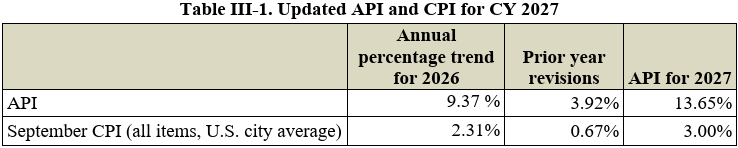
CMS can use one of two methods to update the annual deductible amount. The annual percentage increase (API) measures the average plan expenses per beneficiary. The Consumer Price Index (CPI) measures the annual percentage increase of all items across the U.S.

The 2026 API is 9.37%. The 2026 CPI is 2.31% CMS chose to use the API indexing method to set the 2027 deductible.
Accountability and Sustainability API and CPI 2027 Medicare Advantage Part D

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com


 

Hospice CARE Act

Hospice

by Kristin Rowan, Editor

Hospice CARE Act

Congress breathes new life into hospice protection

In 2024, Representative Blumenauer (D-OR) introduced the Hospice Care Accountability, Reform, and Enforcement Act. The Bill, H.R. 9803, aimed “to amend title XVIII of the Social Security Act to ensure the integrity of hospice care furnished under the Medicare program.” The House referred the act to the Committee on Ways and Means and the Committee on Energy and Commerce for consideration. The Committee on Ways and Means later referred the act to the Subcommittee on Health, where it apparently remains under consideration.

On March 18, 2026, Congresswoman Sanchez (D-CA) and Senator Warner (D-VA) introduced, or re-introduced, the Hospice Care Accountability, Reform, and Enforcement (Hospice Care) Act. According to the joint press release from its sponsors, the act will “modernize the Medicare hospice benefit, protect patients and taxpayers from fraud, and expand access to essential services and caregiver support.”

Program Integrity and Payment Reform

The two primary foci of the act are program integrity provisions and payment reforms. The hospice benefit remains largely unchanged since it began in 1982 despite significant changes in both the providers delivering and patients receiving end-of-life care. The rise in reports of fraud and abuse puts into question whether the current system can ensure both meeting the needs of patients and families and safeguard the Medicare Trust Fund.

“Hospice should provide comfort and dignity at the end of life, yet the benefit has not evolved to meet families where there is need. This bill strengthens and enhances Medicare’s hospice benefit so it provides the critical care patients and their families need – like respite care for caregivers and coverage of palliative treatments like dialysis and radiation – all while protecting the program from those trying to exploit it.”

Linda T. Sanchez

Congresswoman, D-CA

Program Integrity

According to the sponsors, the bill “creates additional safeguards to precent fraudulent providers from enrolling in Medicare and increases oversight of hospices, especially new hospices.”

Specifically, the bill:

  • Temporarily prevents new hospices from enrolling in Medicare, while allowing exceptions for instances where additional access to care is needed.
  • Requires increased transparency of hospice ownership and managing control information, ensuring CMS’s enrollment records are up to date.
  • Increases survey frequency for new hospices to ensure they meet hospice health and safety standards and prohibits payments to hospices that do not submit required quality data to the Secretary, with appropriate exceptions.
  • Reduces the potential for inappropriate financial conflicts of interest when certifying individuals’ eligibility for hospice care, while allowing nurse practitioners and physician assistants to also certify eligibility.
  • Requires CMS to conduct additional oversight activities to ensure hospices are providing holistic and comprehensive care.
  • Provides patients with an explanation of benefits within 15 days of an individual’s hospice election to increase beneficiary awareness of hospice enrollment and prevent extended periods of fraudulent billing.

Payment Reform

The bill “ensures that providers are incentivized to deliver high-quality care to individuals and their families.”

Specifically, it:

  • Revises the payment structure for routine home care to reward hospices for providing in-person care.
  • Increases payments to hospices for furnishing palliative radiation, chemotherapy, blood transfusions, and dialysis to address access barriers for individuals that require these costly treatments under a hospice election. Additionally, it creates an outlier payment policy to provide a backstop for providers delivering care to high-cost patients.
  • Adds home respite care to the Medicare hospice benefit, allowing individuals to receive respite care at home rather than in a facility, which is a key benefit for families and caregivers that are taking care of loved ones at the end-of-life.
  • Creates a new transitional inpatient respite benefit to support patients and families through their transition from a hospital into hospice care in the setting of their choice, allowing patients to move from hospital to general inpatient care to transitional respite, when appropriate. This new transitional payment seeks to eliminate the current pattern of care whereby terminally ill individuals are discharged from the hospital and inappropriately admitted to a skilled nursing facility in lieu of electing hospice care.

“Making decisions about hospice and end-of-life care is one of the most difficult moments that families can endure, yet Medicare’s hospice benefit is out-of-touch with the needs of patients and providers. I’m proud to introduce this legislation that will prioritize patient comfort at home as well as in a health care facility, and protect patients and taxpayers from bad actors attempting to steal essential resources.”

Mark Warner

Senator, D-VA

Industry Support

The Hospice CARE Act received wide-spread industry support after its introduction to Congress. 

Hospice CARE Act
American Academy of Hospice and Palliative Medicine

“Patients and families in need of the care, comfort and quality of life that hospice care provides need to trust that they are receiving the best possible services. We look forward to working with Representative Sánchez and Senator Warner on these important issues and to ensure that all patients have access to this vital care.”

– Kristina Newport, CMO for AAHPM

Center for Medicare Advocacy

“In addition to significant payment reforms and program integrity measures, this bill takes important steps towards improving access to care for individuals on hospice.”

-David Lipschutz, Co-Director for the Center for Medicare Advocacy

National Alliance for Care at Home

“Hospice care is one of the most profound services our healthcare system offers, providing patients and families with compassionate, dignified care during life’s most difficult moments. As the number of Americans turning to hospice continues to grow, it is critical that the benefit keeps pace with how care is delivered today and what patients, families, and providers actually need. The Alliance looks forward to working with Representative Sánchez and Senator Warner and their congressional colleagues on this legislation. We are committed to being a constructive partner in any effort to protect what’s working, address what isn’t, and modernize the Medicare hospice benefit in ways that serve patients, families, and the future of care in our country.”

-Jennifer Sheets, CEO for The Alliance

LeadingAge

“At its best, compassionate, high-quality, person-centered care is delivered to beneficiaries and families by ethical, forward-thinking, competent providers, in keeping with the sector’s nonprofit origins, which established a standard of quality care. Currently, however, hospice is at an inflection point. Increased scrutiny – an appropriate response to fraudulent behavior of a limited group of bad actors – highlights the need for modernization.

-Katie Smith Sloan, President and CEO for LeadingAge

National Partnership for Healthcare and Hospice Innovation

“This legislation provides an important opportunity to pursue thoughtful reforms to the Medicare hospice benefit that both preserve patient access and address ongoing concerns related to program integrity. While the bill represents meaningful progress toward modernizing the benefit and reducing incentives for fraud, waste, and abuse, NPHI believes certain provisions – particularly those related to payment reform – present opportunities for further discussion and refinement.”

– Tom Koutsoumpas, Founder and CEO of NPHI

More Information

A section-by-section analysis of the bill is available HERE
A one-pager of the bill is available HERE

Congress is on recess until the middle of April. The last few months will dictate the priorities when the next session starts, which will likely be focused on finalizing the budget and fully reopening the government. Whether the Hospice CARE Act will progress past its 2024 version is unclear. The Rowan Report will continue to monitor its progress.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Fraud and Abuse Misunderstandings

Clinical

by Elizabeth E. Hogue, Esq.

Medicare and Medicaid Fraud and Abuse

Common Misunderstandings

Providers are generally familiar with prohibitions against fraud and abuse in the Medicare and Medicaid Programs, including Medicaid waiver programs, and other state and federal health care programs, such as the VA and TriCare. Private insurers now often enforce the same prohibitions applicable to federal and state programs. But there are at least two common misconceptions about fraud and abuse.

Intent

Enforcers must prove intent in order to show that providers engaged in fraud, but providers may not understand what the government can use to show “intent.”

Premeditation

Many providers seem to think that the only way to show intent is to prove that they sat down at their desks on a Monday morning and decided to commit fraud, but court decisions tell a very different story! They say that if enforcers can prove that providers knew or should have known of a pattern of fraudulent conduct, enforcers may conclude that providers had intent. Other court decisions say that when providers show reckless disregard for a pattern of fraudulent conduct regulators can show intent necessary to prove fraud.

When providers grasp these crucial standards, it is clear that they must become vigilant to prevent patterns of fraud and abuse. This is necessary in order to prevent government enforcers from concluding that they had intent necessary to prove fraud and/or abuse.

Personal Responsibility

Many providers also may not understand that every provider, regardless of position, is personally responsible for fraud and abuse compliance.

It Rests on You

It is extremely tempting to think that fraud and abuse compliance is management’s responsibility, or the exclusive job of the Administrator/Chief Executive Officer or the organization’s Compliance Officer. On the contrary, the Office of the Inspector General (OIG) of the U.S. Department of Health and Human Services, the primary enforcer of fraud and abuse prohibitions, is quite clear that every practitioner has personal, individual responsibility for fraud and abuse compliance. 

The problem of fraud and abuse will never be solved until every practitioner takes individual responsibility for it. Enforcement action is often taken against individual practitioners, as well as members of management and owners.

Fraud and Abuse Personal Responsibility

Complete Compliance

When providers understand these two basic points, they are well along the road to active participation in fraud and abuse compliance efforts.

Final Thoughts

Providers must remember that fraud and abuse compliance is now a permanent part of the health care landscape across the nation. Compliance is not a fad that will blow over or disappear! Providers must be prepared to actively work to prevent or correct fraud and abuse for as long as they work in the healthcare industry.

# # #

Elizabeth E. Hogue, Esq The Rowan Report

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2026 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. 

MedPAC Finalizes Recommendation to CMS

Advocacy

by Kristin Rowan, Editor

MedPAC Recommends 7% Cut

Vote Finalized

In December, MedPAC published a proposed recommendation for calendar year 2027 that included a 7% cut to home health reimbursement rates and no increase for hospice. Last week, MedPAC voted to finalize that recommendation and send it to CMS. 

Industry Objection

Both the proposal and final recommendation met with strong industry backlash.

“MedPAC’s dangerous and misguided recommendations to reduce the Medicare home health base payment rate by 7% for CY 2027 and eliminate the update to the 2026 Medicare base payment rate for hospice do not reflect both home health and hospice agencies’ operating realities as well as the cumulative impact of recent policy changes. For home health agencies, any cut – let alone one of such great magnitude – will threaten the ability to meet individuals’ healthcare needs. Yet again, the Commission is failing to understand the operating reality providers face and the potential patient harm that any further payment cuts pose.”

Dr. Steve Landers

CEO, National Alliance for Care at Home

Consistently Wrong

The MedPAC recommendation may not be built on solid data, use accurate calculations, consider Medicare Advantage and Medicaid rates along with Traditional Medicare FFS, consider the number of agencies that will go out of business, have any recommendations for maintaining nurse and caregiver hourly rates, or fairly distribute Medicare funds across disciplines, but, wait…where was I going with this? Oh, right! At least they’re consistent. MedPAC recommended a 7% decrease in Medicare payments for 2027, 2026, 2025, 2024, and 2023. They may be completely wrong, but they are dedicated to maintaining their wrongness.

Final Thoughts

Despite the years of 7% cut recommendations from MedPAC, the final numbers from CMS are rarely in line with those recommendations. We will, of course, know more when CMS publishes their proposal later this year. LeadingAge, National Association for Care at Home, individual and corporate HHAs and Hospices, and anyone else with a stake in the care at home industry, should contact their congressional representatives and CMS directly to voice concerns over these cuts.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

UnitedHealth Group Publicity Stunt

CMS

by Kristin Rowan, Editor

UnitedHealth Group Publicity Stunt

How to Distract the Public: 101

When customers and regulatory bodies start to complain about company practices, reputation management usually gets involved. An internal or external public relations, crisis communication, and/or reputation management specialist advises the company on how to overcome negative press.

Transparency & Action

When Dominos Pizza employees recorded a disturbing “hoax” video, the CEO went to the same medium (YouTube) to address the video, apologize, and reassure customers. This issue was handled so well that it is used as a teaching tool in PR classes.

In 1982, when a couple tampered with bottles of Tylenol in Chicago and seven people died, parent company Johnson & Johnson stopped advertising, recalled 31 million bottles across the country, switched to tamper-proof packaging, and personally communicated with 450,000 retailers.

Subterfuge, Smoke & Mirrors

Last week, when UnitedHealth Group, already under investigation for bribing nurses, wrongful death, and Medicare Advantage billing fraud, was called to testify before House committees about their record-high premiums, rising claims denials, and unneccessary waiting over prior approvals, UHG CEO prepared a written statement to read to the Energy & Commmerce Committee that included blaming hospital costs, pricing differences, frequency of testing, drug prices, and pharmaceutical advertising for higher premium rates; extolling the virtues of Medicare Advantage over Traditional Medicare, using incorrect and misleading information; and casually mentioning that they will “voluntarily eliminate and rebate our profits” for their ACA customers.

Gesture too Small to be Meaningful

The months long Congressional stand-off on healthcare premium subsidies continues. Affordable Care Act participants saw healthcare premiums jump over night when the subsidies expired. (Mine went up 400%).

In 2025, UnitedHealth recorded $12.1 billion in profit. But, that profit is spread out over nearly 3,000 wholly owned subsidiaries who take almost 30% of what UHG pays out in care costs. The company has increased its Medical Loss Ratio to 87% by hiring their own subsidiaries to engage in “quality improvement,” virtually eliminating ACA profit.

Of its 50 million subscribers, only about 1 million are ACA customers. Even if the company returns the ACA profits, it will return 1/50th of its profits and keep the rest. In their third quarter earnings call, UHG said it expected 2026 enrollment to be 1/3 of that in 2025. The 2026 outlook estimates an overall increase in profit to more than $14 billion, most of which will never find its way back to ACA participants.

The Truth Behind the Curtain

On January 27, 2026, just one week after the profit-sharing announcement, UnitedHealth Goup addressed shareholders in its Q4 and 2025 Earnings Call. During that call, newly appointed UnitedHealthcare CEO Tim Noel said:

 “Nearly all of our employer Group and fully insured pricing align with continued increases in care activity for 2026. In the Individual ACA market, we repriced nearly all states in response to higher medical trends and the elevated needs of ACA beneficiaries in 2025…. These actions should expand operating earnings margins for UnitedHealthcare by 40 basis points, and are expected to result in membership contraction of 2.3 to 2.8 million.”

Tim Noel

CEO, UnitedHealthcare

Other statements during the call reinforced the company’s drive toward profit.

They are focusing attention in markets where they have “complimentary wrap-around services” already in place. Which means they have owned subsidiaries to shift money to instead of lowering premium rates. Additionally, they have “narrowed [their] affiliated network…with the goal of having a more optimal alignment of physicians….”

New Speak

Throughout the earnings call, company spokespeople used terms like repositioned, streamlined, aligned, membership contraction, and repriced. They carefully avoided saying that they dropped physician services outside those they owned, removed plans that paid out too much, consolidated businesses to increase profits, lost millions of members due to price increases and other plan problems, and raised prices across the board, even on plans that were already profitable.

Final Thoughts

UHG CEO Hemsley made a few statements to Congress I agree with. Drug prices are too high. Hospital and Ambulance prices are too high. Pharmaceutical companies advertise too much and use the cost to offset tax liability.

There were also some statements Hemsley almost got right.

  • He said small businesses should be allowed to join AHPs with fewer restrictions. There should be no restrictions on industry or geography.
  • He said HSA thresholds should be lowered for HDHPs. HSAs should be available to everyone, regardless of plan, deductible, payer, or whether they are on a group, individual, or ACA plan.
  • Hemsley thinks broker compensation should be standardized in the ACA market. If payers want broker compensation, standardized or not, ACA or Medicare Advantage, the compensation should come from the payer and not be included in premiums.
  • He wants consumers to have expanded access to catastrophic plans and to allow the use of premium tax credits. All plans and payers should be available to everyone, everywhere. Increasing competition in plans and players will drive down costs.

I applaud Congress for bringing the large payers in to discuss exhorbitant premium rates, but I’m still waiting on them to take action based on the information they received. 

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

VA Updates Community Cares Contracts

Admin

by Kristin Rowan, Editor

VA Issues RFP

Updates to Community Care Contracts

Some Veterans receive care from VA providers. Non-VA providers can still provide care for Veterans through a Community Care contract with the U.S. Department of Veterans Affairs (VA). In late 2025, the VA released a Request for Proposal (RFP) for new CC contracts. The new contracts are designed to substantively change non-VA provider care to Veterans.

According to the VA, the new contracts are intended to:

  • Increase choice through an IDIQ model that allows multiple health plans to compete to serve Veterans
  • Raise quality of care by requiring plans to follow broad standards of care adopted by major health systems
  • Improve oversight and quality of care using better data, technology, and real-time management
  • Add flexibility so the VA can issue competitive task orders and remove underperforming contractors

How Does This Impact Care at Home?

The primary contractor, and therefore the ones responsible for bidding and ensuring quality of care are the health plans. So, how does this change impact home care and home health providers? Here’s how:

  • Fast changes in network participation along with sudden shifts will inevitably come as a result of plans competing and task orders changing
  • Plans will need to align with VA targets, so expect waves of onboarding, recurring pushes for credentialing, and increased local networking
  • Because the plans will be held to quality standards, you can expect that those standards will flow through provider documentation, timeliness, claims accuracy, and EVV and FWA compliance
  • IDIQ is specifically designed to allow changes in the middle of care, which means the VA and health plans can add or change rules or portal, and make revisions to edit sets during the contract

Get Ahead of the Changes

Plan to make some changes before these new Community Care contracts come to your local health plans. In order to comply with the contract requirements, your credentialing packets need to be updated to include up-to-date CAQH, insurance, licenses, and compliance. This will help minimize the lag-time before getting paid.

Anticipate Expectations

The health plans will be competing for contracts, so they will expect you to compete as well. Awarded contracts will likely be fulfilled by agencies who have a high clean claim rate and quick response to edits and denials. Whatever you are using for coding, documentation, and rules need to be validated before the new care contracts start. Complete documentation will comply with the VAs focus on better data and real-time management. Make sure your team is executing precise reports; centralize your records, documentation, and audits to prove performance records and decrease issue resolution time.

Get Ahead of the changes

Final Thoughts

Non-VA providers who want to be considered to provide care to Veterans need to show alignment with the VA’s goals to expand choice, raise quality, and increase oversight. Planning ahead by meeting those standards early will make the transition process smoother one the new contracts roll out. We will continue to provide resources and information on these Community Care contracts as they are available.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Home Care 100 Sneak Preview

Advocacy

by Kristin Rowan, Editor

Home Care 100 Sneak Preview

An Interview with Jeanette Lynn

In a few days, care at home leaders, influencers, educators, and solutions providers are set to descend on Scottsdale, AZ for the 2026 winter edition of the Home Care 100 Leadership Conference. I had the opportunity to speak with Managing Director Jeanette Lynn about this year’s theme, some of the events, and her outlook for 2026.

Home Care 100 Theme

The Rowan Report:

Jeanette, thank you for taking some time to chat today. I know how busy the week before an event is. Can you tell our readers about some of the agenda highlights for Home Care 100?

Jeanette Lynn:

The theme is the data imperative. The future will rely on becoming a data-centric organization. 

“We impact patients, partners, referral sources, payers, policy makers, and all stakeholders. We have to come to the table with the right data in the right way.”

Jeanette Lynn

Managing Director, Home Care 100

I’m very excited about the keynote address from a former employee of Pixar talking about storytelling. When we’re talking with policymakers, providers, payers, we have to tell a story and find the connection with the audience. There is also an opportunity to do a follow-up workshop with him.

Other Key Topics and Sessions

Other sessions to anticipate next week:

  • Panels of providers sharing case studies
  • Six round-table facilitated discussions that are specific to home care, home health, or hospice. Those topics are listed on the event website
  • A showcase on new approaches to being a CEO of a data-driven organization including tangible and practical takeaways on how to do it. Where is the data? Where can I find it and how do I use it?

State of the Industry

RR:

What is your industry outlook?

Jeanette

There is so much that is changing so fast. Look at the conversations around AI technology just in the last year or so. The technology is opening doors that didn’t previously exist. I’m reminded of what I recently heard from Judy Faulkner from EPIC. This is a company that has been ridiculed for some time for having closed systems, following regulations but sharing information as limited as possible; it has taken them awhile to be more patient and physician-friendly. A recent announcement said patients could now access all medical information in one MyChart system across the country.

This will shift interoperability – from patients to nurses to agencies. The demand to fix this is getting higher; we’ve been sitting on the excuse of not being able to influence reimbursement rates; but MA coming out and saying the rates are going to get lower requires that we increase efficiency and the data will help get you there.

One Answer is Interoperability

When you order food online, that company can tell you that Kathy picked up your food at 7:03 p.m., is riding a bicycle, has two stops before she gets to you, and show you the route she’s taking. We can certainly provide more information, more data, and better data for our patients.

We have to supplement existing Medicare product with other services, other approaches, that get the financial lever pulled a different way. The product is too defined, coded, and reimbursed; we need a bundled care product. It’s time everyone else sees that we have more data, information, and influence.

Home Care 100 Jeanette Lynn Interoperability

There are multiple opportunities and pathways. Our goal is to guide our members toward the ones that will work for each organization.

The Year Ahead

RR:

You’ve been at the helm long enough now that you’ve had a chance to get your feet wet. What have been your observations and what does that mean for Home Care 100 and Lincoln Healthcare Leadership for 2026?

Jeanette:

My biggest observations at Home Care 100 and Lincoln Healthcare Leadership: HC100 is a group of diverse leaders who can drive and influence change; there will be continued consolidation and the big players influence everyone else.

For me, the biggest win is after the conference hearing that one of our members initiated a new program, new deal, new partnership. We want that on steroids. We want to exponentially expand those wins.

The Intelligence group pairs advisors with intelligence group members to figure out how to put into action what you learned at the conference. We align experts to supercharge members. So we’ve relaunched the Intelligence Group as an offering year-round.

The subsets of members in the intelligence group are doing smaller in-person meetings covering particular topics. We’re looking for more organizations joining the group and expanding those events, not hosting more HC 100 events.

Final Thoughts

Speaking with Jeanette, it was so easy to see her passion and excitement for the industry, for the upcoming event, and for the members who benefit from the event. I am looking forward to the sessions she mentioned, seeing old friends and making new ones, and, of course, a little dancing and revelry after the hard work is done. 

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

LeadingAge and Alliance Join Dr. Oz

CMS

LeadingAge and Alliance Join Dr. Oz

CMS hosts listening session in LA

On January 9, 2026, CMS Administrator Dr. Mehmet Oz hosted a listening session in Los Angeles to discuss fraud, waste, and abuse in home health and hospice. Dr. Oz was joined by CMS Director of the Center for Program Integrity Kim Brandt and Director of the Center for Medicare Chris Klomp.

Statement to Dr. Oz

Representatives from both LeadingAge and the National Alliance for Care at Home attended the session. As part of their ongoing collaboration and participation in combatting fraud, waste, and abuse, the two organizations sent a joint letter to Dr. Oz regarding recommendations to strengthen program integrity.

“We strongly support CMS’s ongoing efforts to strengthen program integrity and believe that fraud, waste, and abuse can be effectively prevented and addressed while reducing burden on legitimate providers furnishing critical services in the home. As CMS continues to refine its oversight strategies, we encourage the agency to adopt measures that are analytically rigorous, operationally feasible, and take a targeted risk-based approach, consistent with CMS’s statutory authorities.” 

LeadingAge and the Alliance

CMS Fraud Prevention

CMS has identified areas of waste fraud and abuse they are actively working to combat. In 2025, CMS imposed nearly 500 payment suspension, stopping nearly $5 billion in payments. CMS identified $2.3 billion in overpayments and implemented automated edits to guard against improper payment. They also revoked Medicare billing from 4,780 providers and denied almost 112,000 claims for unnecessary services.

The Alliance

Members of National Alliance for Care at Home (The Alliance) attended the listening session with Dr. OZ, stating that program integrity is a key priority for the organization. The alliance continues to work closely with lawmakers and regulators to ensure providers are putting patients’ needs first without unnecessary or fraudulent claims.

“The Alliance appreciates the opportunity to continue our dialogue with CMS about ensuring program integrity across these essential home-based services. We share the administration’s goal of eliminating fraud, waste, and abuse in home health and hospice care, and will continue to partner with the agency as it pursues solutions that reduce the burden on legitimate providers and protect patient access to care at home.” 

Dr. Steve Landers

President, The Alliance

LeadingAge

Members from LeadingAge also attended the listening session stating that fraud in any care setting is concerning and preventable. The organization continues to work with CMS to address fraud and strengthen regulatory safeguards.

“We thank CMS for initiating this productive meeting, and for the input from Administrator Oz, Deputy Administrator and Chief Operating Officer Kim Brandt, and Deputy Administrator and Director of Medicare Chris Klomp. We look forward to continuing collaboration on this important issue.”

Katie Smith Sloan

President and CEO, LeadingAge

Interview with LeadingAge

The Rowan Report reached out to LeadingAge for a comment on the listening session with CMS. We are scheduled to speak with Mollie Gurian, VP of Policy and Government Affairs, this afternoon. We will update this article with that information immediately following the interview.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

UnitedHealth Causes Heightened Alarm

Breaking News

by Kristin Rowan, Editor

UnitedHealth Causes Heightened Alarm

Guardian Investigation Launches Probe

In July of 2025, The Guardian reported that UnitedHealth had secretly paid nursing homes to reduce hospital transfers. The investigation revealed that UnitedHealth was placing its own medical teams inside nursing homes and pushing them to cut care expenses, delay transfers, and deny care.

Senators Push for Answers

In the weeks following The Guardian report, Senators Ron Wyden (D-OR) and Elizabeth Warren (D-MA) launched their own investigation of the insurance giant’s cost cutting measures in nursing homes. Wyden and Warren sent a letter to then UnitedHealth Group leaders requesting documents and information about the nursing home incentive program.

New Allegations

A new letter from Senators Wyden and Warren states that UHG has refused to comply with the initial request. In the months since the demand for information, UHG has provided only “brief and unsubstantial answers” to their questions.

“Because you have failed to respond adequately to our inquiry – and in light of additional recent reporting – we are renewing our inquiry with heightened alarm.”

Ron Wyden and Elizabeth Warren

United States Senators

Additional Reports

The Senators’s letter alludes to recent additional reports. They were referring to a December story, also from The Guardian, reporting allegations of wrongful deaths inside the nursing home care program. In a statement, UnitedHealth denied any allegations their practices “endanger patient safety or violate ethical standards.”

No Response is a Response

When asked about the second letter, UnitedHealth Group did not respond to reporters at The Guardian. UHG leadership said in statement that they would “continue to engage” with the senators. The company’s leadership also maintains that its nursing home program “improves outcomes” and “reduces unnecessary hospitalizations.”

Unanswered Questions

UnitedHealth attended a briefing with the senators’ offices last July. During that meeting, UnitedHealth made several claims the Senators are now questioning.

  • UHG maintained their nurses are not required to contact company representatives prior to taking a nursing home patient to the hospital, but a document provided by a whistleblower alleges the opposite 
  • UHG failed to adequately explain why hospital admission rates are part of the metrics for determining bonuses
  • UHG chose not to respond to questions about pending wrongful death lawsuits for Mary Grant,  Cindy Deal, and an unnamed nursing home resident in New York

Deadline to Comply

Senators Wyden and Warren allege that UnitedHealth Group has withheld internal documents that directly relate to their initial request for information. The senators gave a deadline of January 28, 2026 to respond with the following information:

  • Hospitalization policies, including clinical protocols for determining when transfers are warranted, definitions of avoidable versus unavoidable hospitalizations, and whether staff must consult Optum supervisors before hospital transfers.
  • Bonus program metrics and thresholds, including how UnitedHealth determines APK limits, whether facilities are penalized for exceeding thresholds, and five years of documentation on bonus payments to nursing homes.
  • Advance directive policies, including training materials for end-of-life conversations, the mortality risk assessment tool used, and who participates in those discussions with residents.
  • Marketing and enrollment practices for I-SNP plans at contracted nursing homes.
  • Federal oversight and compliance, including any CMS sanctions or enforcement actions in the past five years.
Wyden Warren UnitedHealth Group Heightened Alarm

Failure to Respond

Without adding details, the letter states that should UnitedHealth Group fail to respond it full, they will seek answers to their questions using “all tools at the Committee’s disposal.”

This is an ongoing inquiry/investigation and story. The Rowan Report will continue to provide updates as they become available.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

House Passes Health Care Reform Bill

Regulatory

by Kristin Rowan, Editor

House to Vote on Health Care Plan

Discharge Petition Forces Vote

Since the temporary appropriations passed to reopen the government last month, the House and the Senate have been playing chicken with the health care plan for 2026. The lack of consensus threatens both Affordable Care Act (ACA) subsidies to keep health insurance rates down and the extension of the additional subsidies needed to keep the government open after January 30.

Today, four GOP members broke rank and sided with their Democrat counterparts on a discharge petition that would force a vote on the House floor on extending the subsidies. The House quickly called for an expedited vote on the Democratic-backed bill to extend the subsidies for three years without any changes.

In an uncommon move that Democrats decried as “outrageous,” House Leader Johnson closed the vote while some House members were still trying to vote. The vote against the bill passed 204-203. There are 435 voting members of the House. The subsequent vote for the Republican-backed plan passed 213-209. With 15 missing votes, the discharge petition vote may have passed.

House Speaker Johnson said it is “inevitable” that the discharge petition will come up for a vote when the House reconvenes in January.

Multiple Plans

Both Republicans and Democrats want votes on their own House bills. 

The Democratic-backed bill from Leader Hakeem Jeffries is a straight forward extension to the existing ACA subsidies with no policy changes.

The Republican-backed bill does not extend the subsidies or address them at all. Instead, it appropriates funds to pay for cost-sharing reductions that would decrease overall subsidies, lower premiums for some, and raise premiums for others.

Some moderates disagree with their own party’s leadership. Fitzpatrick (R-Pa) and Golden (D-Maine) introduced their own bill that extends the subsidies for two years and includes some eligibility changes. In addition, Gottenheimer (D- NJ) introduced a separte bill with Kiggans (R-VA) that extends the subsidies for one year and includes modest eligibility reforms. Neither petition has near enough support to force a vote.

Second Vote Today

Despite the moderates’s support of Jeffries’s bill, the House voted today on the Republican-backed bill from Miller-Meeks (R-IA). This bill also includes reform of Pharmacy Benefit Managers and provide more control for small business owners through Association Health Plans.

The vote for Lower Health Care Premiums for All Act was 213-209 (some reports say 216-211) and the bill will advance to the Senate. It is unlikely the Senate will vote on the bill before the end-of-year recess, leaving the bill undecided until the Senate returns on January 5th.

End of the Year

Both the House and the Senate will start their end-of-year recess this week. The House of Representatives is scheduled to close their session on December 18th. The Senate will conclude on December 19th. They will return to session on January 6th and January 5th, respectively.

With only two days left on the Senate calendar, they are unlikely to vote on the House bill this session. Most experts predict the bill is unlikely to pass regardless of when the vote is scheduled.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Subsidies Undecided

Medicaid

by Kristin Rowan, Editor

Subsidies Undecided

Senate cannot agree

The record-breaking government shutdown centered around one issue: extending the COVID-era Affordable Care Act supplemental subsidies. The subsidies were an additional discount for Americans within a certain income bracket. They helped make healthcare insurance through the ACA marketplace more affordable during and after COVID. The subsidies have been extended multiple times and expire at the end of the year. Senate Republicans are not willing to extend them again. Senate Democrats won’t vote in favor of any health care proposal that doesn’t include them.

Time is Running Out

Not only do the subsidies expire at the end of the year, but anyone enrolling in a marketplace plan has to apply by December 15th, leaving precious few days to find a way forward. Senate Democrats proposed a straight three-year extension of the subsidies, which failed. Senate Republicans proposed using the subsidy money to contribute to HSAs for bronze or “catastrophic” plans. That proposal also failed.

A hybrid compromise is in the works. Details have not been released but it will likely include income caps and eligibility restrictions on the subsidies as well as some HSA flexibility. Without an extension on the subsidies, premiums are expected to increase an average of 26% in 2026, although some analyses suggest premiums could go up by 73-90%.

Another Shutdown?

The 43-day shutdown that ended in November did not finalize the 2026 budget. It merely passed enough appropriations to temporarily fund some departments through January 30, 2026 and a few essential departments for longer. If the Senate and House cannot agree on the subsidy issue, we face another shutdown in February. Every shutdown impacts Medicare & Medicaid payments, approvals, and renewals.  

Experts indicate nearly 50% of people buying marketplace plans are ages 50-64. Most, if not all of them, are looking at lower cost (and lower benefit) plans or dropping insurance altogether in 2026. If insurance costs remain high, this group of 

Subsidies undecided

people will enter Medicare with poorer health, which will cost the Medicare program and tax payers more in the long run. It will cause a vicious circle of higher Medicare costs, leading to higher taxes, lower subsidies, higher premiums, fewer people being covered, and finally higher Medicare costs again.

This is an ongoing story and The Rowan Report will continue to bring you the latest news on the subsidies and the impending expiration of the temporary government funding as we head into 2026.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

CMS Proposed Changes

Advocacy

by Kristin Rowan, Editor

CMS is Making Changes

Good or Bad?

CMS is making changes across Medicare and Medicare Advantage. From Star Ratings to Prescription Drug Prices to the Hospice benefit, CMS is embracing Make America Healthy Again. Will these initiatives benefit Medicare and Medicare Advantage recipients or the insurance companies who provide the plans?

Drug Payment Model

In early November, CMS announced a plan to lower prescription drug costs for Medicaid recipients. State Medicaid programs can opt in to the GENErating cost Reductions fOr U.S. Medicaid Model (GENEROUS). The pilot program is using the most-favored-nation pricing that was recently negotiated and announced by President Trump. Most-favored-nation pricing requires prescription drug manufacturers to charge the same low rate paid in other countries.

Limited Pilot

Beginning in 2026, CMS will negotiate with manufacturers of select drugs for lower pricing. Participating states will start using uniform, transparent coverage criteria. This is not criteria for inital coverage in Medicaid, but for standardizing access to high-cost medications.

Manufacturers are not required to participate in the GENEROUS Model, but can voluntarily apply. Participating manufacturers agree NOT to seek additional supplemental rebates or discounts outside the model price.

New Medicare Advantage Policies

CMS has proposed updates to the Medicare Advantage and Medicare Part D programs. The new plan would begin in CY 2027 and includes major changes to the Star Ratings system. CMS is also seeking feedback on new ways to modernize MA. 

Star Rating Changes

The proposed changes are supposed to incentivize plans to improve care. CMS suggests removing 12 unique measures that look at administrative processes and those that don’t highlight differences between plans. Star Rating measurements of care, outcomes, and patient experience will remain. 

Request for Feedback

CMS is seeking feedback on Medicare Advantage changes, including improving competition, refining risk adjustment, and aligning quality incentives to deliver greater value. CMS is open to either a limited model test or program-wide changes. Interested parties can submit feedback through January 26, 2026. Read the Proposed Rule here. Submit your comments.

Expanding Technology-Enabled Care

CMS may finally be recognizing what we’ve been promoting for 25 years: Care improves with technology support. 

CMS Proposed Changes<br />
Technology-based Care

The ACCESS model tests a new payment approach in original Medicare to expand access to technology-supported care options. CMS aims to increase technology-supported care options to improve health and prevent and manage chronic diseases. More than two-thirds of Medicare beneficiaries are dealing with high blood pressure, diabetes, chronic musculoskeletal pain, and depression.

An interest form is now available for the 10-year Advancing Chronic Care with Effective, Scalable Solutions (ACCESS) Model test. The model test begins July 1, 2026. The application to participate must be received by April 1, 2026.

Impact

As these programs roll out between now and 2029, the impact on insurance plans, payors, beneficiaries, and taxpayers will unfold. Will lower cost prescriptions and technology-based care lower insurance rates? Payor reform may be necessary to change out-of-pocket costs. Regulations may have to further incentivize payors to increase care when costs go down, particularly with value-based care models. 

Please take a few minutes to read the details on each of these proposals, add your comments, and sign up to participate. The industry needs reform and our aging family members deserve better.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Feedback Adjusts Final Rule

CMS

FOR IMMEDIATE RELEASE
November 28, 2025

Contact:                                                        Hannah Kristan
communications@allianceforcareathome.org
202-355-1647

National Alliance for Care at Home: CMS Modifies Final Payment Rule Based on Stakeholder Feedback, but 1.3% Cut Still Undermines Access

Despite positive changes in final rule, home health leaders remain deeply concerned payment cuts will continue to impact patient access to care at home 

ALEXANDRIA, VA and WASHINGTON, D.C. The National Alliance for Care at Home (the Alliance) today acknowledged that the Centers for Medicare & Medicaid Services (CMS) made significant adjustments in the Home Health Perspective Payment System (HH PPS) Final Rule for CY 2026 in response to community concerns regarding patient access and data integrity. 

However, the Alliance remains concerned that any payment cut for home health providers will continue to compromise access for the millions of Medicare beneficiaries who rely on these services to age and recover from illness or injury safely at home.

Since 2019, Medicare home health providers have experienced severe cuts that have already led to a cascade of home health agency closures and reduced patient access to care, especially in rural and underserved communities. The cuts finalized by CMS today – 1.023% permanent and 3% temporary – will likely continue to exacerbate these trends.

Medicare Advantage Home Health Use

“While the Alliance acknowledges that CMS took into account some of the home health community’s recommended changes in its final rule, resulting in a lower payment cut for next year, a 1.3% overall reduction in payments compared to 2025 will likely result in continued reductions in patient access, the closure of more home health agencies, and more patients waiting in costly hospital settings instead of recovering safely at home.”

– Dr. Steve Landers, CEO for the Alliance

The Alliance commends CMS for revisiting aspects of its flawed payment approach, including the conclusion of permanent payment adjustments with CY 2026 (using data from CY 2020 through 2022) based on issues that CMS acknowledged with isolating PDGM behavior changes from non-PDGM behavior changes in CYs 2023 and beyond. In total, CMS’s changes from proposed to final rule amount to approximately $915 million more in payments to home health agencies for 2026. However, any cut will be detrimental in the face of years of compounding decreases, and more action is needed to help preserve integrity, stability, and predictability in Medicare’s home health benefit. While CMS reduced the amount of overpayments that inform the temporary payment adjustments down to 4.7 billion for CYs 2020 through 2024, home health agencies will continue to face several more years of temporary adjustments without additional action. 

“Home health care is among the most trusted, cost-effective, and patient-centered services in the Medicare program. The Alliance thanks its members, the broader home health community, and allied organizations and leaders for their advocacy to help achieve this substantial improvement for home health providers and patients nationwide. Congress must take further action to enact lasting reforms to the system that protect patient access to these services and ensure the sustainability of the Medicare home health benefit.” 

Steve Landers

CEO, National Alliance for Care at Home

Expanding access to home health care is essential to improving health outcomes, enhancing patient independence, and reducing healthcare costs. Research shows that when patients are unable to access clinically appropriate home health services, hospital readmissions are 35% higher, mortality rates are 43% greater, emergency department utilization grows by 16%, and total spending is 5.4% more than if patients were able to access the services they need. Protecting this vital benefit is also popular as 70% of U.S. voters are opposed to Medicare home health cuts. 

# # #

About the National Alliance for Care at Home

The National Alliance for Care at Home (the Alliance) is the leading authority in transforming care in the home. As an inclusive thought leader, advocate, educator, and convener, we serve as the unifying voice for providers and recipients of home care, home health, hospice, palliative care, and Medicaid home and community-based services throughout all stages of life. Learn more at www.AllianceForCareAtHome.org. 

© 2025 by National Alliance for Care at Home. This press release originally appeared on the Alliance website and is reprinted here with permission. For more information or to request reprint permission, please see press contact information above.

BREAKING NEWS: Home Health Final Rule

Breaking News

by Kristin Rowan, Editor

BREAKING NEWS

Home Health Final Rule

While most of us were still recovering from our Thanksgiving feast overload, CMS quietly released the CY 2026 Home Health Prospective Payment System Final Rule (HH Final Rule). In past years, CMS published the HH Final Rule on or about November 1. The HH Final Rule was delayed this year due to the government shutdown.

Payment & Policy Updates

The payment rate for 2026 will change based on multiple factors:

  • HH payment update of +2.4%
  • The final permanent rate adjustment of -0.9%
  • The final temporary adjustment of -2.7%
  • Fixed-dollar loss ratio for outlier payments update of -0.1%

The aggregated payment update for 2026 is a net decrease of 1.3%

Read the CMS Fact Sheet

Face-to-Face

The CARES Act allows Nurse Practitioners, Certified Nurse Specialists, and Physicians Assistants to order and certify eligibility for Medicare HH and establish a plan of care. CMS has updated face-to-face encounters to now allow NPs, CNSs, PAs and physicians to perform face-to-face encounters whether or not they were the certifying practitioner or one who cared for the patient prior to home health care.

Home Health VBPM

Effective in April 2026, the HHCAHPS survey will undergo changes. CMS is removing these three survey-based measures:

  • Care of Patients
  • Communications between Providers and Patients
  • Specific Care Issues

CMS is adding four measures to them measure set. These include three measures related to bathing and dressing and the Medicare Spending per Beneficiary setting measure. These changes also prompted alterations to the weights of each measure and measure category. 

The expanded model has built-in criteria for the removal of any quality measure. CMS is adding an additional criteria to the list of factors. Factor 9 reads that CMS may remove a quality measure if it is not feasible to implement the measure specificiations.

Medicare Provider Enrollment Revocation

Currently, any provider must enroll and be approved to become a Medicare provider. CMS has the authority to both approve and revoke provider Medicare enrollment. When CMS revokes a provider’s Medicare enrollment, the revocation is effective 30 days after CMS mails notification to the provider. In certain circumstances, CMS can revoke enrollment retroactively to the first date of non-compliance and consequently collect any money paid to that provider back to the retroactive date. CMS is adding to the allowable grounds for retroactive revocation.

  • If an enrolled physician or practitioner has not ordered or certified services for 12 consective months
  • If a beneficiary attests that a provider did not actually perform the services they billed

Additional Changes

CMS is recalibrating case-mix weights under PDGM and LUPA thresholds.

DMEPOS accreditation regulations will now require suppliers to be resurveyed and reaccredited annually. Additionally, CMS is increasing the amount and frequency of data accrediting organizations (AOs) submit, expanding their ability to monitor AOs, and strengthening their ability to address poorly performing AOs.

The DMEPOS Competitive Bidding Program will change, but we are still waiting for the finalized improvements. CMS will begin paying for all continuous glucose monitors and insulin infusion pumps.

Read the Final Rule and additional Documents

Final Thoughts

A decrease in pay of any amount is unfortunate. However, we applaud CMS for listening to the feedback. CMS stated, “…commenters raised concers that behavior change after CY 2022 might [attribute] to factors unrelated to…PDGM.” Changes since 2020 include the introduction of OASIS-E, the expansion of value-based purchasing, and the large increase in the percentage of Medicare Advantage enrollees.

Whatever the reason, The Rowan Report joins the National Alliance for Care at Home in commending CMS for adjusting its payment calculations. The permanent pay adjustment for 2026 is listed as the final adjustment, a positive for HH moving forward. The proposed rule issued mid-year had a net -6.4% decrease in payments for a net decrease of more than $1 billion dollars. The final rule payment adjustment has a net decrease of $220 million. Still a decrease, but much more palatable.

CMS will continue to assess the need for temporary payment adjustments for several more years. Additional adjustments (read decreases) to the payment rate will impact patient access to care. The Alliance will continue to advocate and educate members of Congress and HHS to lower or eliminate they reductions. Your advocacy and support is needed to ensure the future of Care at Home. The Rowan Report will continue to support the Alliance and other advocacy groups and share with you opportunities for advovacy.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Hospice Carve-In is Out

Advocacy

FOR IMMEDIATE RELEASE

Contact:                                                                   Hannah Kristan
communications@allianceforcareathome.org
202-355-1647

Sen. Marshall and Sen. Whitehouse Issue Letter to Senate Leadership Expressing Bipartisan Support for Policies that Preserve Medicare’s Hospice Benefit Under Original Medicare

Alexandria, VA and Washington, D.C., November 24, 2025. On November 20, Senator Roger Marshall (R-KS) and Senator Sheldon Whitehouse (D-RI) sent a letter to Senate leadership expressing strong bipartisan support for policies that preserve the Medicare Hospice Benefit under Original Medicare, including for Medicare Advantage (MA) beneficiaries, which has protected their access to high-quality, timely end-of-life care for nearly three decades. 

Repeal Special Rule

As Congress considers potential reforms to the MA program, the letter urges Senate leadership to maintain this critical safeguard and oppose any proposals that would include hospice in the Medicare Advantage program, including repeal or alteration of the Special Rule for Hospice (the Special Rule), also known as hospice carve-in.  

Hopice in MA

Despite years of attempts from Congress, the Alliance strongly opposes efforts to integrate hospice into Medicare Advantage (MA). Past attempts have revealed challenges such as administrative burdens, difficulty creating networks, and delayed payments for claims. Bringing hospice under Medicare Advantage would undermine patient choice, adversely impact timely access to care, and fragment the hospice experience for patients and families at a highly vulnerable time.

View the full letter here. 

Leave Hospice Carve-In Out

Excerpt

“MA enrollees who elect hospice currently retain the freedom to choose any Medicare-certified hospice provider, free from network limitations or prior authorization requirements. More than half of hospice beneficiaries pass away within 14 days of election, making delays in care both harmful and unacceptable. Integrating the hospice benefit into MA plan design would jeopardize this access by layering additional managed care terms (or policies) on top of an already managed and coordinated benefit.” 

Marshall and Whitehouse

U.S. Senators

Your content goes here. Edit or remove this text inline or in the module Content settings. You can also style every aspect of this content in the module Design settings and even apply custom CSS to this text in the module Advanced settings.

“The Alliance thanks Sen. Marshall and Sen. Whitehouse for listening to the concerns of the care at home community and taking action to protect our nation’s most vulnerable patient population by defending the Hospice Benefit under original Medicare,” said Scott Levy, Chief Government Affairs Officer at the Alliance. “The Alliance will continue to lead on this important public policy priority for hospice providers nationwide by advocating to preserve this sacred promise established by Congress and kept on behalf of the American people for over four decades.” 

# # #

About the National Alliance for Care at Home

The National Alliance for Care at Home (the Alliance) is the leading authority in transforming care in the home. As an inclusive thought leader, advocate, educator, and convener, we serve as the unifying voice for providers and recipients of home care, home health, hospice, palliative care, and Medicaid home and community-based services throughout all stages of life. Learn more at www.AllianceForCareAtHome.org.  

© 2026. This press release originally appeared on the National Alliance for Care at Home Website and is published with permission. For additional information or for permission to print, please see press contact above.



