Groped by Patients

Admin

by Elizabeth E. Hogue, Esq.

Groped by Patients

Just a Slap on the Wrist

Many aides in a variety of healthcare settings have been the victims of unwanted touching or groping. What should they do? In Dorothy Bills v. WVNH Emp, LLC, and Lanette Kuhnash [No. 2:22-cv-00093 (S.D.W. Va., 2022)], the Court concluded that slapping the hands of groping patients is inappropriate conduct.

In this case, a Certified Nursing Assistant (CNA), Dorothy Bills, was responsible for the care of a patient who had limited mental capacity. He could not control his actions or understand their effect. He was sexually aggressive, and staff members had already been instructed to care for him in pairs.

Dorothy Strikes Back

Dorothy Bills was in the patient’s room alone while another nurse was on her break. She moved close to the patient’s bed to speak to him because he was hard of hearing. The CNA leaned closer to the patient to provide water and to help him stay in bed as he tried to sit up. As she did so, the patient reached out and touched Ms. Bills’ breast and vaginal area. He touched her inappropriately on multiple occasions when she cared for him, so she smacked his hands in response and told him that it wasn’t nice to touch her.

A coworker told Ms. Bills that slapping the patient’s hands was abuse and she must report the incident.
Groped by Patients

Agency Policy

The provider, WVNH, had a policy that prohibited physical abuse, including any form of corporal punishment defined as physical punishment used as a means to correct or control the patient’s behavior. The policy specifically prohibited slapping patients’ hands.

Rapid Escalation

The CNA filed an incident report that said she smacked the Patient’s hands three times. She said she didn’t slap him hard enough to hurt him, but just as one would a child who was misbehaving. As a result, a report was made to adult protective services and Ms. Bills was suspended. Adult protective services dropped the allegation of neglect. The CNA’s employment was terminated and her license later expired.

Groped by Patients, and the Court

Ms. Bills filed suit several years later on the basis that her termination was wrongful because it was in retaliation for resisting sexual harassment. She described slapping the patient’s hands and scolding him to “reprimand” him “like you would a child misbehaving” in both the incident report she filed and during her deposition.  Consequently, the Court said that the only issue is whether employers are prohibited from firing employees who physically punish a patient in response to sexual harassment.

The Court concluded that smacking patients’ hands and scolding them are inappropriate activities. Physically punishing patients, said the Court, is not a reasonable means of opposing sexual harassment by them. Filing complaints and asking for protective measures is appropriate. The CNA appealed the Court’s decision to the United States Court of Appeals for the Fourth Circuit.  On April 29, 2024, the appeals court issued a decision upholding the lower Court’s opinion.

Prevention as a Cure for Being Groped by Patients

Home Care Worker Safety

Here are some practical actions that may help prevent sexual harassment of staff members by patients:

  • Providers should require staff members to document and report every instance of sexual harassment by patients.
  • Staff members who violate the policy should be disciplined.
  • Patients should be evaluated by appropriate clinical staff to determine whether medication may be helpful to address inappropriate touching.
  • Staff members should receive education and training on a regular basis about the causes of inappropriate touching and how to address it.

Final Thoughts

The bottom line is that sexual harassment is not a part of the job description of staff members and providers must take appropriate steps to protect them.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Monthly Stipends Not Allowed

Admin

by Elizabeth E. Hogue, Esq.

Medical Directors:

Monthly Stipends Not Allowed

Monthly stipends to Medical Directors for referrals of patients could cost you. Earlier this month, a hospice provider in Georgia settled claims of violation of the federal Anti-Kickback statute (AKS) and the federal False Claims Act (FCA) by agreeing to pay $9.2 million. The allegations include payments of kickbacks, including monthly stipends, to Medical Directors in exchange for referrals of patients. These practices resulted in three whistleblower lawsuits against the hospice by former employees. They will receive $1.5 million.

Marketing, not Monthly Stipends

In the meanwhile, marketing strategies utilized by post-acute providers are generating fierce competition for referrals, especially Medicare beneficiaries who need home health services! As a result, providers are appropriately committing more and more resources to marketing activities. Providers are, for example, entering into agreements with referring physicians to provide consulting services to their organizations. These legitimate relationships may easily be misunderstood by enforcers.

Consulting Physicians

First, it is important to acknowledge that providers of services in patients’ residences need consulting physicians’ services. Examples of services that are genuinely needed, from a business perspective, may include the following:

  • Consultation regarding clinically complex cases
  • Assistance with the development and maintenance of specialty programs
  • Communication with physicians who provide inappropriate orders for care, do not return signed orders on time, or are unresponsive to staff members who are seeking modifications to treatment plans

As providers know, however, these types of arrangements raise important legal issues related to potential violations of the AKS, the federal so-called Stark laws, the FCA, and state statutes that are probably similar to these federal statutes. 

Monthly Stipend Physician Consultation

Avoid Trouble with Specific Contracts

Providers are likely to avoid violations if they meet the requirements of the personal services “safe harbor” under the AKS and the contractual exception under the Stark laws. The safe harbor and exception generally require providers to pay consulting physicians who also make referrals to them based upon written agreements that require payments at fair market value for services actually rendered without regard to the volume or value of referrals received.

Practically, Providers Should:

  • Pay physicians who also make referrals
    • on an hourly basis
    • not a set monthly amount of stipends
  • Develop standardized agreements and use them consistently with all referring physicians who receive consulting fees
    • Providers cannot afford to use a variety of different agreements that may not meet applicable requirements
    • Staff must understand that they can use only the standard approved agreement and cannot modify it without advance written approval from a designated, knowledgeable individual
  • Document services rendered and the amount of time spent on these activities.
    • Documentation is crucial
    • Providers should develop and implement policies and procedures that permit payments to physicians only after appropriate documentation to support payments has been received and reviewed

  • Avoid agreements for consulting services with physicians whose services they do not actually use
    • even if they make no payments to them
    • terminate these agreements if they do not need the services covered by them or it may appear that the only purpose for the agreements is to induce referrals as opposed to a documented need for services
  • Avoid having numerous consulting physicians/medical directors
    • Although there are usually no limits on the number of consulting physicians/medical directors that providers can have at any given time, a very large number is likely to invite scrutiny by regulators and should be avoided
    • How many is too many? The number should certainly bear some relationship to the size of the provider organization and the geographic area served.
    • Beyond this general guideline, common sense must prevail. The bottom line is: does the provider have legitimate work for every consulting physician?
  • Avoid asking consulting physicians to perform commercially reasonable services that are related to the volume and value of referrals made
    • Providers cannot, for example, ask referring physicians to assist with quality assurance activities that
      • Entail their review of charts of patients whom they referred to the provider
      • Ensure the more referrals made, the more money consulting physicians make

Final Thoughts

Providers are more likely to avoid enforcement activities when they follow these practical guidelines. Violations hurt providers and referral sources alike. In view of the possible adverse consequences, expenditures of financial and other resources are certainly justified to get it right.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

Painting Pictures

Admin

by Elizabeth E. Hogue, Esq.

"Painting Pictures" of Patients

Painting Pictures in clinical documentation to achieve positive audit results. As the fight against “fraud, abuse and waste” continues, responding to audits has become an ongoing burden for many providers. Providers have repeatedly been urged to “paint a picture” of patients in clinical documentation in order to help achieve positive results. “Painting a picture” of the patient, however, may have become more difficult as the use of electronic health records (EHRs) has increased. That is, it’s difficult to adequately describe patients’ conditions when there are so many boxes to check and blanks to fill in.

Copy, Paste, Repeat

When it comes to narrative descriptions of patients’ conditions, it is extremely tempting to “copy and paste,” “cut and paste” and/or “copy forward” previous documentation in the EHR. The copy and paste feature allows users to use the content of another entry and to select information from an original or previous source to reproduce in another location. The copy forward capability replicates all or some information from a previous note to a current note, while the cut and paste feature removes documentation from the original location and places it in another location. In addition to the obvious potential problems for quality of care related to the use of these functions, auditors are understandably skeptical of documentation that repeats itself throughout patients’ medical records.

Painting Pictures of Fraud

Auditors are especially likely to deny claims that include documentation that was obviously copied using the above functions, when the information copied “sticks out like a sore thumb.” If hospice staff document, for example, that “the patient eats a lot of Mexican food” over and over in clinicians’ visit notes, auditors are understandably skeptical about whether services were necessary for a hospice patient who seems to have a continuous robust appetite or whether services were, in fact, rendered.

How to Paint the Picture

What does it mean to “paint a picture?” If a home health patient needs wound care or injections of medications, for example, the “picture” must account for why patients or their caregivers are not performing these activities themselves. Clinicians need to describe the following in a “picture” of the patient:

  • Does the patient live alone or have caregivers?
  • Why can’t patients do wound care or self-inject medications
  • Why can’t caregivers perform these activities?
  • What attempts did clinicians make to assist patients and caregivers to provide wound care and injections?
  • Why were these attempts unsuccessful?
  • What attempts were made to find other caregivers – either paid or voluntary – who might provide these types of care?
  • What were the results of these attempts to find other caregivers?
  • Despite the initial inability of patients and caregivers to render this care themselves, what efforts did clinicians make to help ensure that they became able to do so?
Painting Pictures

Get the Picture?

It’s difficult, if not impossible, to paint the above picture using only the boxes and blanks of forms in EHRs. More is needed if providers are serious about positive audit results.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

TEFCA and QHINs: Interoperability 2

Admin

by Ben Rosen, Sr. Client Success Manager, Netsmart

Interoperability

What you need to know and how it affects you Part 2

For over two decades, tech companies and government agencies have been moving toward the goal of interoperability in healthcare technology. At long last, standards and protocols are in place — and continually being improved — to support open data exchange networks. As a result, healthcare providers, including human services, post-acute providers, and specialty practices, have more opportunities to participate in alternative payment models and adapt more readily to the evolving payment landscape.

This is part two of a four-part series covering the forces that are driving interoperability, as well as the future vision of open networks, and what it all could mean to your organization. Read Part One Here.

Interoperability in Healthcare

The creation of TEFCA and QHINs

TEFCA (Trusted Exchange Framework and Common Agreement) is a national framework designed to enable seamless, secure sharing of health information across organizations. With respect to EHRs, this framework simplifies data exchange with other providers, payers and public health entities while enhancing compliance with interoperability requirements. TEFCA is touted as a nationwide federal and private data exchange network.

End goal

One of TEFCA’s main goals is to standardize data sharing, therefore reducing the complexity of managing multiple connections and enhancing the interoperability of your EHR with other systems nationwide.

TEFCA was created by the U.S. Department of Health and Human Services’ Assistant Secretary for Technology Policy (ASTP). The ASTP is contracting with the Recognized Coordinating Entity (RCE), The Sequoia Project. The RCE is tasked with governing and maintaining the operations of the entities who are electing to implement the TEFCA network, these entities are referred to as Qualified Health Information Networks (QHINs).

Interoperability
Interoperability TEFCA QHIN

QHINs

The certification process

QHINs are the entities that build the frameworks to allow data exchange as specified by TEFCA and facilitate the national exchange of health information. A single QHIN may represent dozens or even hundreds of healthcare providers, referred to as participants or sub-participants, across sectors (i.e., acute, human services, post-acute) public health agencies, health IT vendors and payers.

Applicants must build their TEFCA connection, which is then subjected to rigorous technology and security testing. QHIN applicants must also sign the Common Agreement that is countersigned by The Sequoia Project. These rigorous standards have a time limit: Each QHIN who applies must have their network built, tested and designated by the ASTP and RCE within 12 months of the application acceptance date. As of this writing there are eight designated QHINs and two candidate QHINs.

Benefits of participating in a QHIN

  • Streamlined Data Exchange
  • Compliance with Federal Interoperability Mandates
  • Access to Broader Patient Data
  • Improved Care Coordination

The market is already seeing regulatory rules and guidance tied directly to TEFCA. For instance, HTI 1 rule laid the groundwork for TEFCA and the HTI 2 rule is expanding on the process for designation, as well as codifying definitions and use cases to be exchanged via QHINs. Overwhelmingly, one of the biggest benefits to using a QHIN will be the increased types of data exchanged via the network.

The Same, but Different

Data exchange via TEFCA will look different than what we are used to with other nationwide networks today, such as Carequality, EHealthExchange or CommonWell. Via TEFCA, QHINs will exchange more robust types of data, referred to as Exchange Purposes, and will deal with higher volumes as a network. A few examples of these Exchange Purposes are clinical documentation (CCD-A), benefits determination data, public health research data, and even lab data, just to name a few.

Another benefit will be seamless connectivity. Other QHINs should integrate with EHRs to facilitate data exchange, acting as a hub that connects your system with other networks, providers and stakeholders.

Coming soon in Interoperability Part 3: Not all QHINs are created equal. How to choose the one that’s right for you.

# # #

Interoperability Ben Rosen Netsmart

Ben Rosen is a senior client success manager and business unit owner for the interoperability solution suite at Netsmart. With more than a decade of healthcare experience, Ben has led numerous initiatives to integrate healthcare systems and enhance data sharing across the care continuum. His dedication to advancing healthcare interoperability drives his active involvement in industry initiatives and standards organizations, where he provides insight for frameworks such as HL7 FHIR, USCDI and others. Ben holds a Bachelor of Science in kinesiology from Kansas State University and a Bachelor of Science in nursing degree from the University of Nebraska Medical Center.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in the Netsmart blog and is reprinted here with permission. For more information or to request permission to print, please contact Netsmart.

Shoot the Messenger

Admin

by Elizabeth E. Hogue, Esq.

Shoot the Messenger at Your Own Risk

Shoot the messenger of fraud and abuse at your peril. Providers must take seriously the concerns of employees about possible fraudulent and abusive practices. Most whistleblowers take their concerns to their employers first, especially if they are required to do so by employers’ Compliance Plans. When employers ignore their concerns or, even worse, retaliate against employees or contractors for raising issues in the first place, employees may turn to outside enforcers for assistance in addressing their concerns. Providers must take employees’ allegations seriously whether or not they are valid. Thorough investigations are required in order to demonstrate to employees that there is no problem or that the problem has been corrected.

Shoot the Messenger

Qui Tam

Private citizens may initiate so-called “whistleblower” or qui tam lawsuits to enforce prohibitions against fraud and abuse in the Medicare, Medicaid, and Medicaid Waiver Programs and other state and federal health care programs, such as VA and Tri-Care. 

False Claims Act

One of the federal statutes that allows for whistleblower actions is the False Claims Act (FCA). This Act generally prohibits providers from “knowingly” presenting or causing to be presented false or fraudulent claims for payment by the government. Whistleblowers continue to be a major source of information for government enforcers.

Whistleblower Requirements

In order to bring a qui tam action under the FCA, private parties must have direct and independent knowledge of fraud by providers against whom suits are filed. Thus, current or former employees who are familiar with providers’ practices may often initiate whistleblower actions under the FCA. As you can imagine, employees and contractors who are ignored or retaliated against when they bring possible violations to the attention of employers or partners by firing them, for example, are likely to initiate whistleblower suits.  

Here is an example:

In United States ex rel. Chorches v. American Medical Response [No. 15-3920 (2d Cir. July 27, 2017)], Paul Fabula worked as an emergency medical technician (EMT) for American Medical Response. Fabula realized that his employer fraudulently sought reimbursement from the Medicare Program by falsely claiming that ambulance services were medically necessary when they were not. Specifically, EMTs were asked to falsify electronic Patient Care Reports (PCRs) to make it appear that services were medically necessary. Supervisors printed copies of PCRs, revised them, and directed staff members to sign the revised forms.

In one instance, Fabula provided services with another staff member who prepared the PCR. A supervisor instructed the staff member to fraudulently revise the form. When the staff member refused, the supervisor directed Fabula to sign the revised form. When Fabula refused, he was fired.

Don't Shoot the Messenger

What did Fabula do? Why, of course, he filed a whistleblower suit! The message from this case and numerous others is clear: don’t shoot the proverbial messenger who brings information about possible fraud and abuse violations. Listen up!

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Meaningful AI

Admin

by Scott Green, Care Dimensions at Netsmart

Meaningful AI in Post-Acute

Elevating Care and Efficiency with Integrated AI

Meaningful AI is more than plugging your questions into ChatGPT. It goes beyond Artificial Intelligence into Augmented Intelligence. 

After a long day of caring for patients, a home health nurse pulls into their driveway, bracing for the familiar evening grind — hours of documentation. They take a deep breath, one of relief. They’re not mentally preparing for hours at their laptop, documenting every visit, trying to recall every detail while fatigue tugs at their focus. Tonight is different.

Tonight, they step through the door, greeted by their kids clamoring to show off their school projects. Dinner is already on the table, and for the first time in weeks, they sit with their family—truly present. There’s no need to pull out the laptop after dessert, no late-night race against deadlines. Their documentation? Done. Completed during patient visits, thanks to an integrated AI workflow that not only captured essential details of their patient but also highlighted critical care needs in near real-time.

This isn’t just a glimpse of what’s possible—it’s the reality Meaningful Augmented Intelligence (AI) creates for home care & hospice providers. With AI-assisted documentation tools, caregivers are freed from after-hours work. Repetitive tasks are automated, and accurate, compliant records are captured during visits. As a result, clinicians can focus on what matters most: delivering care to their patients during the day and being present for their families at night.

Meaningful Integrated AI in Care at Home: How it Works and Why It Matters

Integrated AI doesn’t just automate tasks—it enhances every part of the care process. By embedding AI directly into existing workflows, solutions empower clinicians and administrators to work smarter, not harder. Predictive analytics, real-time documentation and automated data entry reduce repetitive tasks and administrative burden, clearing staff to focus on patient care.

Unlike generic AI tools, Meaningful AI supports clinicians at the point of care. It captures essential details during visits, highlights critical needs as they arise, and offers real-time guidance. This isn’t just about making work faster—it’s about making it more human. Integrated AI simplifies workflows and strengthens decision-making, whether it’s anticipating a patient’s end-of-life needs, identifying compliance risks, or supporting proactive billing.

The AI Trifecta

AI isn’t just about automation—it’s about Meaningful AI that directly addresses the needs of community-based providers. With our AI Trifecta, every aspect of care delivery is reimagined to optimize processes, empower staff, and simplify reimbursement.

Optimize Processes

Integrated AI helps organizations operate more efficiently by taking over time-intensive, repetitive tasks, allowing staff to focus on patient care. For example, guided assist tools integrated with clinical workflows proactively coach staff through complex tasks like completing the OASIS assessment or interdisciplinary start of care documentation.

Imagine a clinician documenting care after a patient visit. With AI-powered assistance, charting can pre-fill fields based on visit details, flag potential inconsistencies in near real-time and suggest changes to align with regulatory requirements for a supervisor to review. This reduces errors and speeds up documentation, freeing clinicians to focus on patients rather than administrative tasks.

Predictive analytics empower organizations to anticipate and address challenges early, supporting clinical benefits of Hospice Visits in the Last Days of Life (HVLDL) such as symptom management, reduced patient distress and honoring the patient’s end-of-life wishes.

Empower Staff

The backbone of any agency is its staff. Integrated AI tools relieve the pressures of excessive documentation and administrative burdens. These tools aren’t just about doing tasks faster—they help create a more sustainable work-life balance by addressing challenges like burnout and turnover.

Staff can also benefit from smart task prioritization. Meaningful AI tools can include the ability to log in and instantly see a clear list of priorities based on patient needs and compliance deadlines. This reduces time spent figuring out “what’s next” so that every action directly contributes to better patient outcomes.

Meaningful AI

Simplify Reimbursement

Some AI tools monitor claims for potential issues before submission. Imagine if your system could identify a missing modifier or mismatch in coding then flag the problem and provide actionable suggestions to correct it. This not only increases first-pass acceptance rates but also reduces the exhausting back-and-forth that often accompanies denied claims.

Beyond preventing errors, predictive tools assess patterns in denial risks and reimbursement trends, enabling organizations to adjust strategies proactively. Leaders can use these insights to negotiate better contracts or refine documentation practices, ensuring steady cash flow and financial health and upstream process improvement. This empowers organizations to invest resources where they matter most: improving patient outcomes.

About Netsmart myUnity® NX

With Meaningful AI at the heart of myUnity NX, every part of the healthcare process—from care delivery to financial health—works smarter, not harder. These innovations support not just operational efficiency but also the well-being of care teams. By embedding intelligent workflows, providers have the time and space to focus on what matters most—delivering exceptional, person-centered care. Learn more about Netsmart myUnity® NX

# # #

Scott Green Meaningful AI

Scott Green leads the Care Dimensions business unit at Netsmart. In his role, he leads a team focused on building out a comprehensive suite of solutions designed to support organizations as they digitize their operations beyond the EHR. Green has been with Netsmart for 10 years and has held many roles during that time including leading the Human Services business unit.

Prior to joining Netsmart, he spent 13 years with Pfizer where he focused on building relationships and clinical initiatives with Integrated Delivery Networks.

Scott holds a bachelor’s degree in industrial psychology from Kansas State University and a graduate certificate in healthcare leadership from Park University.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared on the Netsmart blog and is reprinted here with permission. For more information or to request permission to print, please contact Netsmart. 

Industry Update

Admin

by Kristin Rowan, Editor

Industry Update with Dr. Steve Landers

At last week’s New England Home Care & Hospice Conference, Dr. Steve Landers, President of The National Alliance for Care at Home (The Alliance) gave the keynote address and offered some industry insights and updates.

A Heartfelt Introduction

Ken Albert, Chairman of the Board at The Alliance introduced Dr. Landers before his address. After reading Dr. Landers’s official biography, Albert offered his own thoughts on the first few months of Landers’ tenure.

Last year, five colleagues from organizations across the country sat in D.C. interviewing candidates. While interviewing Landers, I was remarkably engaged by someone who is deeply passionate about care at home. Steve describes hospice care as a national treasure, and I don’t disagree. More than just his passion for care at home, Dr. Landers is savvy in navigating the political paradigms driving policy. He artfully combines data and stories to navigate relationships with policy makers. What I see every day is someone who roles up his sleeves for the patients we take care of with tremendous respect for the caregivers who are in the patients’ homes.

Ken Albert

Chairman of the Board, The National Alliance for Care at Home

Industry Changes, Advancements, and Ongoing Advocacy Efforts

Dr. Landers attributes much of the positive changes in D.C. to the efforts of volunteer leaders looking to move the industry forward. Care at home needs to become more streamlined, more efficient, and with a better voice.

His vision for the care at home industry is an America where everyone can access high-quality care wherever they call home.

Strong Admonition for CMS

Dr. Landers noted positive movement in some areas. However, he became passionately adamant that a payment update is not an increase if it doesn’t keep up with inflation or pay increases. “The Alliance represents providers delivering high-quality, person-centered care to million of individuals in the home, and they deserve to be recognized and compensated for the work they do,” he said.

Our Aging Nation

It should come as no surprise that older adults have a strong preference for aging at home. They prioritize living where they feel in control and connected. They want to be in familiar surroundings and to maintain their routines.

The U.S. population over the age of 85 is expected to triple from 2020-2060 to more than 19 million people. Despite medical advances, only 1/3 of those over the age of 85 say they are free of disability or free of difficulty with daily living.

With the rising number of older individuals, caregiver to patient ratios are falling nearly everywhere across the country. Dr. Landers and The Alliance urge policymakers to make promoting the dignity and independence of our aging population one of their highest health policy priorities. The Alliance will continue to tell anyone and everyone who will listen that care at home offers the win-win solution that policymakers are looking for.

Changes at the Top

We’ve already seen numerous and sometimes drastic changes at the federal level. Dr. Landers points out that eight years ago the “Trump 1.0 Administration” developed the PDGM framework and signed hospice reform legislation. On the campaign trail, President Trump stated he would not be making cuts to Medicare. The “Trump 2.0” care at home priorities are not yet clear, but The Alliance will continue to emphasize cost savings and the preference to age in place.

Secretary Kennedy, head of HHS, placed his emphasis on the chronic disease epidemic, launching Making America Healthy Again. He has stated a preference for community-based solutions and patient-centered care.

New CMS Administrator Dr. Oz seems to be supportive of Medicare Advantage, but did have some critique of the program during senate hearings. Dr. Oz has a stated focus of finding and eliminating fraud, waste, and abuse.

Changes Near the Top

At the congressional level, The Alliance lost a few key supporters with the last election, but many care at home advocates remained. Of the returning members of the Senate and House, care at home advocates include:

  • Senators Collins (R-ME), Hassan (D-NH), Tillis (R-NC), Barrasso (R-WY), Blackburn (R-TN), CortezMasto (D-NV), and Rosen (D-NV)
  • Representatives: Adrian Smith (R-NE), Sewell (D-AL) Van Duyne (R-TX), Panetta (D-CA), Guthrie (RKY), and Carter (R-GA)

The support in Congress leaves us hopeful. Large Reconciliation Packages dominate the current conversation. Many questions remain as to what is at risk for care at home and what Medicaid’s future might hold.

Later this year, The Alliance sees opportunities for care at home outside of reconciliation. These include Home Health PDGM reform, hospice reform, the telehealth extension, revocation of the Medicaid HCBS 80/20 rule, tax credits, and long term care insurance.

Public Policy Priorities

As The Alliance moves forward, several key issues will remain priorities:

Access to Care at Home

  • PDGM Implementation
  • Telehealth Extension
  • Medicare Advantage Dynamics
  • Care for High Needs Beneficiaries

Quality Care at Home

  • Special Focus Program Implementation
  • DEA Telehealth Provisions
  • HOPE tool implementation?

Eliminating Fraud and Abuse in Care at Home

  • Hospice Concurrent Care
  • Hospice and Medicare Advantage
  • Medicaid 80/20 Rule
  • Caregiver Tax Credits / LTCI

Growing the Care at Home Workforce

  • Supply is simply not meeting demand
  • Strengthened rates, incentives, and educational opportunities will attract and retain a qualified workforce
Industry Update with Dr. Steve Landers

Follow Up

I spoke with Dr. Landers after the keynote address to ask him why lone worker safety was not among the top priorities of The Alliance. He assured me that there is a position within The Alliance who, among other tasks, is focusing on lone worker safety. I urged him to make it a higher priority and will follow up to get the contact information for the position he mentioned.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

That’s a No-No

Admin

by Elizabeth E. Hogue, Esq.

No-no # 1

“No-No” may seem like something you would say to a toddler, but there is a list of things agency owners do that they should not do. Many of these are things providers may not often consider. This article focuses on the use of private duty services by hospice and home health patients, and what hospices and home health agencies cannot do with regard to aide services.

Aide Services

Both home health and hospice services are usually intermittent and provided in patients’ homes.  Patients and their families may elect to utilize the services of private duty/home care companies for additional assistance. At the same time, hospice and home health patients may receive aide services from hospices and home health agencies. 

Conditions of Participation no-no

Conditions of Participation

According to Medicare Conditions of Participation (CoPs), hospice and home health aides can only provide personal care services, including bathing. Aides provided by private duty/home care companies may also provide personal care. Unlike aides provided by hospices and home health agencies, however, they can provide additional services; such as laundry, food preparation, light housekeeping, shopping, and running errands.

Private Duty Services

When patients use private duty services, they are often paying for these services out of their own pockets. Even if they have long-term care insurance, patients still bear the financial burden of paying for private duty services. Longterm care insurance often costs thousands of dollars that patients probably paid for themselves. Patients usually pay by the hour for these services. 

Private Duty Aide Services No-No

That's a No-No

Patients may, of course, utilize private duty/home care services to perform any of the services described above. It seems, however, that hospices routinely tell patients who have private duty/home care that they will not provide aide services because private duty/home care aides are able to provide personal care for patients.

Breaking it Down

Here is an example: A hospice admitted a bedridden patient with urinary and fecal incontinence. The patient and caregiver requested aide services from the hospice five days a week to bathe him. He paid for a few hours of private duty/home care services each day. The hospice refused to provide aide services five days a week to bathe him because he had private duty/home care services. No-no!

Compelled to Provide Care

ospices must provide aide services consistent with patients’ needs related to their terminal illnesses. In the example above, the patient clearly had a need for aide services five days a week. If patients and their caregivers state that they prefer to use private caregivers for personal care, then hospices must document the refusal of hospice aide services offered, consistent with applicable standards of care. Then hospices are not required to provide aide services.

Profiteering

When hospices deny aide services that are consistent with applicable standards of care and require patients and caregivers to use private duty/home care services, hospices are shifting the cost of aide services onto patients and their families. Patients and their families may have to pay for additional private duty/home care services to meet patients’ needs. The result for hospices is that they do not incur the costs of aide services, thereby increasing their profits at the expense of patients and their families. 

If hospice staff members who refuse to provide aide services to patients and require patients and their families to use private duty/home care services instead are compensated in any way based on the financial performance or profitability of the hospices, let’s hope they look good in orange jumpsuits!

Intent to Defraud

If the private duty/home care services are being paid for by any federal or state health care program; such as Medicaid, Medicaid waiver, VA, or TriCare; then both home health agencies and hospices have engaged in fraudulent conduct by shifting costs that they should have incurred onto other federal government programs. 

God forbid that the hospice also owns the company from which patients receive private duty/home care services! Then hospices are limiting their costs while profiting from patients and their families.

Dig Deep and Find Your No-No's

Now is the time for all home health agencies and hospices especially to audit patients’ records to make certain that all patients have been offered services that they are required to provide. If patients and their families choose to use private duty/home care aides instead, documentation must show that they were offered the services but chose to use private duty/home care aides.

No-No's Final Thoughts

The bottom line is that hospices and home health agencies must always provide services needed by patients.  Patients may choose to pay for services that are paid for by the Medicare hospice or home health benefits. Patients cannot be required to pay for services privately that hospices and home health agencies must provide. Unacceptable!

This article is the first in a series of “No-no” items for agency owners.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Relief for Providers

Admin

by Elizabeth E. Hogue, Esq.

Relief for Providers from Devastating Penalties?

A judge in the Northern District of Texas recently decided that even the minimum penalties mandated under the False Claims Act (FCA) violate the Eighth Amendment’s Excessive Fines Clause [see U.S. ex rel. Taylor v. Healthcare Associates of Tex. (N.D. Tex. Feb. 26, 2025)]. The FCA punishes providers for submission of information that is not true in order to get paid by the federal government.

Life Threatening Penalties

The penalties assessed against providers under the FCA may be described as “life threatening.” That is, it may be difficult for providers’ businesses to survive payment of such severe penalties. The minimum penalty increased from $13,946 to $14,308 in 2025. The maximum penalty per claim increased from $27,894 to $28,619.

Ex Post Facto

These increased penalties will be assessed for violations that occurred prior to the change, but that are assessed after they are in effect. These penalties certainly make it clear why it is difficult for providers to survive violations of the FCA.

False Claims

In the Taylor case above, for example, the defendants allegedly submitted false claims as follows:

  • As “incident to” a physician’s care without proper documentation
  • For services by providers who were not eligible to bill the Medicare Program
  • For services performed by medical assistants instead of qualified practitioners
Ex Post Facto

FCA Math Doesn't Add Up

The jury found that one of the defendants, a primary care medical group practice, submitted 21,944 false claims for $2,753,641.86 in actual damages. After trebling the damages as required by the FCA, the Court said it would enter judgement against the defendant for approximately $8 million. The Court acknowledged, however, that penalties under the FCA are fines subject to the Eighth Amendment of the U.S. Constitution.

Gravity of Penalties

Grossly Disproportional to the Gravity

The Court then applied the following four factors to decide whether the “fine was grossly disproportional to the gravity of the offense” under the Eighth Amendment:

  • The essence of the defendant’s crime and its relationship to other criminal activity
  • Whether the defendant was within the class of people for whom the statute of conviction was principally designed
  • The maximum sentence, including the fine that could have been imposed
  • The nature of the harm resulting from the defendant’s conduct

Fraud...or a Reporting Error?

With regard to the first factor, the Court emphasized that the defendant’s misconduct involved violations of Medicare billing rules, but did not include billing for services that were not provided. In fact, the Court said that even though the defendant violated Medicare billing rules, the misconduct was “closer in gravity to something like a ‘reporting offense.’” There was, said the Court, no evidence that the defendant’s conduct was “related to other criminal or fraudulent activity.

Magnitude of Harm

The Court also focused attention on the fourth factor. The defendant’s harm was certainly significant, but the harm, according to the Court, did not necessitate a penalty “two orders of magnitude greater than the actual financial harm,” especially when the actual damages were substantial, i.e., one hundred times the amount of actual damages. That ratio was “grossly out of alignment with the ratios in other similar cases.” The Court imposed a civil penalty of $8,260,925.58 that represents less than 3% of the statutory minimum.

Final Thoughts

Whether other Courts follow the Taylor case described above remains to be seen, but it is quite clear that providers need relief from the penalties of the FCA.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

HIS to HOPE

Admin

by Vicki Goodman, CRO at Curantis Solutions

HIS to HOPE Transition in Hospice Care

What You Need to Know

As a hospice nurse, I am excited to share pivotal news that will significantly impact our field starting October 1st. In case you have been living under a rock, we are transitioning from the Hospice Item Set (HIS) to the Hospice Outcomes and Patient Evaluation (HOPE). This change is not just a modification in terminology; it represents a transformative shift towards a more patient-centered and holistic approach to hospice care. In this article, we will explore what this transition entails, its benefits, and how it will affect our daily practices.

Understanding the Transition from HIS to HOPE

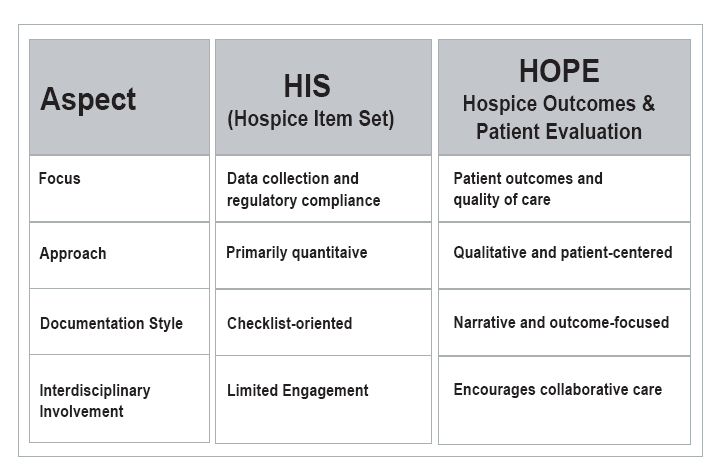
The move from HIS to HOPE signifies an essential evolution in our approach to patient care. While HIS primarily focused on data collection and compliance with regulations, HOPE emphasizes measuring patient outcomes, quality of care, and overall patient experience. This transition encourages us to engage more deeply with our patients and their families, ensuring that their unique needs and preferences are at the forefront of the care we provide.

What is HOPE?

HOPE stands for Hospice Outcomes and Patient Evaluation. This new framework highlights several core principles:

  • Patient-Centered Care
    • Focusing on individual patien needs and preferences
  • Quality of Care Assessment
    • Evaluation how well we meet those needs
  • Holistic Approach
    • Considering emotional, spiritual, and psychological factors in addition to physical health

Benefits of HOPE in Hospice Care

The adoption of the HOPE framework offers numerous advantages for both patients and healthcare providers:

  • Improved Patient Engagement
    • By prioritizing patient preferences, we can foster stronger relationships and enhance the overall care experience
  • Enhanced Quality of Care
    • Focused outcomes assessment allows us to identify areas for improvement and implement best practices
  • Recognition of Care Quality
    • HOPE enables us to demonstrate the effectiveness of our care, leading to greater recognition of our contributions in hospice settings

HIS to HOPE Key Differences

Understanding the distinctions between HIS and HOPE can help clarify the shift in our practices. Here are some key differences

HIS to HOPE Vicki Goodman Curantis Solutions

The Role of Hospice Nurses in the HOPE Framework

As hospice nurses, our role in implementing HOPE will require a significant mindset shift. Here’s how we can adapt our practice:

  • Engage With Patients and Families
    • Actively involve them in care planning and decision-making
  • Assess Holistically
    • Look beyond clinical data to include emotional and spiritual assessments
  • Collaborate with Interdisciplinary Teams
    • Work closely with all caregivers to ensure a comprehensive approach to patient care

By integrating these principles into our daily practice, we can enhance patient experiences and outcomes, ultimately providing the compassionate care that is the hallmark of hospice services.

Acknowledging Our Impact

As we transition to the HOPE framework, it’s essential to take a moment to give ourselves credit for the incredible work we already do. For most of us, patient-centered care has been at the heart of our practice long before HOPE was introduced. This new framework serves as validation, providing a structured approach to highlight the compassionate, individualized care we consistently offer.

Getting Prepared

The transition from HIS to HOPE marks an important chapter in the hospice care journey. Prepare for the transition with partners who understand the complexities and challenges that come with such significant changes. Specifically, work with a software and service company designed to ensure that your hospice team can seamlessly adapt to the HOPE framwork without sacrificing the quality of care. 

About Curantis Solutions

From comprehensive training to state-of-the-art data management systems, we provide everything needed to make this transition as smooth and effective as possible. With Curantis Solutions, you can be confident that no matter how the standards evolve, you will always be at the cutting edge, providing compassionate, patient-centered care. t Curantis, we understand the unique challenges faced by hospice and palliative care organizations. Our commitment to providing exceptional support ensures that you can focus on what matters most—delivering compassionate care to your patients. We pride ourselves on our quick response times, we deeply listen to our clients, and are easy to get ahold of when you need us. When partnering with Curantis Solutions, we guarantee we have support you can depend on.

# # #

Vicki Goodman
Vicki Goodman

Vicki Goodman, RN, BSN, MHA is an accomplished healthcare professional with a strong background in post-acute care, SaaS sales. With a proven track record of driving revenue growth, Vicki has successfully orchestrated sales strategies and marketing initiatives with over 30 years of experience in the home health and hospice EHR industry. Prior to joining Curantis Solutions, Vicki was VP, Enterprise Sales at Matrix Care.

She is an RN and BSN graduated of East Carolina University and received her MHA from University of North Carolina at Chapel Hill. She credits a lot of her success to collaborating with product and marketing teams creating an unstoppable engine. We are thrilled to have her join the Curantis Solutions family and look forward to the continued growth under her leadership.

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Dr. Oz Nomination Advances to Full Senate

Admin

by Tim Rowan, Editor Emeritus

Dr. Oz Nomination Advance to Senate

“Given your close ties to the industry that you would regulate, if you are confirmed, the public would have reason to question your impartiality and commitment to serving the public’s interest.”  — Senator Elizabeth Warren, letter to Dr. Mehmet Oz

Reuter’s Ahmed Aboulenein reported on March 12 that “Warren called on Oz to divest from his financial holdings related to industries regulated by the agency and commit to strong ethics safeguards.” Oz, of course, is President Donald Trump’s nominee for CMS Administrator, the agency most important to Home Health and Hospice providers.

Across the aisle, Missouri Senator Josh Hawley peppered Oz with questions about his position on transgender therapy. “You previously praised trans surgeries for minors and supported the use of puberty blockers for children. You discussed transgender therapy on your TV program and hosted transgender children.”

Hawley also questioned Dr Oz’s previous comments on abortion, adding: “I hope he’s changed his views to match President Trump! We need the Trump agenda at CMS.”

It goes without saying that a nominee who encounters challenges from the left and the right is facing an uphill battle toward Senate confirmation, especially when nominees this year can only afford to lose three votes from the majority party. What exactly has Dr. Oz said or done over his long career that may put his nomination in jeopardy?

Pulling Back the Curtain

Becker’s Hospital Review summarized Oz’s history as well as his answers to questions during his three-hour Senate hearing on March 14.

“The former TV personality answered questions about potential Medicaid cuts, the focus of the House’s February budget instruction that the Energy and Commerce Committee cut $880 billion over 10 years. Medicare and Medicaid are the largest programs under the committee’s oversight. (A March 5 Congressional Budget Office report said the only way to reach the $880 billion saving goal over the next decade, without raising taxes, would be through Medicaid or CHIP cuts.)”

While Dr. Oz did not directly respond to questions or reveal his stance regarding Medicaid cuts, he did have a prepared non-answer for the Senators. “I commit to doing whatever I can, working tirelessly to ensure that CMS provides Americans with superb care. Especially Americans who are most vulnerable. Our young, our disabled and our elderly.”

CMS Administrator Nominee Dr. Oz

On March 25, the Senate Finance Committee voted to advance Oz’s nomination to the full Senate. The panel voted 14 to 13, along party lines. 

Vision Statement

Prior to facing the challenging questions thrown at him from both sides of the aisle, Dr. Oz used his opening statement to outline a vision focused largely on modernizing CMS’s systems; addressing waste, fraud and abuse; and incentivizing Americans to make healthier lifestyle choices.

In the past, Oz had endorsed privatizing Medicare through a change that would essentially result in something that might be called “Medicare Advantage for All.” In his Senate hearing answers, Oz pivoted to the opposite argument. He cited problems of overpayments to Medicare Advantage plans, the need to limit prior authorizations, and emphasized the need to halt the practice of “upcoding” where providers or plans bill for treating patients as sicker than they actually are.

In 2010, Dr Oz hosted a 15-minute segment on his show called “Transgender Kids: Too Young to Decide?” in which he spoke to transgender children, their parents and a doctor who provided gender-affirming care.

Outlook

Considering the slim Republican majority in the Senate, Ox can afford to lose only three Republican votes in his bid to become the next CMS administrator.

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Ensuring HIPAA Compliance in Healthcare Communication

Admin

by Devin Paullin, CGO at Skyscape Buzz

Ensuring HIPAA Compliance

Communications Requiring HIPAA Compliance

While patient communication requires HIPAA adherence, so does any discussion between other parties. Essentially, any time PHI is discussed, a degree of confidentiality must be involved. For example, the Health Insurance Portability and Accountability Act (HIPAA) requires that sensitive patient data be protected when shared or discussed among:

  • Healthcare Providers and Patients
    • Any time a caregiver, staff member, doctor, nurse, or any other employee communicates with a patient, resident, or client, outside of face-to-face meetings, it must be done securely in a way that meets HIPAA standards.
  • Healthcare Professionals Among Themselves
    • HIPAA compliance must be met when healthcare professionals discuss PHI within their department or collaborate with external departments.
  • Healthcare Providers and Insurance Companies
    • Insurance providers require patient details and sensitive PHI. Still, anything that makes information vulnerable to interception must be fully compliant with HIPAA standards.
  • Healthcare Organizations and Third-Party Associates
    • Third parties that need to handle PHI (e.g., IT consultants, collections agencies, or other vendors) must do so in a way that protects patient data. To safeguard communication, healthcare organizations should ask outside associates, vendors, or agencies to sign a business associate agreement (BAA) and/or Data Processing Agreement (DPA). This is a formal agreement to comply with HIPAA standards and ensure accountability.
  • Healthcare Organizations and Public Health Authorities
    • Some diseases or conditions require healthcare professionals to report to public health authorities (e.g. COVID-19 information during the pandemic). This communication requires stringent security measures and protection of PHI.

Why HIPAA Compliance Matters

In healthcare, effective communication is essential for providing high-quality care. However, without HIPAA compliance, the risk of data breaches increases. Implementing secure, HIPAA-compliant communication systems ensures the protection of Personal Health Information (PHI) while improving overall operational efficiency.

Key Benefits of HIPAA-Compliant Communication

  • Protects Patient Privacy and Data Security
    • HIPAA-compliant platforms use advanced encryption and access controls to prevent unauthorized access. This protects patient information, including medical histories, diagnoses, and test results.
  • Enhances Communication Efficiency
    • Secure messaging platforms streamline communication between patients, caregivers, and healthcare providers. These tools eliminate inefficient methods like phone calls and ensure real-time communication.
  • Strengthens Collaborative Care
    • Providing high-quality healthcare often involves a team of professionals working together. Whether it is a hospital placing a patient in rehabilitation or home care, coordinating with intake team, care team and providers,collaboration is key. HIPAA-compliant communication tools allow these professionals to securely share critical patient information, ensuring everyone has the details they need to deliver cohesive, well-informed care.
  • Reduces Legal and Financial Risks
    • Compliance with HIPAA regulations minimizes the risk of violations, protecting organizations from hefty fines and legal repercussions.
  • Maintains Patient Trust
    • Patients are more likely to engage openly with healthcare providers when they feel confident that their sensitive information is protected.

How to Ensure HIPAA Compliance in Communication

To comply with HIPAA regulations, healthcare organizations should adopt the following secure communication methods:

  • Encrypted Emails
    • Ensure emails containing PHI are encrypted and, in some cases, require patient consent.
  • Secure Messaging Platforms
    • Use platforms specifically designed for HIPAA compliance for text-based communication.
  • HIPAA-Compliant Voice Calls and Telehealth
    • Ensure voice and video communication channels are encrypted and secure.
  • Patient Portals
    • Provide secure portals with two-factor authentication for patients to access their medical information.
  • Secure File Sharing
    • Use encrypted systems for sharing patient documents and medical records.

Implementing HIPAA-Compliant Communication Platforms

Adopting a HIPAA-compliant communication platform requires a thorough evaluation of existing systems and policies. Organizations should consider the following steps:

  • Conduct a Communication Audit
    • Identify all channels currently used for healthcare communication and assess their compliance.
  • Choose a Secure Platform
    • Select an all-in-one communication solution designed to meet HIPAA standards.
  • Establish Access Controls
    • Implement role-based access to ensure only authorized personnel can view PHI.
  • Provide Staff Training
    • Educate employees on the importance of HIPAA compliance and how to use secure communication tools.
  • Monitor and Evaluate
    • Regularly assess communication practices to identify and address vulnerabilities.

Final Thoughts

HIPAA-compliant communication is not just a legal obligation—it’s a commitment to patient privacy, security, and high-quality care. By implementing secure communication platforms, healthcare organizations can enhance efficiency, foster trust, and reduce the risk of data breaches. Investing in compliance is an investment in the long-term success and reputation of your organization.

# # #

Devin Paullin HIPAA Compliance in Home Healthcare

Devin Paullin is an award-winning innovator and executive in Healthcare Technology, having developed successful products, solutions, and partnerships in Life Sciences, Post-Acute Care, SDOH, and Long-Term industries.

He is currently Chief Growth Officer for Skyscape which provides Buzz, an all-in-one, real-time HIPAA-compliant clinical collaboration and communication platform that enables the entire staff (admins, operations, clinicians, caregivers, partners, patients, and families) with the tools to communicate securely, easily, in groups or one to one, and affordable, by any mode they choose. Visit Buzz or contact them to learn more about Buzz by Skyscape today.

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Gaslighting Patients and Caregivers

Admin

by Elizabeth E. Hogue, Esq.

Gaslighting

Gaslighting, According to:

Nurse Professional Liability Exposure Claim Report: 4th Edition issued by Nurses Service Organization and CNA, for the period from 2016 to 2019 nurses who prvided services to patients in their homes; including those providing home health and hospice, and palliative care; were the most vulnerable of all nursing specialities to professional liability claims.

A Dubious Distinction

This is the first time that nurses in home care topped the list since the reports were first compiled in 2008. Home care nurses accounted for 20.7% of claims, which represents an increase of 12.4% over the previous number reported in 2015. Adult medical/surgical nurses topped the list in past reports.

Tell me Why

These factors may contribute to increases in claims against home care nurses:

  • Lack of institutional support for home care nurses that is routinely received by nurses in hospitals and other facilities
  • Growing popularity of home care
  • Rising acuity of home care patients
  • Lack of 24-hour oversight of patients
  • Absence of equipment in patients’ homes that is readily available in institutional settings to help identify patients at high risk for negative outcomes

According to the Experts

However, the nonprofit organization Emergency Care Research Institute (ECRI) says that eroding trust is a major threat to patient safety in 2025. ECRI ranks “gaslighting,” or dismissing concerns of patients and caregivers, as the top issue. In other words, nurses aren’t listening to patients and their caregivers! There is an old adage that says that if practitioners would just listen to their patients, patients will tell them what is wrong (i.e., the diagnosis). Perhaps, then, the best way to avoid negligence and resulting lawsuits is to listen to patients and caregivers.

Gaslighting Safeguards

Other strategies that nurses can use to protect themselves from malpractice claims include:

  • Stay up to date on education and training
  • Document assessments of patients in a timely and objective manner
  • Go up the chain of command when concerned about the well-being of patients
  • Maintain files that demonstrate character; such as letters of recommendation, notes from patients, and performance evaluations

Of course, complete, accurate and contemporaneous documentation may provide the best defense of all!

Final Thoughts

An increase in malpractice claims against home health and hospice nurses is a significant new industry development. It’s time to move risk management, with a focus on listening to patients and caregivers, higher up the list!

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Enabling Care Through AI

Admin

by John Crighton, CTO at Curantis Solutions

Enabling Care Through AI: Ethical Issues

Recently, artificial intelligence (AI) has become an essential component of healthcare organizations. AI is revolutionizing hospice and palliative care by enhancing patient care and optimizing workflows. Its impact is undeniable in these sensitive and life-changing fields. At Curantis Solutions, we are proud to apply AI-driven solutions to support caregivers while upholding ethical standards, enabling care through AI.

The Importance of AI in Hospice and Palliative Care

Hospice and palliative care are primarily based on empathy, understanding, and individual approach. When applied correctly, AI can enhance these core principles in several ways:

  • Improving Efficiency
    • Some of the time-consuming tasks, such as entering assessment notes, reviewing recent documents before a patient meeting, or creating a summary of recent documentation in preparation for a team meeting, can be performed or assisted by AI. By automating these administrative tasks, caregivers can spend more time providing direct patient care.
  • Predictive Analysis
    • AI tools can analyze the patient’s data and predict the possible changes in the patient’s condition, which will help to prevent complications.
  • Individualized Care Plans
    • Based on the patient’s history, AI can help clinicians in the development of care plans that are more accurate in meeting the needs of the patient. Although the idea of using AI in hospice and palliative care is fascinating, it is crucial to approach this issue with caution and always pay attention to ethical issues.

Ethical Issues in the Use of AI in Hospice and Palliative Care

As  the industry incorporates AI into our products and agencies, we need to consider ethical implications such as those shown below:

  • Privacy and Data Protection Issues
    • Hospice and palliative care deal with the patient’s private details. At Curantis Solutions, we ensure that all AI-powered tools comply with the highest security and privacy standards, safeguarding patient data at every step.
  • Bias and Fairness
    • The way AI systems are developed, they are only as good as the data that is used in their development. At Curantis Solutions, we strive to recognize and eliminate any possible prejudice in the AI systems that we develop to benefit all patients.
  • Transparency and Accountability
    • It is important that the caregivers and the patients know how the AI is being used and how the decisions are made. We try to make our AI solutions as transparent as possible, and we ensure that the final decisions are always made by humans. Hospice and palliative care are very personal. This field is defined by the human component, and AI should only supplement it and not replace it. The solutions that we provide are intended to assist clinicians in order to maintain the sanctity of every patient.

A Future of Kindness with the Help of AI

The healthcare sector is changing rapidly, and AI is coming in to improve hospice and palliative care. At Curantis Solutions, we are proud to apply AI in a way that enhances the human factor, ethical values, and the capacity of the caregivers to offer the best care possible to the patient. Therefore, it is possible to envision a future where technology and empathy coexist to ensure that every patient gets the care they require. Leverage AI to reduce administrative burdens for hospice and palliative care.

About Curantis Solutions and AI

The goal of Curantis Solutions is to assist hospice and palliative care providers in the provision of patient-centered and compassionate care. This post discusses how AI can be used in this mission and how it can be done ethically.

We accomplish this in the following manner:

  • Working in partnership with specialists
    • We partner with clinicians, ethicists, and AI experts to guarantee that our solutions are appropriate for the context of hospice and palliative care).
  • Revisiting the Model
    • AI is not set and forgotten; it needs to be assessed and improved on an ongoing basis. We also regularly check the efficacy of our AI tools to ensure that they are accurate, fair, and reliable.
  • Enabling Care Teams
    • Our solutions which are supported by AI are meant to support the skills of the care teams and not to replace them. Thus, we lessen the burden of documentation to allow the providers to focus on the patient and their families more often.

# # #

Curantis Solutions AI John Crighton

John Crighton is a seasoned technology leader, with over 25 years of experience in software development innovation and best practices.

John most recently served as the Chief Technology Officer for Lightning Step, a Behavioral Health SaaS EHR with over 100,000 users. John served on the executive team that scaled the business, contributing to the 40x revenue growth and eventually to a successful exit.  Prior to that, John managed a custom development team at Openlink Financial and was responsible for product quality at SolArc Software. John was part of the management team that led Mission Critical Software to a successful IPO and went on to management roles with JMI Software, NEON Systems, and NetIQ.

John is a veteran of the US Army, and graduated Summa Cum Laude from the University of Houston with a Bachelor’s of Business Administration.

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in the Curantis Solutions blog and is reprinted in Healthcare at Home: The Rowan Report with permission. For further permission to reprint, contact Curantis Solutions.

More Violence in Care at Home

Admin

by Elizabeth E. Hogue, Esq.

Violence Against Home Care Providers Continues

Violence in Care at Home Continues…

Sadly, but not surprisingly, the violence against field staff caring for patients in their homes continues. Here’s a recent example:

On February 28, 2025, a hospice nurse in Texas was accosted inside a patient’s home while she was attempting to provide care. The man who accosted her inside the home followed her outside with a rifle and fired at her as she fled. The nurse was uninjured, but her car was struck by at least one bullet.

Then, still armed, the man went back inside the patient’s home where he stayed close to the patient while pointing his rifle at deputies. Law enforcement officers were able to communicate with him and de-escalate the tense situation. The man was booked into the county jail on a charge of aggravated assault with a deadly weapon and bond was set at $250,000.

Violence in Care at Home

By the Numbers

According to a recent analysis of Bureau of Labor Statistics data, healthcare is one of the most dangerous places to work. Homecare field staff members who provide services on behalf of private duty agencies, hospices, Medicare-certified home health agencies, and home medical equipment (HME) companies may be especially vulnerable. Contributing to their vulnerability is the fact that they work alone on territory that may be unfamiliar and over which they have little control. Staff members certainly need as much protection as possible. 

Violence Policies Needed

First, regardless of practice setting, management should develop a written policy of zero tolerance for all incidents of violence, regardless of source. This policy should include animals. The policy must require employees and contractors to report and document all incidents of threatened or actual violence, no matter how minor.

Beyond Reporting

Emphasis should be placed on both reporting and documenting. Employees must provide as much detail as possible. The policy should also include zero tolerance for visible weapons. Caregivers must be required to report the presence of visible weapons.

UCHealth SAFE Program

Below are some additional important actions for healthcare organizations to take that are based on the UCHealth SAFE Program:

  • Encourage staff members to STOP if they feel unsafe for any reason. 
  • If danger is not imminent, workers should pause to generally ASSESS their environments. Staff members should think about what happened and observe what is currently happening. Is there, for example, mounting frustration or anger?
  • Staff should then FAMILIARIZE themselves with the area. Who is the patient? Where is the patient? Are there any factors that might escalate behaviors? Staff members should also consider putting themselves in positions where they have a route to escape, if necessary.
  • ENLIST help. Getting help may, for example, include pushing panic buttons on mobile devices.

In Their Own Words

Here is what Chris Powell, Chief of Security at UCHealth, said in Becker’s Hospital Review on June 4, 2024:

“You can’t just talk about the shrimp and give you a good picture. We have to talk about the roux and the rice and everything else that goes into this for a good picture to be painted so people have an understanding. We want to solve this with an electronic learning or a 15-minute huddle, but we can’t. This is continuous and a persistent pursuit toward educating, communicating, recognizing, responding to, reporting and recovering from workplace violence.”

Chris Powell

Chief of Security, UCHealth

Final Thoughts

Every caregiver matters. The healthcare industry has lost caregivers to violence on the job in the past. Let’s do all that we can to avoid similar events in the future.

# # #

Elizabeth E. Hogue, Esq.

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2025 Elizabeth E. Hogue, Esq. All rights reserved.

No portion of this material may be reproduced in any form without the advance written permission of the author.

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com