Product Review: Startup Reimagines the EMR

by Tim Rowan, Editor Emeritus

Catherine Zhang was thriving in product engineering while Mayur Pandya held a similar leadership role for Silicon Valley’s Workday. Their futures were predictable and bright until Catherine’s close friend unexpectedly passed away, changing her career goals as profoundly as her heart.

Over a cup of coffee, Zhang and Pandya learned they both had close family working in health care. The conversation turned to how they might apply their product development expertise to, as they put it today, “improve patient outcomes, empower care teams, and reduce the cost of care in the U.S.”

Their first task was to identify which healthcare sector had a pain point that needed their talents most. Naturally, they found their way to the $129 billion Home Health sector. Ms. Zhang told us they were taken aback by the severity of the harm done to Home Health by Medicare Advantage plans.

Catherine Zhang Narrable

“We learned that over 600 HHAs had closed their doors in the previous five years. MA reimbursement ranges from 60% to 70% of what Medicare pays, and the administrative burden imposed by MA plans is seven to eight times what it is for traditional Medicare. Making matters worse, or perhaps because of these pressures, we found the turnover rate among HHA nurses to be 31%.”

Mayur Pandya Narrable

Fast Forward Two Years

Working together, the pair attracted investors, additional coders, and, most importantly, experienced Home Health advisors and product designers. What began as an idea to ease the workload on the nurse in the field grew into a full-fledged electronic medical record system, complete with AI-enabled intake, scheduling, revenue management, physician signatures, and quality control. Naturally, created in the 2020’s, the new system is built around Artificial Intelligence tools. They dubbed it “Narrable.”

“What we wanted to do,” Ms. Zhang continued, “was to harness the power of AI to eliminate the inefficiencies we were learning from owners and nurses within HHAs. Some spend hours completing assessments and visit notes in the evening because ‘it is too hard to document in the patient’s home.’ Many told us that intake, scheduling, chasing physician signatures, and productivity tracking are too unpredictable or too complex for their existing EMR and they resort to multiple spreadsheets.” One HHA owner told Zhang that he “spent $500,000 last year on double data entry.”

Narrable Features We Saw

Narrable’s roots are in the field nurse’s experience. Ms. Zhang explained that the system’s clinician-centric design can eliminate tens of thousands of “invisible” clinician work. In the product demonstration she walked us through, we were able to understand how an AI engine might save work by eliminating both steps and errors.

    • Scheduler analyzes each clinician’s capacity, ability to accept an additional patient, and geographic location, automatically recommending the best person to take a new case. Still, a human makes the final decision.
    • OASIS assessment answers are automatically checked against referral documents and internal logic quality checks are performd.
    • Clinical notes benefit from AI pre-filling demographic data, reminding the clinician of OASIS determinations and goals stated on the Plan of Care.
    • Eligibility is checked against payer data and prior Home Health admissions
    • Physician PECOS integration auto-fills fields, eliminating repetitive data entry
    • Claims management includes:
      • alerts to find uncompleted tasks that may delay billing
      • automated claims submission
      • automatic monitored and posted remittances

Lastly, Narrable offers a suite of configurable management reports that check for maximum allowable PDGM revenue, HHVBP outcomes that may affect adjustments, and real-time financials. A configurable financial report displays paid vs expected revenue, A/R, adjustments, and denials.

Our Narrable Recommendation

At last month’s inaugural conference of the new National Alliance for Care at Home, we witnessed a virtual AI explosion. Every established tech company and a plethora of startups are diligently experimenting to identify the appropriate role for artificial intelligence in Home Health and Hospice. As with all breakthrough technologies, there will be a race to the finish line, with the large, established companies enjoying a head start and others scrappily inventing and innovating with no legacy products acting as a ball and chain.

In this writer’s opinion, Zhang and Pandya have come up with something different. Any HHA thinking about launching an EMR search and evaluation project would not regret the time invested in giving Narrable a look.

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com


Here We Go Again

by Tim Rowan, Editor Emeritus

OIG Accuses Medicare Advantage Providers of Padding Patient Assessments...Again

“Hello, this is your Medicare Advantage company calling. I am one of their clinicians and it is time for us to update your health assessment. If you will agree to a home visit, we will send you a $50 gift card to CVS.”

This phone call my brother received is typical, increasingly common, and not necessarily on the up-and-up, according to a new report to CMS from the Department of Health and Human Services Office of the Inspector General (OIG). OIG found that these home visits, known in the insurance industry as “Health Risk Assessments,” (HRA) when coupled with HRA-related claims data, increased Medicare Trust Fund payments to MA companies $7.5 billion in 2022 and twice that in 2023. Most of it went to the top 20 companies.

Concerned woman on a telephone call

The October 2024 report, “Medicare Advantage: Questionable Use of Health Risk Assessments Continues to Drive Up Payments to Plans by Billions,” accuses the industry as a whole of improperly padding payments by “finding” new health conditions during these HRA’s that may indicate the need for additional care at additional cost to the company. It questions the use of MA plan employees doing these assessments instead of relying on the customer’s primary care physician’s reports.

OIG references CMS’s own report, “Part C Improper Payment Measure (Part C IPM) Fiscal Year 2023 (FY 2023) Payment Error Rate Results,” to determine that gross overpayments to Medicare Part C plans in 2023 amounted to just over six percent of total payments, or $14.6 billion. The net increase to MA plans, after adjusting for underpayments, brought the percentage to 4.62. Total 2023 payments to MA plans came to $275,605,962,817.

The report also points out that identifying additional customer need during an HRA does not necessarily translate into the insurance company paying for additional care.

OIG Recommendations

In addition to implementing prior OIG recommendations, the new report asks CMS to:

    • Impose additional restrictions on the use of diagnoses reported only on in-home HRAs or chart reviews that are linked to in-home HRAs for risk-adjusted payments,
    • Conduct audits to validate diagnoses reported only on in-home HRAs and HRA-linked chart reviews, and
    • Determine whether select health conditions that drove payments from in-home HRAs and HRA-linked chart reviews may be more susceptible to misuse among MA companies.

CMS concurred with OIG’s third recommendation but rejected the other two.

While the entire 38-page report is well-worth reading, OIG has also published a one-page summary.

At this year’s annual conference of The National Alliance for Care at Home, the new merger of NAHC and NHPCO, a number of education sessions were devoted to teaching Home Health agency owners how to negotiate with Medicare Advantage plans in order to minimize losses and better care for patients who chose those plans. Comments included the high rate of care denial, unreasonable prior authorization policies, and slow payments as compared to traditional Medicare. Other healthcare entities have chosen a potentially more effective response: Just Say No. 

Hospital systems have had enough

According to a roundup of recent decisions by large and small healthcare systems in Becker’s Hospital CFO Report (10/25/24), no fewer than 30 healthcare providers are severing their relationships with one or more MA plans, with another 60 who told Beckers they are seriously considering the same move.

Doctor tears up contract

States Have as Well

A sister publication, Becker’s Payer Issues, reported in its October 23 edition that more and more states are issuing fines against MA plans for violations ranging from excessive denied claims to collection of co-pays when none was required.

How Much Longer?

All of this demands a serious question. How much longer will Home Health continue to tolerate abuse by these giant, for-profit payers now that a different path forward has been paved by hospital systems and state regulatory arms? The loudest voice for Home Health to join the “Just Say No” movement over the last few years has been that of Bruce Greenstein, CTO of LHC Group. Following his company’s acquisition by UnitedHealth’s Medicare Advantage division, Optum, his less loud message is to work with MA plans to teach them what Home Health is and what it can do for them.

Statement from Dr. Landers

In his inaugural address to The Alliance last month, new CEO Dr. Steven Landers called for our entire industry and everyone taking a paycheck from it to join him in advocacy. We fully support that call to action, recognizing that no national association can influence lawmakers and CMS regulators without member support, but he was referring to Medicare rules and payment structures. As we know, that includes less than half of Medicare beneficiaries today. Thanks to deceptive TV ads during open enrollment every year, that number will continue to shrink.

Widespread Advocacy

We need to turn at least part of our advocacy focus to the dominant payers, the MA divisions of insurance companies. Read the Beckers report on the 30 healthcare systems that have torn up their MA contracts. Read the companion report about the epidemic of care denials. Yes, it is a David vs. Goliath story, with even the largest organizations in Home Health dwarfed by the size of the payers. As so many hospital systems have shown, however, it is possible to switch from begging for a few more cents per visit to forcing a plan to beg you to take their patients.

It will only work though if everyone does it. We have already lost LHC Group, and Optum is in the final stages of adding Amedisys to their stable. Out of 11,000 HHAs, there is still a chance we have a united voice loud enough to be heard and taken seriously.

Final Thoughts

One of their improper cost-cutting tactics is routine care denial. For example, the Labor Department alleged that UnitedHealth subsidiary UMR denied all urine drug screen claims from August 2015 to August 2018 without determining whether a claim was medically necessary. In my brother’s case, following his wife’s HRA by her MA company, with no additional care offered, he made the tough choice to put her on in-home hospice care. The assessing nurse immediately detected she had a UTI and ordered the appropriate antibiotics. She responded quickly and may be discharged from hospice soon. Hospice care, of course, is paid by traditional Medicare, not Medicare Advantage.

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com or contact Tim at Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

The Great Hospital/Home Health Divorce Movement

by Tim Rowan, Editor Emeritus

Hospitals Divesting Home Health Departments

Is this an early omen of two related trends? A number of hospitals are divesting their home health departments, while large health insurance companies are swallowing up large home health companies.

Beckers reported on October 23 that Providence Health plans to spin off its home-health services along with hospice and palliative care into a new joint venture that will be managed by Compassus, a for-profit, Tennessee-based provider of home care services in 30 states. The move will affect about 700 patients receiving care every day in Spokane County.

The Catholic not-for-profit health system’s agreement with Compassus will be known as “Providence at Home with Compassus.”

After a regulatory review, the deal is expected to close in early 2025. Providence and Compassus will each own a 50% stake. The new venture is part of a strategy to expand and improve home-based services, but also to cut costs. Providence, which operates Sacred Heart Medical Center and Holy Family Hospital in Spokane, declined to disclose the financial details of the joint venture.

LHC Group Was Not Enough

A news release that surfaced on October 25 said that UnitedHealth Group representatives are set to meet with Justice Department officials to make the case for the insurance giant’s acquisition of Amedisys to be approved. The meeting is often the last step before the Justice Department decides whether to file a lawsuit challenging an acquisition, according to the news outlet. 

Amedisys operates more than 500 facilities in 37 states. Shareholders approved the acquisition in September 2023, but the deal has been held up by regulatory scrutiny. Justice Department officials are concerned the deal could increase prices for home health, according to Bloomberg. 

Hospitals Divesting Home Health

If approved, this would be phase two of UnitedHealth’s historic foray into our sector. United acquired LHC Group, a home health provider with more than 900 locations, in February 2023. If UnitedHealth’s acquisition of Amedisys is approved, the company would own 10% of the entire home health market, with significant overlap between Amedisys and LHC acquisitions in some Southern states, according to Bloomberg. 

Regulators could approve the deal with some changes to address competition concerns, Bloomberg reported. In August, Amedisys and UnitedHealth agreed to sell a reported 100 home health and hospice care centers to VitalCaring Group if the merger is approved.

Three or More is a Trend

UnitedHealth is not the only insurance company interested in owning home health agencies and hospices:

  1. Humana acquired Kindred, one of the nation’s largest HHAs, and rebranded it CenterWell Home Health. Today it operates more than 360 home health locations in 38 states. In 2023, the company said it would expand into in-home primary care in several states.
  2. In 2023, CVS Health acquired home health provider Signify Health for $8 billion. The company won a bidding war for Signify over UnitedHealth Group, Amazon and Option Care Health. Signify Health has more than 10,000 clinicians.
  3. Evernorth, Cigna’s health services arm, offers home health services with a staff of more than 430. In January, Cigna CEO David Cordani said home health was one area where it would focus on future acquisitions.
  4. In 2021, Centene sold its majority stake in home-based primary care provider U.S. Medical Management. Centene retained a minority stake in the company.

Our healthcare sector is changing as the entire U.S. healthcare scene changes. Next week we will delve further into the ramifications of the CMS 2025 final rule and of course the political events of this week.

# # #

Tim Rowan, Editor Emeritus
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

UnitedHealth Study: Is Medicare Advantage Killing Seniors

by Tim Rowan, Editor Emeritus

Is Medicare Advantage Killing Us?

Dr. Steve Landers has long been eloquent in his speaking and writing about the importance of Home Health over the years. Though I was already impressed, I gained a new level of respect this week. Simultaneously with his debut as CEO of the new Alliance, Dr. Landers released an article about a recent study on the impact of Medicare Advantage on Medicare beneficiaries.

It is an article that everyone in our healthcare sector should read.

In “Home Health Cuts and Barriers are Life and Death Issues for Medicare Beneficiaries,” Dr. Landers points readers toward a study conducted by Dr. Elan Gada of UnitedHealthcare’s Optum Group. The results are disturbing. That the findings were released by a Medicare Advantage company is surprising.

Yes, Virginia, Home Healthcare Really Does Save Lives

Landers cited the study’s primary finding. “Medicare Advantage beneficiaries in their plan who did not receive needed home health care after hospitalization were 42% more likely to die in the 30 days following a hospital stay than those who received the prescribed care.” If a drug proved to be as effective as post-discharge home healthcare in saving lives, Landers wrote, “it would dominate the news, restricting access would be considered immoral, and health officials would be pushing its adoption.”

Medicare Advantage Enrollees Go Without

There are a number of reasons a hospital discharged patient might not receive home healthcare, including system issues and patient refusal. However, Dr. Gada’s study also discovered that MA customers go without post-discharge home health at a higher rate than traditional Medicare beneficiaries. Traditional Medicare beneficiaries go without in-home care about 25% of the time. Medicare Advantage beneficiaries 38% of the time. Landers notes that this data is a few years old and that the denial rate for MA customers is likely higher today.

Stop the Killing

We know the life-saving impact of post-hospital home healthcare. The question becomes: how does our little corner of the U.S. healthcare system help regulators and payers to know it as well as we do? At this week’s inaugural conference of the National Alliance for Care at Home, at least three education sessions discussed Medicare Advantage. All three offered strategies for negotiating with insurance companies and surviving under their oppressive rate structures and their frequent care denials.

UnitedHealth Group Medicare Advantage Landers

These Are Bandages, Not Cures

In previous opinion pieces, I have quoted revelations in government lawsuits against MA divisions of insurance companies. These prove the program that was originally launched to extend the lifespan of the Medicare Trust Fund actually costs CMS 118 percent of what traditional Medicare costs. At the same time, insurance company reports to shareholders proudly point out that their MA division is their most profitable.

One of last week’s most read stories was the report from UnitedHealth Group on their astounding Q3 growth.

In the Long Run

Learning to cope with MA care denials and below-cost visit payments is fine for those focused on making next month’s payroll. An entirely different tactic is needed for those focused on the care needs of their elderly parents or who are approaching age 65 themselves. The question must be asked, “Why does Medicare Advantage exist?”

Medicare Advantage Lobbyists

AHIP is the insurance company lobby. It put extreme pressure on Congress in 2009 when the Affordable Care Act was being written. That pressure resulted in then-President Obama removing a core plank from his bill. Obama struck the public option healthcare insurance plan in order to win enough votes to get the bill to his desk.

More $ Makes More $

That lobbying effort continues today precisely because MA is so profitable. How does it bring in so much cash? One after another, all of the large insurance companies have been caught padding patient assessments, the very fraud Home Health is so often accused of. Their monthly checks are determined by how much care they predict their covered lives will need, and they exaggerate it. Later, when it comes time to treat these same customers, MA plans deny care that would have been covered by traditional Medicare. They book profits at both ends, and they gladly pay the minimal fines when the practice is exposed.

The Reality of Medicare Advantage Fraud

To make each covered life more profitable, MA plans have begun calling customers to offer “free” nurse visits. These are essentially re-assessments where the MA staffer is rewarded for “finding” additional illnesses. This is not theoretical. My brother was offered a $50 gift certificate to CVS if he would allow his wife’s MA plan representative to drop in and chat with her, to “make sure she was getting all the benefits she was entitled to.”

Dr. Steven Landers: Call for Advocacy

In his article and in his speeches this week, Dr. Landers made it quite clear what must be done. EVERY person whose livelihood depends on the Medicare Trust Fund must make their voice heard. Letters and phone calls to Congress, to the Senate, to CMS, and to the Secretary of Health and Human Services, telling them you do not want to happen to your community what happened in Maine. After years of negative profit margins, in a state where MA adoption is at two-thirds, Andwell Health Partners ceased business in a wide swath of the northern regions of the state. Andwell was the only Home Health provider there.

The combined advocacy strength of NAHC and NHPCO is not enough to tip the scales. Your input is crucial.

Here's How it Works:

  1. Your letter explaining the damage coming from shrinking CMS reimbursement and MA care denials will be opened by a Congressional staffer.
  2. The staffer will read only enough of your letter to see its topic and which side of that topic you are on.
  3. No need to be lengthy or eloquent
  4. Put your topic and your position in your first paragraph
  5. The staffer will add a checkmark in the pro or con side of their Home Health ledger.
  6. The Congressperson, Senator, HHS Secretary will see a one-page summary of the numbers.
  7. When the numbers are small, the summary goes into a file
  8. When the numbers are large, the elected or appointed official will pay attention
  9. In rare cases, you may even get a phone call
UnitedHealth Group Advocacy Medicare Advantage

Dr. Landers, in His Own Words

The article Dr. Landers wrote detailing all of these includes wording suggestions for your message in your letter and/or call. For convenience, I have included one paragraph below,* but I urge you to spend three minutes reading the entire inspiring and frightening piece. In person, he explained all this in an emotional appeal. He said he cannot emphasize enough the importance of universal participation in our new organization’s advocacy effort. Based on what we have learned about post-hospital nursing care in the home, your letters and phone calls are a matter of life and death.

Excerpt

*To save lives and avoid unnecessary suffering, Medicare officials must reverse their plans to cut Traditional Medicare home health payments for 2025 and ensure payments are stable after adjusting for the dramatically increased healthcare labor cost inflation experienced over the past 5 years. Additionally, Medicare officials and lawmakers must study and address the possibility of the disproportionate administrative and financial barriers to home health in Medicare Advantage.

We are fortunate to have leaders in Congress like Senator Debbie Stabenow, Senator Susan Collins, Representative Terri Sewell, and Representative Adrian Smith who are working to champion a comprehensive bi-partisan legislative fix. Our leaders in Washington must act swiftly, before the end of the year, to save lives and avoid further destabilizing home health services for Medicare beneficiaries.

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

An Interview with Dr. Steven Landers, Part 2

by Kristin Rowan, Editor

Medicare Advantage is Killing Us...Literally

This is part 2 of 2 in the interview with Dr. Steven Landers. You can read part 1 here.

Medicare Advantage article by Dr. Landers

Earlier this week, Dr. Landers published an article in the NAHC Report. The article cited three studies and analyses on the number of enrollees in both Medicare and Medicare Advantage who do not receive the care to which they are entitled. During our recent interview with Dr. Landers, he addressed this article.

Dr. Steven Landers: On the Record

The Rowan Report:

You wanted to address something you recently wrote. Is this the same topic you mentioned the opening session, or is this something else?

Dr. Steven Landers:

No, this is a focused piece on the emerging research that we’re seeing around when people miss out on home health. It’s a life and death issue. I want to be sure that we, as an alliance, I, as a physician, and us, as advocates, that we are conveying that these issues around home health cuts and barriers are potentially deadly. This is not a trivial matter. It’s not an administrative or technical financial issue. It’s about people’s lives.

RR:

The article mentioned a study that said that the numper of people not getting the home care that they’re entitled to is almost double with Medicare Advantage enrollees over traditional Medicare.

Steve:

That was from a study that’s referenced there from a few years ago. The Partnership for Quality Home Health Arcadia Analysis that came out this year actually showed that those trends are worsening. We know that they’re not getting the needed care in Medicare Advantage and traditional Medicare.

In both cases it’s too high, but it’s higher in Medicare Advantage. It’s more common that people don’t get the prescribed care in Medicare Advantage. And we also know that that’s going up in both traditional Medicare and Medicare Advantage. The access has gotten worse because of the Medicare home health policy and because of the way that Medicare Advantage has grown and handled these issues.

Medicare Advantage Landers
Interviewer:

I guess the big giant question is what do we do, especially when margins for both traditional Medicare and Medicare Advantage are so low?

Steve:

One, we’ve got to start improving access to home healthcare. And the way that we do that is we end this march of payment cuts that are being set forward by Medicare. I mean, right now the leaders of Medicare are in their rulemaking process and they have choices to make. They can either do things that reverse this trend and put us on a path to better access or I think continuing these cuts will hurt beneficiaries.

And the other piece is the Medicare advantage front. We need more scrutiny and evaluation and potentially oversight here to make sure Medicare Advantage beneficiaries have access to high quality home healthcare.

“The results of this study demonstrate that among MA members referred to home health after acute hospitalization, those who did not receive home health services experienced higher mortality and lower readmissions than those who received these services.”

Unfulfilled Home Health Referrals Lead to Higher Mortality Among Medicare Advantage Members

Elan Gada, MD, Paul Pangburn, MHA, Chris Sahr, MS, MBA, Chad P. Schaben, MPH, Richard Young, MS

RR:

Where does the problem lie?

Steve:

People don’t get home health when it’s prescribed and mortality rates are substantially higher. There could be [anecdotal] reasons that this is happening. I’ve tried to think of them. I can’t really come up with them when you see it in three different analyses, especially one done within the Medicare Advantage plan. They have great data. It was well thought out and this is serious business and it really should be a kitchen table discussion for families like ‘what’s going here?,’ because obviously home healthcare is a beloved service that families care deeply about.

We’ve seen home care become a presidential campaign issue because it’s good policy and also because the folks running, Vice President Harris, who brought it up, and former President Trump, who chimed in sort of a me too, being enthusiastic about the concept. They’ve got to know that this polls well, that the families care about this stuff.

Editor Emeritus Tim Rowan provides an analysis of the study from UnitedHealth Group here.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Introducing “The National Alliance for Care at Home”

by Tim Rowan, Editor Emeritus

National Alliance for Care at Home

The merger of the National Association for Home Care and Hospice and the National Hospice and Palliative Care Organization, which was inked on July 1, became official this week in Tampa, Florida. The new National Alliance for Care at Home said farewell to retiring NAHC President Bill Dombi and gave a rousing welcome to incoming Alliance CEO, Steven Landers, MD. Both Bill’s farewell address and Dr. Landers’ introduction speech ended with the same theme. We do what we do for the good of our patients. Yes, there is money. Yes, there are politics. In the end, our legacy and our future are about people.

Dr. Steven Landers

Integrity, Quality and Compliance

That future will begin with a commitment to patient care excellence. Dr. Landers closed his opening address with an announcement. From now on, every member, upon beginning or renewing their annual membership, will be asked to sign an attestation pledging their company and themselves personally to commit to Integrity, Quality, and Compliance. “Our members will be known to the world as the best in the industry,” he proclaimed. “They will assure patients, families, and payers that they participate in Medicare and Medicaid quality performance standards.”

In a press conference the next day, Dr. Landers elaborated that NAHC and NHPCO have always worked with public and private payers and law enforcement agencies to rid our industry of those who are not in it for noble reasons. Those cooperative efforts will continue, he told the reporters. The new attestation will further assure the world that members of The Alliance publicly join that mission. One is reminded of a code of conduct common to all our national military academies. “We will not lie, steal, or cheat, nor tolerate among us anyone who does.”

Emphasis on Advocacy

The Alliance is new, and Dr. Landers candidly admits he is gradually learning his new role as he goes along. But he is guided by a commitment to care in the home that has been with him since medical school. “I didn’t want to be just another cog in the system,” he told 2,000+ attendees. “The first time I went along on a home visit, I immediately realized that this is what I wanted to commit my career to.” Through his years at the VNA and Cleveland Clinic, he saw the power of in-home care, including its ability to extend live expectancy and reduce the total cost of care.

Bill Dombi

A Semi-Farewell at Best

National Alliance for Care at Home Dombi

Bill Dombi will serve the new Alliance through the end of this year before fully entering retirement. Following his closing address on the last day of the conference, during which he summarized his 38 years with NAHC (years that began with a promise to his wife Lynn that they would only have to leave their home in Connecticut for the DC area for three to four years), I asked him what he planned to do that first day in January. He said that he accumulated a ton of frequent flyer miles during his career and that they would love to travel somewhere other than state and national association conference cities.

He also mentioned the ongoing legal actions he initiated to force CMS to develop more honest formulae for calculating Home Health reimbursement and added, “It is very difficult to change litigators in the middle of a lawsuit.” Draw your own conclusion but take it from one who knows how difficult it is to completely walk away from this mission and its people. We may not have heard the last of William A. Dombi.

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

More Rural Providers Say ‘No’ to MA

by Tim Rowan, Editor Emeritus

O

ne just does not know whom to believe anymore. This week, we were sent three opinions of the pros and cons of Medicare Advantage programs. One says they reduce costs and improve patient satisfaction for rural residents. Another says rural hospitals are turning away MA customers at a growing rate. The third says MA customers utilize healthcare services at a lower rate than traditional Medicare beneficiaries. Let’s take a look at each opinion.

The Pro

Better Medicare Alliance is a non-profit advocacy group that promotes Medicare Advantage. They describe themselves and the genesis of their recent report this way:

“Better Medicare Alliance engaged ATI Advisory to understand Medicare beneficiaries who live in rural areas and how they are served across Medicare Advantage and Fee-for-Service (FFS) Medicare. Understanding geographic differences in beneficiary experiences is important to both the Medicare Advantage and FFS Medicare program. This research can help policymakers and stakeholders identify opportunities to improve access to and quality of rural health care.”

That sounds good so far. Let’s look at their conclusions.

    • 30 percent fewer MA client live in rural areas compared to cities and suburbs
    • rural MA enrollees are more likely to be Black or LatinX but health needs are consistent across all rural demographics
    • satisfaction is the same between rural MA clients and traditional Medicare beneficiaries, though MA enrollees use preventive services more and outpatient services less
    • rural MA enrollees spend less in premiums and out of pocket costs than traditional Medicare beneficiaries

Rural Hospitals Tell a Different Story

Healthcare Uncovered, an online publication with a patient advocacy slant, describes BMA as “an active front group for the health insurance industry and perhaps the country’s greatest champion of Medicare Advantage plans.” and “with a well-stocked, industry-financed war chest to promote insurers’ premier product.”

Writing for Healthcare Uncovered, longtime healthcare journalist Trudy Lieberman added perspective to the BMA-sponsored report:

More places say no to medicare advantage

There was evidence last fall that Medicare Advantage was under attack when several hospitals announced they were reviewing their arrangements with Advantage plan sellers and were not accepting some or all plans. The CEO of the Brookings Hospital system in Brookings, South Dakota, told me, “The difference between original Medicare and Medicare Advantage is vast. Advantage plans pay less, don’t follow medical policy, coverage, billing, and payment rules and procedures, and they are always trying to figure out how to deny payment for services.”

In 2023, Becker’s Hospital Review began reporting on hospitals that were dropping some or all of their contracts with Advantage plans. The August 20, 2024 update indicates 18 more hospitals have or will drop MA plans this year. 

Ms. Lieberman went on to report that MA plans frequently limit in-plan physicians. When they eliminate a physician in a rural community, patients often must travel miles to reach an approved doctor.

“Another damning report, this one issued by the Nebraska Rural Health Association, also revealed the pitfalls of joining an Advantage plan. The report warned that Nebraskans with Advantage plans ‘have created such a financial burden for rural residents’ that when they get sick, those with Medicare Advantage coverage ‘represent the largest growing segment of charity care for Nebraska’s rural hospitals.’ I’d bet few if any seniors are told they may end up on charity care if they choose an Advantage plan.”

A hospital in 23,000-resident North Platte, Nebraska has stopped accepting all MA patients. CEO Ivan Mitchell told Ms. Lieberman that transfers to nursing home and Home Health are denied 13 percent of the time. “Hospital stays are 40 percent longer for MA patients. They are stuck in the hospital two or three days waiting for approval to be transferred, and we need those beds for sicker patients.”

RIHC logo

Home Health Weighs In

The Research Institute for Home Care awarded a grant to Tami M. Videon, PhD, and Robert J. Rosati, PhD, of the VNA Health Group, the honored Home Health not-for-profit in New Jersey. The researchers divided beneficiaries into three groups: Traditional Medicare, MA with a premium, and MA without a premium. Their findings resonated with the experiences of rural hospitals more than those of the MA advocacy group.

Research Findings

    • Traditional Medicare (TM) beneficiaries were more likely to utilize outpatient, inpatient, and home health care services than beneficiaries in Medicare Advantage (MA) plans, regardless of whether the plan had a monthly premium or not.
    • Beneficiaries who reported being in zero premium MA plans were substantially less likely to use dental, hearing, and vision services compared to other beneficiaries.
    • Rates of utilization of hearing and dental services were relatively similar for beneficiaries reporting they were in MA plans with a premium and those enrolled in TM. Access to vision services was greatest among beneficiaries reporting being in MA plans with a premium.

In their research briefing, the researchers stated:

“Consistent with the literature, this study found beneficiaries enrolled in MA  plans had lower utilization for services required to be covered by Medicare (outpatient visits, inpatient admission, and home health care use) than beneficiaries enrolled in TM. The observed lower rate of home health care utilization among MA beneficiaries may result from restrictions in inpatient care. However, prior research indicates when analyses are restricted to similar patient populations (a subset of diagnostic codes), MA beneficiaries are less likely to receive home health care than TM beneficiaries.”

Where Does the Money Go?

We have often reported on the lawsuits that various federal departments have lodged against the largest health insurance companies for their Medicare Advantage practices.  With their payments from the Medicare Trust Fund based on patient assessments, they have been caught exaggerating illnesses, adding chronic conditions that do not exist, and conducting periodic home visits to “update” their data on the health condition of their customers. These nurse visits to the home frequently “identify” serious health conditions that the person did not know they had, or in most cases did not have at all.

As a consequence of this practice, coupled with denying care that Traditional Medicare would have covered, the program has been determined by government audits to cost 119 percent of what Traditional Medicare costs. 

Final Thoughts

Should Home Health follow the lead of so many rural hospitals and begin to Just Say No? Our guess is that this will be a prominent topic at this October’s NAHC Conference in Tampa.

# # #

Tim Rowan, Editor Emeritus
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com Tim@RowanResources.com ©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Startup Offers $3 Caregiver Recruiting Service

by Tim Rowan, Editor Emeritus

Costly Caregiver Recruiting

Out of desperation, the nationwide caregiver shortage has driven many Home Care agency owners to resort to expensive recruiting tools. How much, for example, do you spend on services such as Indeed, ZipRecruiter, or Monster, each of which charges per-click?

A Needle in a Stack of Needles

You know how job seekers use these services, correct? They complete one resumè and send it to dozens, if not hundreds, of companies every day. When you respond to their inquiry, thinking they have a keen interest in applying for your caregiver position, they typically respond, “Now, which one are you?”

Caregiver Recruiting GoInstaCare

Caregiver Recruiting Database Emerges

In the process of building a web site and app for families to find in-home caregiver services, former Home Care agency owner Amit Shrivastava suddenly found himself with more job seekers than he could place in homes, and this after launching in only five states. His solution was to open his collection of resumés to other agencies. After we tested his idea, we believe it will one day give Indeed and the others a run for their money.

Simple Process with Customized Results

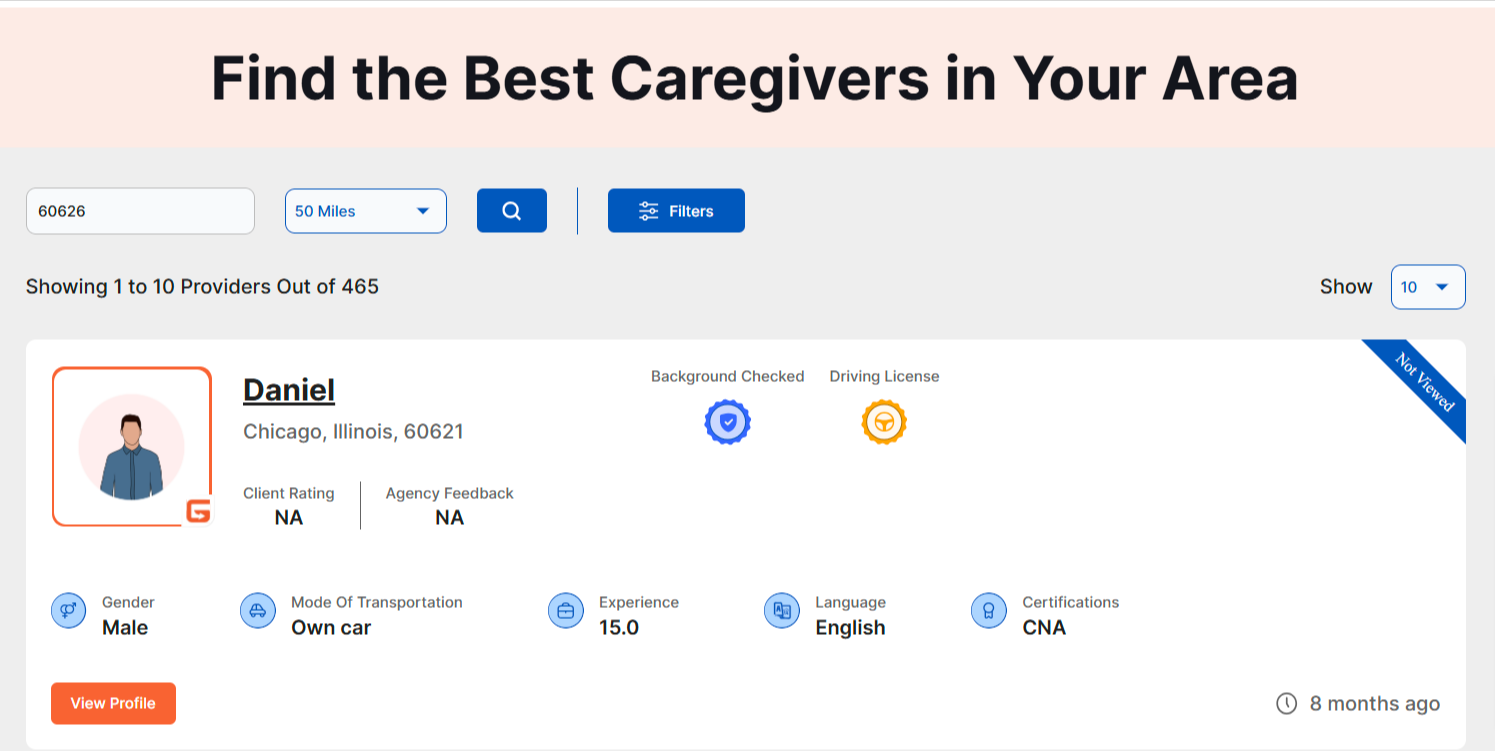
After a $200 set-up fee, GoInstaCare users can look at the names, certificates, personality types, and work preferences of 10,000 caregivers, a list that continues to grow. An easy filtering system allows the user to narrow the list by certification, gender, zip code, and experience. Each entry displays whether the caregiver has a driver’s license, his or her own car, languages spoken, and ratings from past employers and clients.

GoInstaCare performs background checks so the hiring agency knows that the caregiver has a higher degree of passing their own checks. By selecting filters, a hiring agency can focus its search to the qualifications it requires. Once the 10,000 names are filtered down to a manageable half dozen or so, the hiring agency pays $3 each to download their contact information. At that point, GoInstaCare steps back and leaves the rest of the onboarding process to their participating agency.

"Uberized" Employer

For Caregivers

Like its counterparts in ride shares, delivery services, virtual assistants, and other gig economy positions, GoInstaCare allows caregivers to set their own schedules, provide flexible rates, get paid daily, and accept or decline a job at will. Caregivers are reviewed by clients and their families directly on the GoInstaCare platform.

For Agencies

The gig job nature of the platform gives agencies the option to cover a gap in scheduling or temporarily raise employee numbers without the hiring, onboarding, training, and retention of a full-time or part-time employee. Agencies can also save a caregiver profile to share with a team, or for future reference.

Where to Find GoInstaCare

As this is written, GoInstaCare has spread to five states, Texas, Illinois, Michigan, New York, and Florida. Mr. Shrivastava told The Rowan Report there are plans to continue to expand.

There are two ways to get in touch with Amit Shrivastava. Click on this link to schedule a product demo: calendly.com/goinstacare-sales/meeting. Or sign up to use the service here: Goinstacare.com/partner-with-us

Caregiver Recruiting GoInstaCare

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

MA Past, Present, and Possible Future: Nothing Good to Report

by Tim Rowan, Editor Emeritus

Past

For at least the last five years, every Home Health conference this reporter has attended has featured at least one keynote speaker or expert panelist complaining about sparse and shrinking payments from Medicare Advantage plans. As thousands of seasonal TV ads convince more and more Medicare beneficiaries to enroll in what insurance company executive-turned-whistleblower Wendell Potter called “neither Medicare nor an advantage,” the calls from Home Health executives to turn away MA members, following the lead of many hospitals, have grown louder and more frequent.

Originally designed to extend the lifespan of the Medicare Trust Fund by bringing managed care practices to the federal healthcare program for seniors and disabled, Medicare Advantage has failed to do so. As long ago as 2021, an exposé by Fred Schulte in Kaiser Family Foundation Health News found that MA costs to taxpayers began to explode in 2018 and today equal 119 percent of what traditional Medicare should cost. We looked at more recent studies and found similar reports.

From the Experts

Referencing a study by Richard Kronick, a former federal health policy researcher and a professor at the University of California-San Diego, Schulte said, “his analysis of newly released Medicare Advantage billing data estimates that Medicare overpaid the private health plans by more than $106 billion from 2010 through 2019 because of the way the private plans charge for sicker patients. A third of that overpayment occurred in 2018 and 2019.”

Since Kronick’s 2021 report, more beneficiaries have opted in to Medicare Advantage. So far, just over half have switched from straight Medicare, with or without a supplement, and that number may reach 100 percent if those who profit most from the option have their way.

Present

In recent months, we have investigated and reported on the insurance industry’s practice of exaggerating MA member health conditions and denying care that traditional Medicare would have covered, collecting from both ends of the CMS trough. We have also mentioned several federal and state lawsuits piling up against insurance companies for both of those practices. One of our sources, The Center for Economic and Policy Research, said this in the Executive Summary of its detailed, September 2023 study:

Profiting at the Expense of Seniors: The Financialization of Home Health Care

“The nonpartisan Medicare Payment Advisory Commission (MedPAC) estimates that upcoding by MA plans that make enrollees appear to be sicker than they are costs CMS 106 percent of what traditional Medicare costs; adding in the quality bonus payments brings it to 108 percent. MA plans also enroll healthier Medicare beneficiaries, increasing their operating surplus by another 11 percent, making the payments to MA plans 19 percent higher than the payments to traditional Medicare. 

CMS’s announced goal for traditional Medicare beneficiaries is to move all of them to Accountable Care Organizations, which use the valued-based payment model, or other similar care arrangements, by 2030. CMS’s leading model to accomplish this shift is ACO REACH — a gentler, kinder version of the Trump administration’s backdoor enrollment of traditional Medicare beneficiaries in a capitated payment model.”

The Center for Economic Policy Research

Future

Past Present Future Medicare Advantage

Depending on results in the unpredictable world of politics later this year, CMS may or may not see its shift to value-based ACO models come to fruition. Kaiser News‘ Schulte examined the Heritage Foundation’s “Project 2025,” the conservative think tank’s blueprint for any possible future Republican administration, and found an entire section on the Department of Health and Human Services.

Within its “Mandate for Leadership,” the authors identify Medicare and Medicaid as “the principal drivers of our $31 trillion national debt.” While admitting that Medicare and Medicaid “help many,” the authors assert that the programs “operate as runaway entitlements that stifle medical innovation, encourage fraud, and impede cost containment, in addition to which their fiscal future is in peril.”

Rebuttal

Commenting on the Heritage Foundation’s claim, researcher Sonali Kolhatkar, writing for “OtherWords.org,” counters that this opinion is often used to justify ending social programs, but actual CMS data indicates that per person Medicare spending has plateaued for more than a decade and represents one of the greatest reductions to the federal debt. Even with 10,000 to 11,000 Boomers reaching Medicare eligibility every day, total per beneficiary expenditures have stopped climbing, hovering around $12,000 per year since 2010. Before reaching that 2010 plateau, per beneficiary spending had steadily risen from $2,000 at the program’s 1965 inception.

Medicare Advantage for All

Project 2025 proposes making Medicare Advantage the default enrollment option rather than a choice beneficiaries can opt into. With 100 percent of seniors on MA plans, already historic insurance profits will skyrocket further. But will Medicare beneficiaries benefit as well?

The Center for Economic and Policy Research cites multiple lawsuits that have proven eight of the ten largest MA plans routinely add chronic conditions – some non-existent – to patient assessments at enrollment…or later. We reported recently that UnitedHealth Group, operator of the largest MA plan, recently began sending nurses into homes to search for additional health conditions that would raise company payments from the trust fund. The report we quoted included evidence that these home visit upcodes do not lead to any treatments. The Center added that MA’s “heavily restricted networks damage one’s choice of provider along with introducing dangerous delays and denials of necessary care.”

As we have mentioned before, Medicare Advantage is neither Medicare nor an Advantage.

Medicaid also Attacked

Project 2025 also proposes restrictions on Medicaid eligibility by imposing work requirements. The blueprint sees the program for low-income Americans as a  “cumbersome, complicated, and unaffordable burden on nearly every state.” Their plan includes bringing private insurance companies in to “manage” care.

A June, 2024 report by the Center on Budget and Policy Priorities concluded that the ACA’s expansion of Medicaid helped millions of Americans who would otherwise be uninsured, and that its enabling and encouragement of preventive care actually saved money in state budgets. Last month’s report asserted “the people who gained coverage have grown healthier and more financially secure, while long-standing racial inequities in health outcomes, coverage, and access to care have shrunk.”

Project 2025 authors make no mention of a KFF News report from April 2023 that said most Medicaid-eligible people are already working. Nor does it take into account a Government Accountability Office report to Congress October 2020 and again in 2023 that determined that hourly wages in many large companies are low enough to keep even full-time workers eligible for Medicaid and SNAP. Walmart and McDonalds, to name two, land in the top five in almost every state for having Medicaid-eligible workers.

EVEN THE WALL STREET JOURNAL IS CRITICAL

Under the front page Headline “Medicare paid $50 billion to insurers for untreated ills,” a detailed WSJ investigation highlighted a number of findings, including:

  • “The questionable diagnoses included some for potentially deadly illnesses, such as AIDS, for which patients received no subsequent care, and for conditions people couldn’t possibly have, the analysis showed. Often, neither the patients nor their doctors had any idea.”
  • “Instead of saving taxpayers money, Medicare Advantage has added tens of billions of dollars in costs, researchers and some government officials have said.”
  • “Medicare Advantage has cost the government an extra $591 billion over the past 18 years, compared with what Medicare would have cost without the help of the private plans, according to a March report of the Medicare Payment Advisory Commission, or MedPAC, a nonpartisan agency that advises Congress. Adjusted for inflation, that amounts to $4,300 per U.S. tax filer.”
  • “The Journal reviewed the Medicare data under an agreement with the federal government. The data doesn’t include patients’ names, but covers details of doctor visits, hospital stays, prescriptions and other care.”
People voting

Now it is in the Hands of Voters

Home Health, Hospice, and Home Care owners, management, and workers will be voting in November. Consideration of what four years under a Project 2025-friendly administration will mean to businesses dependent on Medicare and Medicare will weigh heavily on their minds as they enter their polling booths.

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report.homecaretechreport.com One copy may be printed for personal use: further reproduction by permission only. editor@homecaretechreport.com

Payer or Competitor?

by Tim Rowan, Editor Emeritus

UnitedHealth Making Home Health Visits

Payer or Competitor…that is the question. According to a report in the Wall Street Journal, and questioned by the insurance industry’s lobbying arm, AHIP, UnitedHealth Group has increased its revenue from the Medicare Trust Fund by $50 billion by “finding” additional health issues during home visits to its MA customers.

In a July 16 investor call, CEO Andrew Witty said UnitedHealth clinicians made more than 2.5 million home health visits to UnitedHealthcare MA members in 2023. Following these visits to more than 500,000 seniors, UnitedHealth upgraded over 300,000 of them to higher payment levels by uncovering health conditions the individual seniors did not know they had.

The WSJ investigation found that between 2018 and 2021, insurers received $50 billion for diagnoses they added to members’ charts. Many of these diagnoses were “questionable,” according to that investigation.

Questionable Visits

Uncover versus Discover United Health

Though a UnitedHealth spokesperson called the analysis “inaccurate and biased,” former UnitedHealth employees told the Journal home visits are often used to add diagnoses. Clinicians say they use software during visits that offer suggestions as to what illnesses a patient might have.

CEO Witty maintained in the investor call that the practice is good for seniors. “UnitedHealth clinicians discovered more than 3 million gaps in care through home visits in 2023,” he reported, “and 75% of patients receive follow-up care in a clinic within 90 days of a home visit.” 

He added that the United home visit program “helps patients live healthier lives and saves taxpayers money,” concluding. “…Medicare Advantage makes programs and results like this possible.” 

The Journal concluded with the finding that few of these upgraded seniors are ever seen by a physician for their newly discovered health conditions. 

# # #

Tim Rowan, Editor Emeritus

Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2024 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in Healthcare at Home: The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com