For better or worse, healthcare has begun the inevitable adoption of Artificial Intelligence. Before you consider adopting AI technology, know that there is a wrong way and a right way to use AI in healthcare. In a companion article this week, we describe the criticism insurance companies are getting for deploying AI in healthcare to harm patients. As a balance, here is a review of a product that we find to be using AI in healthcare to help both patients and Home Health Agencies.
The Problem
Home Health referral documents from physicians or hospitals can consist of more than 100 electronically transmitted pages. Some agencies report occasional packets exceeding 1,000 pages, often in a variety of data formats. Some are standard data formats, such as a face sheet, but most are unstructured, consisting of images or narrations, sometimes in paragraphs, sometimes in incomplete sentences. Worse, patient data interoperability can be limited by unstructured data.
More often than not, most of these pages are never read. Thoroughly interpreting that much data is nearly impossible for a human. Consequently, nurses too often approach an admission evaluation visit with an incomplete picture of a patient. The result can be gaps in care or treatment, inaccurate OASIS assessments, incomplete or poorly sequenced diagnosis codes, and improper care plans. These obstacles can impact both patient outcomes and agency revenue.
One Newly Available Solution for the Right Way to use AI in Healthcare
We recently attended a product demonstration and followed it up with updated descriptions to learn details about new product developments. Over the next three months, Select Data, in full disclosure one of our sponsors, will be introducing an AI-powered suite of products that has been designed over many years of development to support clinical, data driven decision-making. One by one, it addresses the problems described above.
The new system, SmartCare, empowers clinicians to harness previously hidden insights while reducing bias and cognitive overload. It enables them to steer their decisions with enhanced precision while maintaining their pivotal role in patient care, eliminating one of the common reasons many Home Health administrators hesitate to invite AI into agency processes. It does, however, make the care team’s job easier and facilitates better decision-making.
AI can read those 100 to 1,000 page referral documents in minutes, where a human may require days.
SmartCare uses AI to synthesize relevant medical history to provide a care snapshot highlighting the key diagnosis, focus and considerations for care, and recommended OASIS clinical discipline. It highlights any areas for clarification needed from physician or admitting nurse.
Clinicians can search and index specific words in unstructured data, such as narratives, to instantly identify any detail of a patient’s condition in an easy-to-read interface. Nurses approach the initial OASIS visit armed with all of a referring clinician’s relevant care findings.
Recommendations for diagnostic codes strictly follow Medicare PDGM guidelines.
Suite of Tools
1 – RISE stand for Rapid Intake Summary & Evaluation. This component of the suite summarizes all clinical data from referral sources and your EHR. It compiles this data to provide clinically relevant diagnoses, focus of care, and recommendations for skilled disciplines. This is the part of the tool that reads referral documents and supports informed decision-making. The advantages we detected go a bit beyond the technical.
When clinicians, reviewers, coders, and office staff all have access to the same patient information, it would seem that communication among disciplines would improve and that care coordination would be enhanced. It also seems logical that continued experiences of advanced access to previously hard-to-find physician comments would gradually break through the AI fear barrier reported by so many clinicians and other professionals. Select Data will provide us with actual client experiences to verify our assumptions once they have been compiled.
2 – ACE, or Admission Clinical Evaluation is SmartCare’s clinical support summary tool. It deploys AI to understand accepted OASIS assessment criteria. It then uses this knowledge to extract assessment and narrative data from nursing and therapy evaluations. With streamlined, pertinent data at the point of care, the entire care team has the same patient data. Having the same patient data enables more informed decision-making.
ACE links all patient data back to its source assessment. Doubt about the AI’s credibility should gradually diminish, even among the most AI-resistant users. Every analysis and recommendation is explained in clear language so that clinicians are likely to understand the rationale behind them. The goal is to replace every “I’m not going to let a machine tell me what to do” with “I’ll take this information into consideration with my human insights.”
Pricing
We are honoring Select Data’s request to allow them to build personalized price quotes to every prospective client. They will be represented at several state and national conferences this year. Alternatively, interested HHA representatives can contact EVP Ted Schulte at Ted.Schulte@SelectData.com
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com Tim@RowanResources.com
You know the routine. Everyone does. You log into your bank, airline account, or health insurance web portal, enter the correct password, and are directed to look on your smartphone for a code to enter to fully authorize your login. The name for this is Multi-Factor Authentication, or MFA. Lack of MFA procedures leaves your company at risk, which UnitedHealth discovered when it was grilled by Congress about the cyberattack on Change Healthcare.
United Health Grilled by Congress
In his testimony to the House Energy and Commerce Committee Wednesday, UnitedHealth Group CEO Andrew Witty blamed the absence of MFA as the weak link that allowed a ransomware attack to cripple subsidiary Change Healthcare in February. The breach had ripple effects throughout healthcare, given Change’s role as fiscal intermediary for thousands of providers. Healthcare systems on every level were unable to file claims and receive payments.
Asked by the committee why Change Healthcare, which United acquired in late 2022, did not have MFA in place, Witty testified, “Change Healthcare was a relatively older company with older technologies, which we had been working to upgrade since the acquisition. But for some reason, which we continue to investigate, this particular server did not have MFA on it.”
CBS News reported that Change Healthcare processes 15 billion transactions a year. “The scale of the attack,” their report stated, “meant that even patients who weren’t customers of UnitedHealth were potentially affected. Personal information that could cover a ‘substantial portion of people in America’ may have been taken in the attack.” The breach has already cost UnitedHealth Group nearly $900 million, plus the $22 million ransom Witty decided to pay to the hackers.
The Russia-based ransomware gang, ALPHV, or “BlackCat,” claimed responsibility for the attack, bragging that it stole more than six terabytes of data, including “sensitive” medical records. The attack triggered a disruption of payment and claims processing around the country.
We followed up our initial report on the attack with CMS guidance on March 20, 2024 and an update on April 11, 2024, with reports that Change Healthcare was being blackmailed again by another ransomware gang, RansomHub, who claimed to have 4TB of data from Change Healthcare and demanded another ransom payment.
Walmart & Optum, UnitedHealth Trouble Spots?
UnitedHealth Group is also in headline news this week for two other reasons. The company’s Optum division, which owns home care giant CenterWell,formerly Kindred at Home, and which is awaiting government approval for its bid to acquire Amedisys, has quietly been executing a reduction in force. Reports are that the bulk of the layoffs are hitting “Optum Virtual Care,” the name given to naviHealth following its $1 billion acquisition in 2020. Following a surge in demand during the pandemic, the company is apparently abandoning telehealth services.
A planned 10-year collaboration between UnitedHealth and Walmart to provide virtual healthcare services ended Tuesday after only one year. On April 30, the retail giant announced that it will close its 51 health centers across five states due to the “challenging reimbursement environment” and rising operating costs, which have resulted in a lack of profitability. Like Optum Virtual Care, the centers were providing virtual services via telehealth.
A sign of the post-pandemic times? Perhaps. We will keep watching.
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com Tim@RowanResources.com
Average 2023 hourly rate for home health aide increased 5.2%
Hourly per visit nurse rate decreased 1.6% with facility prices mixed
Washington and New Hampshire most expensive states for home health aides
illumifin’s comprehensive study provides insight which empowers consumers, insurers, and providers by benchmarking the prices of senior care.
WOODBURY, Minn., March 27, 2024 /PRNewswire/ — illumifin, the leading insurance administration and claims solution provider for long term care (LTC) insurance, has just released its 2023 Cost of Care study and comprehensive analysis. Now in its tenth year, this longitudinal study includes national, state and regional costs of various care services, spanning skilled nursing, adult day care, home health care and assisted living facilities.
illumifin’s Cost of Care study gathers tens of thousands of data points from care providers nationwide, with results normalized by the company’s in-house actuarial and data science teams. Insurers and financial services providers rely on this data for both forecasting and stakeholder education as well as informing customers and agents about national and regional cost variations. In addition, care providers benefit from understanding the market rates for services in their area. These insights are also accessible via illumifin’s What Care Costs website, which offers interactive maps and projection tools to sort, rank and evaluate average costs of LTC services across the US.
illumifin’s study found that the average hourly rate for a home health aide in 2023 was $30.62, an increase of 5.2 percent over the prior year. Meanwhile, the average per-visit rate for a registered nurse in 2023 was $147.72, a decrease of 1.6 percent over the prior year, potentially reflecting rates beginning to normalize post pandemic.
The research also shows facility prices were mixed. The average assisted living facility rates increased between 0.6 and 3.8 percent in 2023 depending on room type, reversing course from the pandemic where assisted living facility rates had been trending downward. However, skilled nursing facility rates experienced a small decrease in 2023 between 0.4 and 1.0 percent.
The most expensive states for home health aides were Washington and New Hampshire, whereas Mississippi and Louisiana were the least expensive. Meanwhile, the most expensive assisted living rates were found in New Hampshire and New Jersey, while the lowest assisted living prices were found in Alabama and Oklahoma.
“We are proud to leverage our 30 years of experience in senior care to provide actionable data for insurers, consumers, providers and financial institutions,” said Peter Goldstein, illumifin’s President and CEO. “Our focus remains on customer centric initiatives which assist in managing risk and planning for the future. Our Cost of Care survey has proven valuable to not only to our business partners but providing valuable knowledge to consumers and their families as they navigate the maze of service types when making care decisions.”
The study, interactive tool and data are available for use by insurers, providers and financial services firms. For more information regarding illumifin’s Cost of Care Study, please contact Jennifer Frost via email at jenniferfrost@illumifin.com.
About illumifin illumifin provides third party administration and technology services to individual and group insurers. The company, launched in 2021, blends insurance industry knowledge, technology leadership and operational execution to prepare insurers for the digital future. illumifin is a diverse, passionate and empowered team of insurance specialists committed to the growth and success of its customers. With illumifin, there’s a brighter future. Visit www.illumifin.com.
Contact: Chris Tofalli Chris Tofalli Public Relations, LLC 914-834-4334
NEW REPORT FINDS THAT DIGITAL DIABETES MANAGEMENT TOOLS FAIL TO DELIVER MEANINGFUL HEALTH BENEFITS TO PATIENTS WHILE INCREASING SPENDING
Independent evaluation from Peterson Health Technology Institute recommends new directions for digital diabetes solutions
NEW YORK — Peterson Health Technology Institute (PHTI), an independent organization that evaluates healthcare technologies to improve health and lower costs, today released a new evaluation of digital diabetes management tools. These solutions are used by millions of Americans and have been funded by $58 billion of investment and mergers and acquisitions, yet the evidence shows that the technologies do not deliver meaningful clinical benefits, and result in increased healthcare spending.
The analysis, conducted by a team of health technology assessment experts and informed by clinical advisors, evaluated eight widely used digital tools that people with Type 2 diabetes use to track and manage blood glucose using a noncontinuous glucometer.
The report found that people who use these tools achieve only small reductions in hemoglobin A1c (HbA1c) compared to those who do not, and these reductions are not sufficient or sustained enough to change the trajectory of their health, care, or long-term prognosis, including cardiovascular risks. The solutions also result in increased overall healthcare costs. One promising solution, Virta, supports nutritional ketosis to achieve diabetes remission in patients who follow the rigorous diet modifications.
“When these digital diabetes management tools launched more than a decade ago, they promised to improve health outcomes for people with diabetes and deliver savings to payers. Based on the scientific evidence, these solutions have fallen short, and it is time to move toward the next generation of innovation,” said Caroline Pearson, executive director of PHTI. “Patients with diabetes invest time, energy, and resources in these tools, and they deserve to experience meaningful, positive benefits for their health. The healthcare sector as a whole needs transparent, accurate information about the clinical and economic impact of these digital tools that are taking up precious healthcare dollars.”
PHTI’s rigorous analysis incorporated an evidence-based assessment framework and review of more than 1,100 articles, including 120 submitted to PHTI by companies evaluated in the report. PHTI’s ratings are at the category level, including remote patient monitoring solutions that support providers, and behavior and lifestyle modification solutions that engage users to improve their diet, exercise, and self-management.
HbA1c is the standard form of measurement of glycemic control in diabetics. The studies show that these digital tools deliver small reductions in HbA1c of 0.23 to 0.60 percentage points compared to usual care. These results are generally below industry standards for Minimal Clinically Important Difference (MCID) of 0.50 percentage points. Further, the evidence indicates that this small improvement is not durable because the reduction is not sustained over time.
Additionally, PHTI’s analysis did not find evidence to demonstrate that digital diabetes management tools improve other health factors, including weight loss, body mass index, blood pressure, cholesterol, or other common conditions impacting people with diabetes. The analysis also concluded that, despite the disproportionate impact of diabetes on low-income and racially and ethnically diverse communities, these tools are not currently being deployed in ways that improve health equity.
PHTI’s evaluation further determined that these tools increase net healthcare spending. This is due to the fact that price for the solutions exceeds the associated healthcare cost savings, because the minimal clinical benefit does not enable the patient to avoid other care or treatments. For patients using tools in the remote patient monitoring category, annual spending is projected to increase by $2,002 for commercial insurance patients, by $1,011 for Medicare patients, and by $723 for Medicaid patients, as a result of higher provider payments. For patients using tools in the behavior and lifestyle modification category, annual spending is estimated to increase by $484 for commercial insurance patients, by $513 for Medicare patients, and by $574 for Medicaid patients. For all payers, the increased spending associated with virtual diabetes solutions has a significant impact on total spending given how many people are eligible to use the solutions, including 4.3% of those with commercial insurance, 17.0% of those with Medicare, and 4.8% of those with Medicaid.
In addition to its scientific literature review, PHTI proactively engaged the companies included in the report and provided an opportunity for them to share data and product information. Companies in PHTI’s evaluation include DarioHealth, Glooko, Omada, Perry Health, Teladoc (Livongo), Verily (Onduo), Vida, and Virta. The evaluation considered evidence about which populations stand to benefit the most from using the technology, as well as the durability of clinical impacts given the importance of sustained glucose control to achieve health benefits. The economic analysis modeled expected healthcare savings resulting from improved glycemic control for patients using digital diabetes management solutions who are enrolled in Medicare, Medicaid, and commercial insurance.
PHTI identified two potential bright spots for digital diabetes management tools. Initial data showed that Virta users are much more likely to achieve clinically meaningful benefits in glycemic control, including diabetes remission and the ability to reduce or eliminate their diabetes medications, if they can maintain the rigorous dietary requirements of the intervention. The other area of greater potential is among patients with higher starting HbA1c levels who are newly starting insulin. By engaging these patients at an early critical transition point in their care, digital solutions could have more impact by helping establish good self-management habits among these higher-risk patients.
In the United States, about one in seven adults—more than 38 million living in the U.S.—has Type 2 diabetes, which is the eighth leading cause of death. At over $400 billion of total healthcare spending annually, diabetes is the most expensive chronic condition to treat and manage. Given the critical role of patient self-management, investment in digital health tools has surged in recent years.
Throughout the assessment process, PHTI worked with a range of independent evaluation partners, clinical advisors, patients with Type 2 diabetes, and other stakeholders. Report contributors and reviewers included:
Curta: assessed the clinical and economic impact of these technologies using the published ICER-PHTI Assessment Framework for Digital Health Technologies, including the systematic literature review and budget impact assessment
Charm Economics: identified what technologies cost to deliver, how they work, and their impact on patients and purchasers
Institute for Clinical and Economic Review (ICER): co-developed the ICER-PHTI Assessment Framework for Digital Health Technologies, and was consulted to review its implementation in this report
Ami Bhatt, MD, chief innovation officer of the American College of Cardiology
Richard Milani, MD, chief clinical innovation officer, Sutter Health; former innovation lead at Ochner Health System
Karen Rheuban, MD, co-founder and director of the University of Virginia Center for Telehealth
“Managing diabetes is complex and essential to future cardiovascular health. Patients will gain agency and drive better clinical benefit if they direct their time and effort towards effective interventions rather than tools that provide marginal or no benefit,” said report contributor Ami Bhatt, MD, chief innovation officer of the American College of Cardiology.
“New diabetes technologies need to be easier to use, by the people who need them most, at lower cost than standard care, and provide real health benefits,” said report contributor Richard Milani, MD, chief clinical innovation officer at Sutter Health. “This evaluation suggests there is room for new innovations that deliver for patients and address worrying increases in healthcare spending.”
The PHTI report provides recommendations and best practices for innovators, providers, and payers. The next generation of diabetes management solutions should aim for clinically meaningful improvements in glycemic control, potentially integrating continuous glucose monitors and new GLP-1 obesity medications. Solutions should also generate sufficient evidence to support broader adoption, and they should prioritize access for populations who need them most. Providers of diabetes care should have clarity about the performance of these digital solutions when recommending them to their patients. Payers, including health plans and employers, should adapt their contracting approach to require transparency about the solution’s usage and benefits within their covered population and to include financial performance guarantees tied to clinical outcomes.
“PHTI is filling an important role in delivering actionable and market-facing information to digital health purchasers about what solutions will make a meaningful impact on health outcomes for members, making them worth investment,” said Peter Long, PhD, executive vice president, Strategy and Health Solutions at Blue Shield of California and a PHTI Advisory Board member. “Having an organization like PHTI cut through the noise of digital health options helps payers make faster and more effective decisions for members so that we can focus on the big work of transforming the healthcare system.”
PHTI has announced that future assessment areas include virtual physical therapy, blood pressure monitoring, and mental health tools.
# # #
About the Peterson Health Technology Institute
The Peterson Health Technology Institute (PHTI) provides independent evaluations of innovative healthcare technologies to improve health and lower costs. Through its rigorous, evidence-based research, PHTI analyzes the clinical benefits and economic impact of digital health solutions, as well as their effects on health equity, privacy, and security. These evaluations inform decisions for providers, patients, payers, and investors, accelerating the adoption of high-value technology in healthcare. PHTI was founded in 2023 by the Peterson Center on Healthcare. For more information, please visit PHTI.com.
Primary caregivers – often patients’ family members – are crucial players in home care. Without them, it can be impossible to provide home care services and to keep patients in their homes. If patients cannot care for themselves, reliable caregivers are an essential prerequisite for the provision of all types of home care.
Caregivers have a very “hard row to hoe” because caregiving is physically, emotionally, intellectually, and spiritually demanding. Is it possible that enhanced assistance for caregivers can positively impact quality of care? Intuitively, the answer to this question seems to be “yes.” What additional assistance may be helpful and can providers offer it?
Here are some initial ideas for helpful assistance:
Caregiver support groups
More intensive education about patients’ clinical conditions, with an emphasis on signs and symptoms of changes in patients’ conditions and what to do about them
Assistance from volunteers, especially for patients who are chronically ill
The next question is whether providers can offer additional assistance, such as the activities described above. This issue has been addressed by the Office of Inspector General (OIG) of the U.S. Department of Health and Human Services, the primary enforcer of fraud and abuse prohibitions. The OIG has clearly stated that providers may not give patients or potential patients free items or services that cost more than $15.00 at a time or more than $75.00 in aggregate per calendar year.
In Advisory Opinion No. 18-05; issued on June 18, 2018; the OIG also addressed the circumstances under which providers can establish “caregiver centers” that provide or arrange for free or reduced-cost support services to caregivers in local communities. The provider that requested this Advisory Opinion recognized the difficulties faced by primary caregivers and, consequently, established a caregiver Center.
The Center is staffed primarily by volunteers. Private donations fund the Center and none of its costs are shifted to any federal health care program.
The Center either directly or, in collaboration with local nonprofit organizations, provides free and fee-based services to caregivers. Free services include, but are not limited to, access to a resource library, various educational sessions, a short-term equipment lending program, and free on-site respite care during events sponsored by the Center and attended by caregivers. The Center offers or partners with other providers in the community to offer stress reduction workshops, low-cost ride-share programs, and additional respite care.
The provider does not specifically market the Center’s services, but information is available on its website, social media pages, and in brochures. These sources make it clear that every caregiver is eligible to use the Center’s services, regardless of healthcare provider or payor.
Center staff members do not market, promote, or make referrals for any medical items or services that are reimbursable by federal care programs and do not provide any items or services that are reimbursable by federal health care programs. Referrals for services include a comprehensive list of local service providers offering requested services, without recommending any provider over another.
In response to this request, the OIG first stated that the key question is whether these services are likely to influence caregivers to select the provider or items or services reimbursable by the Medicare or State health care programs in the future. The OIG then acknowledged that the services provided have intangible, psychological value to caregivers. Some of the services relieve caregivers of expenses they might otherwise have incurred. The OIG also noted that many of the support services take place on the provider’s premises, which might encourage selection of the provider for future services. The OIG also acknowledged that this arrangement does not fit into any safe harbor or exception under the federal anti-kickback statute.
Nonetheless, the OIG said that it would not impose sanctions on the provider because:
The services offered at the Center primarily benefit caregivers, not patients.
The Center’s services are available to all caregivers.
The provider does not actively market the Center and its services.
The Center is unlikely to increase costs to federal health care programs.
Caregivers have a tough job and need the support of home care providers. Based on this Advisory Opinion, the OIG has provided guidance about how home care providers of all types can expand their support for caregivers.
Illumifin, an insurance administration and claims solution provider for long term care (LTC) insurance, has released its 2023 Cost of Care study. The longitudinal study is now in its tenth year and includes national, state, and regional costs of services across skilled nursing, adult day care, home health care, and assisted living facilities.
The study found that the average rate for a home health aide in 2023 was $30.62 per hour, a 5.2% increase over 2022. The average per-rate visit for a registered nurse was $147.72, a 1.6% decrease over the prior year. Assisted living facility rates are up .6 – 3.8% nationwide, while skilled nursing facility rates decreased .4 – 1.0%.
As costs continue to rise, CMS will need to adjust its proposed per-episode base pay cut for FY 2025. We continue to report on the proposed cuts from CMS and MedPAC, who argue home health agencies are being overpaid, even as costs of supplies and hourly pay go up.
# # #
Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com
In December, 2023, The Medicare Payment Advisory Committee (MedPAC) recommended a 22% payment reduction for hospice providers. This week, they’ve recommended additional cuts once again.
MedPAC has just released the March, 2024 Medicare Payment Policy Report, issued to Congress. The initial statement from MedPAC recognized the long-lasting impact of the COVID-19 pandemic on healthcare providers and the record inflation rates. The commission admits that the pandemic has caused burnout and personal risk to clinicians and other health care workers. The commission also admits that the effects of COVID-19, PHE-related policy changes, and emergency funding made it difficult to interpret the indicators of adequacy in Medicare’s payment rates.
The commission openly states that the fundamental problem with FFS Medicare payments is that providers are paid more when they deliver more services, whether or not those services provide value. The call for additional payment reforms to force providers to coordinate care over time and across care settings and to eliminate what may be necessary services that MedPAC doesn’t deem valuable.
Home Health Agencies
The commission reports the Medicare margins for HHAs at 22.2 percent in 2022. The commission calculates these margins excluding some fixed costs. The margins, according to the commission, indicate that FFS Medicare payments exceed the costs of care. This should incentivize HHAs to take on additional beneficiaries, as the margins are calculating using only costs that diminish by volume.
The commission notes a drop in HHA use in 2022 and lists possible causes including:
The number of FFS Medicare beneficiaries is lower due to the increased enrollment in Medicare Advantage
Lower use of inpatient hospital care among FFS beneficiaries
Hospitalized FFS beneficiaries were less likely to be discharged to home health care (no reason for this was given)
More FFA beneficiaries are using SNFs after hospitalization (no reason for this was given)
The staffing shortages reported by HHAs limit the volume of services they can provide
The commission implies that the staffing shortages are not a factor in the decline in HHA usage. The Department of Commerce’s employment data indicates staffing levels that are currently higher than pre-pandemic levels. Even though the data includes HHAs, hospice, private duty, pediatric agencies, and other home care providers, the commission still contends that Medicare HHAs comprise a significant enough share of this group to conclude there is no staffing shortage nationwide.
The commission also reports that the decrease in the number of HHAs nationwide is not a factor in the decline of HHA usage, because most beneficiaries still live in an area with at least on HHA. The commission recognizes that the number of employees and contract laborers is not used to calculate access to care, even though it is a factor. They also admit that an HHA does not need to serve an entire area to be counted as serving the area, and that the capacity to serve additional beneficiaries is not considered.
The report recognizes that preventable readmissions to hospitals is lower among for-profit and free-standing HHAs than for hospital-based care. However, the commission dismisses this data in favor of the all-cause measure of hospitalization, which is much higher for HHAs. This measure covers 60 days and includes all hospitalizations for any cause and includes community-admitted and home health admitted patients. Essentially, MedPAC is assigning a 14.2 percent hospitalization rate to all home health patients, regardless of the cause of hospitalization, whether or not it is deemed preventable, and whether or not it is in any way related to the initial 30-day-period of post acute care.
The average cost of a 30-day period increased by 4 percent in 2022, due to a higher cost per visit. The HHAs are combatting this by reducing the number of in-person visits per 30-day period. Since MedPAC did not track telehealth visits, there is no data on the overall cost per visit, regardless of whether it was in person or remote. HHAs are working within the PDGM model for reimbursement by lowering their overall costs per 30-day period through telehealth visits, remote patient monitoring, and other technologies implemented to increase efficiency in HHAs. MedPAC wants to penalize this by reducing payment rates. This will only serve to push HHAs to further decrease the number of visits, which will impact quality of care, satisfactions rates, and rehospitalization rates.
The commission concludes that because the payments exceed the costs, the benefits of home health care are devalued as a substitute for more costly care options. MedPAC argues that the overpayment since 2000 creates higher expenditures for beneficiaries, but fails to provide data to this effect.
As noted by NAHC, there are flaws in MedPACs calculations as well as in the foundation of their position:
Exclusions such as taxes, telehealth, and marketing in cost calculations incorrectly inflate the margins
MedPAC relies heavily on the CMS calculations for budget-neutrality, which NAHC has already refuted as incorrect, bordering illegal formulas
The data used in these calculations omitted all HHAs that are hospital-based.
NAHC, along with other agencies, will continue to advocate on behalf of HHAs, hospice providers, and other home-based care agencies in front of Congress to ensure these disastrous cuts will not become permanent inclusions in Medicare policy. We will continue to bring you updates as this issue continues to unfold.
# # #
Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com
On March 15th, the Centers for Medicare & Medicaid Services (CMS) issued a Center Informational Bulletin (CIB) that provides guidance and flexibilities to mitigate the impacts on providers resulting from the Change Healthcare Hack. In the guidance, CMS advises state Medicaid agencies that certain requirements will not be enforced, until June 30th, to enable ongoing funds to flow to providers and to prevent disruption of access to Medicaid services, prevent associated negative health outcomes, and avoid solvency issues for providers.
The most important component of the guidance is the ability for states to make interim payments to providers to avoid operational disruptions. Federal law and regulation does not allow for “advance payments” in Medicaid fee-for-service systems, despite their availability in Medicaid managed care environments; however, states can make interim payments to providers subject to reconciliation with actual services delivered.
CMS stresses that such interim payments are not advanced payments or prepayments prior to services furnished by providers, but rather are payments for services furnished that are subject to final reconciliation once the state has access to individual claims data currently inaccessible due to the cybersecurity incident.
The flexibilities CMS discusses in the guidance include:
Modifying required timelines for public notice, public process, and Tribal consultation and to obtain an earlier effective date for certain kinds of SPAs than would otherwise be possible;
Use interim payment methodologies to pay providers without current period claims data, as long they are determined via current approved payment rates, limiting the interim payments to the amount expected for each specific provider based on recent history, and reconciling the interim payments with final payments based on the actual services provided once they can be properly identified. These could be effective retroactively to the date when claims payment processing was disrupted due to the cybersecurity incident and could last until June 30, 2024;
Suspend beneficiary cost sharing requirements described in their state plans when necessary to avoid service disruptions for Medicaid beneficiaries for services affected by the hack;
CMS also includes language urging Medicaid managed care plans to make prospective payments to impacted providers and reiterating that plans do not need prior CMS authority to make prospective payments to providers. CMS also indicates that plans can:
Suspend or modify prior authorization requirements;
Allow early prescription refills and/or extend the length of prescription refills;
Extend existing prior authorizations;
Suspend out-of-network requirements; and
Modify or update cost-sharing requirements to be consistent with any changes that are made in the Medicaid state plan.
This week, we look at the state of the healthcare industry, vis a vis payers that do not pay.
While Home Health and Hospice leaders talk at every gathering about refusing to accept Medicare Advantage clients, some large Integrated Healthcare Systems are actually doing it. Other hospitals are responding to difficult payers by laying off staff, or even closing. The HHS Office of Inspector General repeatedly fines insurance companies for upcoding to gain inflated, unjustified monthly payments. Meanwhile, insurance companies report record profits, with their MA divisions leading the way. The fines go into the “cost of doing business” column.
March, 2024, Becker’s Hospital Review: Bristol (Conn.) Health will eliminate 60 positions, 21 of which are currently occupied and will result in layoffs at Bristol Hospital. The hospital’s CEO, Kurt Barwis, told a local newspaper a lack of reimbursement from insurers left the hospital without a choice but to cut staff.
October, 2023, NPR: Since 2010, 150 rural hospitals have closed. Under CMS’s “Critical Access” designation, Medicare pays extra to those hospitals to compensate for low patient volumes. MA plans do not. Instead, they offer negotiated rates that are lower than what traditional Medicare would pay.
December, 2023, Becker’s Financial Management: 13 additional hospital systems cut ties with Medicare Advantage plans since October.
What is going on?
The Medicare Payment Advisory Commission, MedPAC, believes it has learned the answer. In its March 15, 2024 report to Congress, the Commission called for a “major overhaul” of Medicare Advantage policies. It says it found that the program, designed to lower costs and extend the lifespan of the Medicare trust fund, does not save money but costs the fund more than if all beneficiaries were on traditional Medicare, $83 billion more in 2024.
Calling it, too politely, “coding intensity,” MedPAC concurs with the OIG that MA plans routinely exaggerate patient conditions. The report claims it will amount to MA clients appearing to need 20% more healthcare than fee-for-service beneficiaries, when they do not. Padded coding, MedPAC says, will increase Medicare premiums by $13 billion in 2024.
“A major overhaul of MA policies is urgently needed for several reasons,” the commission wrote in its report. MedPAC cited several problems that need to be addressed, including the disparity in costs between beneficiaries in fee-for-service Medicare and MA, a lack of information on the use and value of supplemental benefits, and challenges setting benchmark payment rates.
A proposal currently making its way through Congress would reduce supplemental payments to insurers, who threaten to raise premiums and cut benefits if their inflated benchmark payments are lowered.
“If payments to MA plans were lowered, plans might reduce the supplemental benefits they offer,” MedPAC wrote in its report. “However, because plans use these benefits to attract enrollees, they might respond instead by modifying other aspects of their bids.” The barrage of TV ads, featuring aging celebrities, have been found to be deceptive and too often backed by shady front companies representing brokers, not insurance companies. The brokerage company behind the Joe Namath ads, for example, has reorganized and changed its name three times.
Pushback from AHIP, the insurance industry lobbying organization, has been as expected. “MedPAC’s estimates are based on ‘speculative assumptions’ and ‘overlook basic facts about who Medicare Advantage serves and the value the program provides.'”
MedPAC asserts that its estimates are based on history, not speculation.
Healthcare Providers Beg to Differ
A lack of payments from Medicare Advantage plans is one reason the Connecticut hospital is laying off staff, the Hartford Courant reported March 14. CEO Kurt Barwis told the newspaper Medicare Advantage plans have been denying claims more frequently while delaying payments for the claims they do approve. “Our primary care is to take care of patients, their single focus is shareholder value and profits,” Mr. Barwis told the Courant. “The Medicare Advantage abuse is outrageous.”
The strategy insurance companies deploy to avoid providing care, Barwis continued, is excessive prior authorizations, coupled with delayed payments. This obstacle to care is directly in opposition to CMS policy. MA divisions of large insurers respond that they are private insurance and allowed to impose their own treatment approval policies. MedPAC says this claim is incorrect.
Richard Kronick, a former federal health policy researcher and a professor at the University of California-San Diego, said his analysis of newly released Medicare Advantage billing data estimates that Medicare overpaid the private health plans by more than $106 billion from 2010 through 2019 because of the way the private plans charge for sicker patients. Kronick added that there is “little evidence” that MA enrollees are sicker than the average senior, though risk scores in 2019 were 19 percent higher in MA plans than in original Medicare. That gap continues to widen.
Where does this excess taxpayer money go?
2023 Medicare Advantage business division profits and 2022 CEO compensation reported by publicly traded companies:
UnitedHealth Group: $22.4 B (Andrew Witty $20,865,106)
Aetna (CVS): $8.3 B (Karen Lynch $21,317,055)
Elevance Health (Anthem): $6 B (Gail Boudreaux $20,931,081)
Cigna: $5.1 B (David Cordani $20,965,504)
Centene: $2.7 B (Sarah London $13,246,447)
Humana: $2.5 B (Bruce Broussard $17,198,844)
We found one curious outlier. Molina Health, with annual revenue 10 percent of UnitedHealth Group’s income and 2.16 percent of the market, paid its CEO $22,131,256 in 2022.
Download the entire MedPAC 2024 report here. Chapter 7 is the Home Health section. A summary of MedPACs recommendations begins the chapter thus, “For calendar year 2025, the Congress should reduce the 2024 Medicare base payment rates for home health agencies by 7 percent.”
# # #
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com Tim@RowanResources.com
The U.S. House Ways and Means Committee held a hearing on March 12, 2024 to address the need for access to care-at-home services in rural and underserved communities. The advisory board heard from several witnesses including two care at home patients, a medical doctor, the founder and CEO of Cadence, and a professor of Health Care Policy and Medicine at Harvard Medical School.
Committee Chairman Jason Smith (MO) said, in his opening statement, “Where someone lives, works or raises a family should not be a barrier to getting top of the line health care. One of our priorities on this Committee is helping every American get health care in their community.”
With the Medicare telehealth and Hospital at Home programs scheduled to expire at the end of this year, Smith is urging the committee to see the profound impact that lack of access to healthcare would have on patients in rural and underserved communities. He want on to say that the “tired approaches…have not made a meaningful impact for enough patients.”
Cutting edge technology and new approaches to make Americans healthier and increase access to care in rural areas are needed. Smith recommends examining provider reimbursement and adding patient and taxpayer protections to “ensure access, demonstrate value, and prevent waste, fraud, and abuse.”
Read Chairman Smith’s opening statement here. Watch the witness statements at the hearing here.
The American Telemedicine Association and ATA Action expressed appreciation to the Committee in a press release issued just after the hearing. “We are grateful to the House Committee on Ways and Means for examining the opportunities in moving care into the home in order to benefit patients, particularly those in rural and underserved communities,” said Kyle Zebley, Senior Vice President, Public Policy, the ATA and Executive Director, ATA Action.
Read the full press release from the American Telemedicine Association and ATA Action here.
# # #
Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com




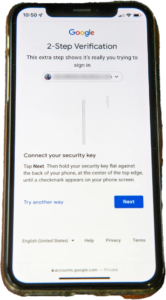 for a code to enter to fully authorize your login. The name for this is Multi-Factor Authentication, or MFA. Lack of MFA procedures leaves your company at risk, which UnitedHealth discovered when it was grilled by Congress about the cyberattack on Change Healthcare.
 formerly Kindred at Home, and which is awaiting government approval for its bid to acquire Amedisys, has quietly been executing a reduction in force. Reports are that the bulk of the layoffs are hitting “Optum Virtual Care,” the name given to naviHealth following its $1 billion acquisition in 2020. Following a surge in demand during the pandemic, the company is apparently abandoning telehealth services.

 Kristin Rowan has been working at Healthcare at Home: The Rowan Report since 2008. She has a master’s degree in business administration and marketing and runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in event planning, sales, and marketing strategy. She has recently taken on the role of Editor of The Rowan Report and will add her voice to current Home Care topics as well as marketing tips for home care agencies. Connect with Kristin directly kristin@girardmarketinggroup.com or


 Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information:


