Private Duty Fraud Enforcement

by Elizabeth E. Hogue, Esq.

The Future of Private Duty/Home Care

It Begins with Fraud Enforcement

Use of private duty/home care services continues to increase. It has become increasingly clear, however, that companies will not be permitted to care for patients who need these services without considerable additional oversight.

The proverbial “bottom line” is that private duty/home care companies will be under greater scrutiny and regulation. The instances of gross mistreatment of patients, some of which we have described in previous articles, are too shocking and lurid. And caregivers about whom lip service is given about their need for support have been mistreated by private duty companies.

And Then There's This:

The feds are convinced that there is rampant fraud in state Medicaid Programs to the tune of millions, if not billions, of dollars that has not been addressed. The number of fraud strike forces, task forces, etc. targeting companies that provide services to Medicaid recipients are now too numerous to count.

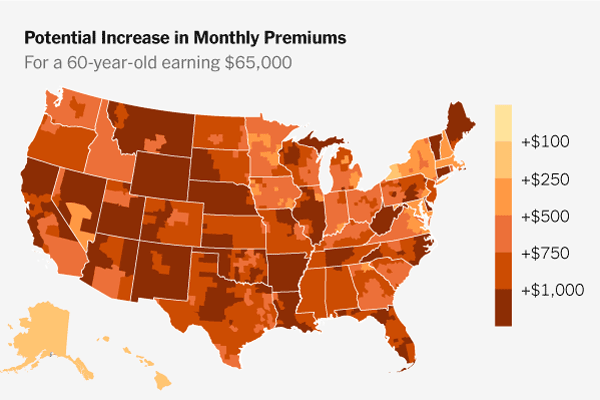
Fraud enforcement is definitely “in fashion” and enforcers are eager to put private duty/home care companies in the color orange! If this a fashion statement you want to make?

To Illustrate:

The National Fraud Enforcement Division of the U.S. Department of Justice (DOJ) recently announced that it has prosecuted 6200 defendants who collectively billed federal health care programs, including Medicaid, TriCare, the VA and others, $45 billion.

In a press release issued on August 4, 2026, the Division stated:

“Home care fraud is everywhere, and the victim is all of us taxpayers. Medicaid claims date and the experience of veteran prosecutors all point to the systematic exploitation of reimbursable home care programs….Today. we sound the alarm on the scale of this fraud by announcing some truly egregious cases, in which numerous people are charged with filing fraudulent claims for caregivers who were not actually providing home care services, but in fact were dead, in prison, or trafficking drugs. This racket ends today.”

And There's More!

“Let today’s announcement be a warning to those engaging in similar activity: if you seek to exploit our health care systems for personal profit, you should expect the FBI and our partners to uncover your scheme and bring it to an end. Every dollar stolen through fraud is a dollar diverted from patient care, and the FBI will continue its work to safeguard the public’s trust and hold accountable those who abuse these vital programs.”

Finally the press release promises that enforcers “…will pursue anybody who seeks to profit at the expenses of American taxpayers, regardless of whether the wrong doing is in the boardroom or in the sickroom.”

In other words, it’s not just the perpetrators who will be punished. The companies, owners and managers will also face punishment.

So, what are some of the offenses pursued so far?

Private Duty Fraud Enforcement

One of the defendants was captured on tape:

”This home health care is the best kept secret…I made a buck plus (each of) the last five years. That’s a half million dollars… ain’t checking on nobody.”

It may be tempting for owners and managers to say: “That’s on them.” Not so! Companies and management will be held accountable for the actions of their employers and contractors.

Private duty/home care companies will see a tsunami of regulation. Use of fraud and abuse prohibitions is just the beginning.

# # #

Elizabeth E. Hogue, Esq The Rowan Report

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2026 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. 

HHAeXchange Launches RCM Services

by Kristin Rowan, Editor

HHAeXchange Announces RCM Services

An Interview with Phil Feldman

In April of 2026, HHAeXchange unveiled their new end-to-end Revenue Cycle Management (RCM) service. HHAeXchange is a leading provider of homecare program management designed for Medicaid Home and Community-Based Services. (HCBS).

Addressing Top Concerns

HHAeXchange’s 2025 Provider Voice Survey asks homecare agencies about the pain points facing the industry. Administrative workload and cost are significant areas of concern for homecare agencies, cited by 41% of providers. RCM services address these concerns by removing administrative tasks from agencies, freeing up personnel to focus on growth, community outreach, referrals, and caregiver training. 

“Homecare providers are navigating diverse payers, rising costs, growing administrative demands, and an increasingly complex financial and regulatory environment. RCM Services relieves agencies of the operational burden of billing and collections while improving cash flow and business performance. By offloading revenue cycle management to experts who deeply understand homecare and the HHAeXchange platform, agencies gain clarity, efficiency, and more time to focus on care.”

Paul Joiner

CEO, HHAeXchange

From Submission to Resolution

End-to-end RCM services handle the full revenue cycle. The RCM Services team at HHAeXchange handles everything from the initial claim submission to handling discrepancies, resolving rejections, appealing denials, and shortening the cycle of aging receivables.

Improved Cash Flow

RCM services go beyond billing and collections. HHAeXchange uses operational intelligence to track denial trends, authorization issues, and payer challenges. With these issues addressed at the beginning, claims are cleaner, denials are reduced, and agencies stay in compliance. These are issues cited by 70% of homecare agencies. 

With improved cashflow, agencies have the resources to grow, to invest in their staff, to scale operations, and to create a more stable work environment.

HHAeXchange RCM Services

Phil Feldman, National Director of RCM

The Rowan Report sat down with Phil Feldman, the National Director of RCM for HHAeXchange. Feldman, and the RCM service platform, came from Sandata and joined HHAeXchange in the acquisition in 2024. We asked Feldman about RCM services: 

The Rowan Report:

What makes HHAeXchange’s RCM different?

Phil Feldman:

The RCM service platform is specific. It is specific to home care, specific to Medicaid, and specific to HHAeXchange. Agencies are connected to resources within the organization. We have existing relationships with payors that we can resolve directly. And the customer-facing team, the experts handling your revenue cycle, are employees of HHAeXchange, not a partner or a 3rd party.

RR:

What is the agency experience with HHAeXchange’s RCM service?

Feldman:

We are currently only offering the RCM services within the HHAeXchange platform. You have one vendor and one platform. When there’s a finger to point, it points right back at us. 

Every account has at least one RCM advisor who serves as the primary point of contact, working with the agency on their billing schedule, their time-keeping week, and the whole process from close to claim.

The intelligence in the platform goes beyond mechanically processing claims and takes a holistic approach. The system checks for demographic descrepancies from intake like member IDs, gender alignment, ID updates from new payors, overservicing on claims, providing services past the end date or outside allotted days. We look directly at the agency’s denial trends and go upstream in the revenue cycle to fix the whole process, not just one claim.

Results

With just under five months since the full launch, and nearly a year of data from beta test agencies, Feldman says their agency claims are in the 90% collection rate. Claim denials, clawbacks, and remit time are trending down. A full data set is forthcoming, but for now, Feldman is relying on anectodal evidence: Their customers are referring agencies that are looking for RCM solutions.

“You’re the best thing ever. I have a lot of friends that I consult with and help them run their business. I want to introduce them to you.”

– An Indiana Agency Owner

Final Thoughts

Hiring and retention issues, reimbursement rates, administrative workload, operational costs, denials, payor compliance, authorizations…these issues are universal across home care and aren’t going away any time soon. If you’re looking for ways to optimize your current workforce, reduce overhead costs and tasks, and create a steady cash flow for your agency, outsourcing RCM is one way to do it. If you’re already an HHAeXchange customer, well, it just makes good sense to work within the system you know, with advisors who take time to understand your agency, and the backing of decades of experience.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com


Justice Department’s Next Target

By Kristin Rowan, Editor

Justice Department's Next Target

New York Sued for Fraud

The past several months, Vice President JD Vance, Dr. Oz, and the anti-fraud task force have investigated home health and hospice agencies suspected of fraud. Much of the focus has been in Minnesota, Georgia, and California. Now, New York joins the list of targeted states, as the Justice Department suis the New York State Department of Health, the state’s Medicaid director, Public Partnerhsips, LLC (PPL), the company operating the $10 billion Consumer Directed Personal Assistance Program (CDPAP) for the state.

CDPAP Management

Prior to the fall of 2024, CDPAP was managed by hundreds of individual agencies. The state opted to consolidate management into one firm and selected PPL. At the time, CDPAP was one of the largest public health benefits programs in the state with more than 250,000 patients.

Justice Department Allegations

Skimming

In the lawsuit, the Justice Department alleges unauthorized profits going to PPL. These profits allegedly come from PPL skimming a percentage of each hour of care billed to Medicaid. The skimmed percentage, according to the suit, amounts to millions of dollars.

Favored Vendor

The Justice Department further alleges PPL was untruthful in its bid regarding its staffing plan, its financial readiness to handle the contract, and the quality of its software, among other aspects of the plan.

Department of Justice New York Fraud

The Department of Justice is blaming New York Governor Kathy Hochul and her administration for allowing the fraud. The DOJ alleges PPL was “preselected” as the winner of the contract in a fixed bid process.

Misrepresentation

The lawsuit further alleges that PPL won the contract after a “sham bid” process. The Justice Department claims PPL intended to stray from the representations made in their bid, that the New York Department of Health learned of the deceit, and failed to hold PPL accountable.

JD Vance Speaks

At a recent campaign event, Vice President JD Vance spoke about the lawsuit.

“You do not want your government facilitating fraud; you want your government fighting against fraud. You know what these fraudsters are doing? They’re taking advantage of American generosity to enrich themselves.”

JD Vance

Vice President of the United States

Response

New York State Department of Health spokesperson Cadence Acquaviva called the lawsuit a “baseless complaint” and an attempt by Republicans to “score political points at the expense of vulnerable New Yorkers.” Acquaviva called the lawsuit “inexcusable and completely lacking in merit.”

The Rowan Report reached out to PPL for comment, but did not hear back as of the publication of this article. We will provide updated information as it becomes available.

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

Private Payors Against Fraud

by Elizabeth E. Hogue, Esq.

Private Payors Against Fraud

Join Enforcement Efforts

There seems to be a persistent myth among providers of private duty/homecare services that the federal anti-kickback statute applies to Medicare-certified providers only. On the contrary, the anti-kickback statute applies to providers who receive funds from any state or federal healthcare program; including the Medicaid Program, VA, TRICARE, etc. Private duty providers: This means many of you! Lately it has become clear that private payors have joined fraud enforcement efforts.

Guilty

In a recent case, a provider in Detroit pled guilty to conspiring to commit health care fraud. The conspiracy resulted in losses totaling $1.9 million to Medicare, Medicaid, and Blue Cross Blue Shield of Michigan. The investigation was conducted by the FBI and the Office of Inspector General of the U.S. Department of Health and Human Services, the primary enforcer of fraud and abuse prohibitions.

Ghost Services

At the plea hearing, the provider admitted to creating and operating a scheme to submit false and fraudulent claims that were medically unnecessary or not actually provided. In some instances, services billed were not ordered by physicians. The scheme continued for over five years. The provider used the proceeds of fraud for his personal use and to benefit others.

Consequences

After a presentence report is prepared, the provider faces a possible maximum sentence of ten years in prison, a fine of up to $250,000 and up to three years of supervised release following any term of imprisonment.

Private Payers Against Fraud

Federal and Private Prosecution

It is important to note that the provider was criminally prosecuted not only for fraud with regard to claims submitted to Medicare and Medicaid Programs, but also fraud committed against a private payor, Blue Cross Blue Shield.

Your Payor Could Report You

It now appears that providers who receive payments from third party payors must be concerned about fraud enforcement. Consequently, providers of private duty/home care services must develop, implement, and update Compliance Programs.

Compliance Programs

Compliance Programs are specific types of documents that routinely address issues that providers do not usually cover in internal policies and procedures. In addition, providers may not gain benefits related to fraud enforcement if there is no formal document called a Compliance Program.

More than Accreditation

Some providers think that accreditation means they are in compliance. On the contrary, providers may be accredited but fail to meet applicable compliance standards for fraud and abuse. Compliance Programs appropriately address potential fraud and abuse issues. They also include mechanisms for helping to ensure compliance, such as processes for identification and correction of potential problems that are not addressed during the certification process.

It Could Save You

Providers also need to know that developing, implementing, and updating Compliance Programs may make a considerable difference during fraud enforcement actions. If providers have Compliance Programs in place that are current and fully implemented, enforcers may be less aggressive in pursuing potential violations.

Corporate Integrity Agreement

When enforcers discover problems with fraud and abuse in organizations, providers are usually asked to develop and implement a Corporate Integrity Agreement (CIA). This type of agreement is likely to include processes for stringent monitoring on a continuous basis. These monitoring activities can be extremely burdensome to providers in terms of both time and money. Providers with valid Compliance Programs are not necessarily asked to develop and implement CIA’s.

Final Thoughts

Now is the time for all providers, including private duty/home care companies, to recognize and act upon the need to establish and maintain Compliance Programs. “Working on it” is no longer good enough.

# # #

Elizabeth E. Hogue, Esq The Rowan Report

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2026 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. 

Medicaid Reform

by Kristin Rowan, Editor

Medicaid Reform

New Efforts to Stop Fraud Before it Happens

As auditors continue to investigate fraudulent activity, new initiatives through Medicare reform aim to stop fraud before it happens. The new initiative, the Combating Deceptive Practices in Assistance Programs Act adds oversight to the Medicaid program.

Preserve Medicaid through Reform

Chairman of the Joint Economic Committee and Chairman of the House Ways and Means Oversight Subcommittee, Rep. David Schweikert, announced the legislation that would tighten eligibility requirements for home health services through Medicaid. The bill requires Medicaid recipients to prove they are unable to perform three or more ADL’s without assistance.

If we seriously want to preserve Medicaid, and provide for the people most in need, we must crack down on fraud. Reaching people that need these services the most should be the top priority of these programs, not growing one of the largest jobs corps in the state. With the U.S. adding almost $87,000 per second to our national debt, making commonsense reforms can save tens of billions of dollars while protecting the truly vulnerable.”

Rep. David Schweikert

Chairman, Joint Economic Committee and House Ways and Means Oversight Subcommittee

Medicaid Waiver Programs

According to the statement from the Joint Economic Committee, the federal waiver programs that allow states to provide at home care for Medicaid beneficiaries are lacking guardrails and oversight. The state policies are “egregious” and lead to waste, fraud, and abuse.

For example, the New York State Medicaid program includes the Consumer Directed Personal Assistance Program (CDPAP) which allows beneficiaries to choose their caregiver. This broad eligibility program allows enrollees to choose friends or family members with no caregiving experience. New York’s Medicaid spending jumped from $2.5 billion in 2019 to more than $9 billion in 2023 with estimates of $12 billion in 2025.

More Information

Read H. R. 7713

Read the accompanying brief from the Joint Economic Committee: From Care to Cash: Correting Misaligned Incentives in Home Health

# # #

Kristin Rowan Editor The Rowan Report

Kristin Rowan is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news. She is also a sought-after speaker on Artificial Intelligence, Technology Adoption and Lone Worker Safety. She is available to speak at state and national conferences as well as software user-group meetings.

Kristin also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing. She works with care at home software providers to create dynamic content that increases conversions for direct e-mail, social media, and websites.  Connect with Kristin directly at kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com


Fraud and Abuse Misunderstandings

by Elizabeth E. Hogue, Esq.

Medicare and Medicaid Fraud and Abuse

Common Misunderstandings

Providers are generally familiar with prohibitions against fraud and abuse in the Medicare and Medicaid Programs, including Medicaid waiver programs, and other state and federal health care programs, such as the VA and TriCare. Private insurers now often enforce the same prohibitions applicable to federal and state programs. But there are at least two common misconceptions about fraud and abuse.

Intent

Enforcers must prove intent in order to show that providers engaged in fraud, but providers may not understand what the government can use to show “intent.”

Premeditation

Many providers seem to think that the only way to show intent is to prove that they sat down at their desks on a Monday morning and decided to commit fraud, but court decisions tell a very different story! They say that if enforcers can prove that providers knew or should have known of a pattern of fraudulent conduct, enforcers may conclude that providers had intent. Other court decisions say that when providers show reckless disregard for a pattern of fraudulent conduct regulators can show intent necessary to prove fraud.

When providers grasp these crucial standards, it is clear that they must become vigilant to prevent patterns of fraud and abuse. This is necessary in order to prevent government enforcers from concluding that they had intent necessary to prove fraud and/or abuse.

Personal Responsibility

Many providers also may not understand that every provider, regardless of position, is personally responsible for fraud and abuse compliance.

It Rests on You

It is extremely tempting to think that fraud and abuse compliance is management’s responsibility, or the exclusive job of the Administrator/Chief Executive Officer or the organization’s Compliance Officer. On the contrary, the Office of the Inspector General (OIG) of the U.S. Department of Health and Human Services, the primary enforcer of fraud and abuse prohibitions, is quite clear that every practitioner has personal, individual responsibility for fraud and abuse compliance. 

The problem of fraud and abuse will never be solved until every practitioner takes individual responsibility for it. Enforcement action is often taken against individual practitioners, as well as members of management and owners.

Fraud and Abuse Personal Responsibility

Complete Compliance

When providers understand these two basic points, they are well along the road to active participation in fraud and abuse compliance efforts.

Final Thoughts

Providers must remember that fraud and abuse compliance is now a permanent part of the health care landscape across the nation. Compliance is not a fad that will blow over or disappear! Providers must be prepared to actively work to prevent or correct fraud and abuse for as long as they work in the healthcare industry.

# # #

Elizabeth E. Hogue, Esq The Rowan Report

Elizabeth Hogue is an attorney in private practice with extensive experience in health care. She represents clients across the U.S., including professional associations, managed care providers, hospitals, long-term care facilities, home health agencies, durable medical equipment companies, and hospices.

©2026 Elizabeth E. Hogue, Esq. All rights reserved.
No portion of this material may be reproduced in any form without the advance written permission of the author.

©2026 by The Rowan Report, Peoria, AZ. All rights reserved. 

CMS Proposed Changes

by Kristin Rowan, Editor

CMS is Making Changes

Good or Bad?

CMS is making changes across Medicare and Medicare Advantage. From Star Ratings to Prescription Drug Prices to the Hospice benefit, CMS is embracing Make America Healthy Again. Will these initiatives benefit Medicare and Medicare Advantage recipients or the insurance companies who provide the plans?

Drug Payment Model

In early November, CMS announced a plan to lower prescription drug costs for Medicaid recipients. State Medicaid programs can opt in to the GENErating cost Reductions fOr U.S. Medicaid Model (GENEROUS). The pilot program is using the most-favored-nation pricing that was recently negotiated and announced by President Trump. Most-favored-nation pricing requires prescription drug manufacturers to charge the same low rate paid in other countries.

Limited Pilot

Beginning in 2026, CMS will negotiate with manufacturers of select drugs for lower pricing. Participating states will start using uniform, transparent coverage criteria. This is not criteria for inital coverage in Medicaid, but for standardizing access to high-cost medications.

Manufacturers are not required to participate in the GENEROUS Model, but can voluntarily apply. Participating manufacturers agree NOT to seek additional supplemental rebates or discounts outside the model price.

New Medicare Advantage Policies

CMS has proposed updates to the Medicare Advantage and Medicare Part D programs. The new plan would begin in CY 2027 and includes major changes to the Star Ratings system. CMS is also seeking feedback on new ways to modernize MA. 

Star Rating Changes

The proposed changes are supposed to incentivize plans to improve care. CMS suggests removing 12 unique measures that look at administrative processes and those that don’t highlight differences between plans. Star Rating measurements of care, outcomes, and patient experience will remain. 

Request for Feedback

CMS is seeking feedback on Medicare Advantage changes, including improving competition, refining risk adjustment, and aligning quality incentives to deliver greater value. CMS is open to either a limited model test or program-wide changes. Interested parties can submit feedback through January 26, 2026. Read the Proposed Rule here. Submit your comments.

Expanding Technology-Enabled Care

CMS may finally be recognizing what we’ve been promoting for 25 years: Care improves with technology support. 

CMS Proposed Changes<br />
Technology-based Care

The ACCESS model tests a new payment approach in original Medicare to expand access to technology-supported care options. CMS aims to increase technology-supported care options to improve health and prevent and manage chronic diseases. More than two-thirds of Medicare beneficiaries are dealing with high blood pressure, diabetes, chronic musculoskeletal pain, and depression.

An interest form is now available for the 10-year Advancing Chronic Care with Effective, Scalable Solutions (ACCESS) Model test. The model test begins July 1, 2026. The application to participate must be received by April 1, 2026.

Impact

As these programs roll out between now and 2029, the impact on insurance plans, payors, beneficiaries, and taxpayers will unfold. Will lower cost prescriptions and technology-based care lower insurance rates? Payor reform may be necessary to change out-of-pocket costs. Regulations may have to further incentivize payors to increase care when costs go down, particularly with value-based care models. 

Please take a few minutes to read the details on each of these proposals, add your comments, and sign up to participate. The industry needs reform and our aging family members deserve better.

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Alliance to Congress: STOP CUTS

by Kristin Rowan, Editor

9% Cut Proposed

CMS proposed home health rule for 2026 includes disastrous cuts. A 3.2% market basket increase, a 0.8% productivity cut, a 5% reduction to recoup prior overpayments, and a 4.1% permanent reduction to prevent further overpayments. CMS proposed an additional 0.5% cut to account for high-risk outliers. In other words, CMS wants to pay less for all patients to make up for the small percentage of patients who need more care.

Deadline Looming

The mandatory comment period ended on August 29. Next, CMS reviews the submitted comments, responds to those comments (generally explaining why they are not going to listen), and then finalizes the 2026 rule. The final rule is due November 1, 2025. Although, that falls on a Saturday, so the deadline may extend to Monday. A good many of us will be in New Orleans for the Alliance annual conference and expo by then.

Group Effort

The National Alliance for Care at Home (Alliance) joined 150+ provider, patient, community, and advocacy groups to write a letter to Congress urging them to prevent the CMS proposed cut.

“The proposed payment reductions for home health pose a serious threat to the health and safety of Medicare beneficiaries and to the broader integrity of our healthcare system. With the 2026 payment rule under review and due by November 1, we urge you to promptly intervene and press CMS to stop the cuts and realign payments.”

Pattern of Payment Reduction

The letter, addressed to Senate Majority Leader John Thune, Senate Minority Leader Chuck Schumer, Speaker Mike Johnson, and House Minority Leader Hakeem Jeffries, asks Congress to look at the consecutive years of pay reductions and how they have impacted home health. Because of the cuts, agencies have gone out of business or downsized, leaving rural areas without care.

Home Health Costs Less

The letter also explains that cutting medicare payments actually costs more. When more patients have access to home health, CMS spends less on unplanned hospital visits and ER trips. Patients have fewer falls and accidents. Risk factors are identified earlier and preventative treatments are used before a patient’s condition requires hospitalization. Home health patients stay home years longer than those not receiving home health before entering a skilled nursing or assisted living facility. 

What's at Risk

The Medicare Trust Fund, funded partially by payroll taxes, includes hospital insurance that pays for hospital (Medicare Part A) services. When these costs increase, the trust fund is at risk being insolvent and taxes are increased to put money back into the fund. Lowering home health payment rates and cutting off millions of people who depend on home health will impact tax payers as well.

CMS home health payment cuts
“The cuts currently proposed to Medicare’s home health benefit are unsustainable and would be deeply harmful to those who depend on care at home. The Alliance will continue to work with policymakers and our stakeholder allies to oppose these harmful cuts and protect access to home health services for millions of older adults, individuals with disabilities, and their families.”
Dr. Steve Landers

CEO, National Alliance for Care at Home

The Alliance issued a press release with the highlights from the letter. You can read the full letter here.

# # #

Kristin Rowan, Editor
Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Government Shutdown

by Kristin Rowan, Editor

Government Shutdown Threatens Care at Home

Lawmakers on opposite sides of the aisle failed to come to a budget agreement by the deadline. This causes an immediate cease to all non-essential government functions and many government employees aren’t being paid. 

UPDATE: Shutdown, Day 16

–As of October 16, 2025–

What it Means for Care at Home

After 10 attempts, the government is no closer to an agreement than they were on September 30th. The Senate is expected to break at the end of the day, leaving the next opportunity to negotiate until at least Monday. 

Telehealth

The biggest impact on care at home during the government shut down is the ability to complete required face-to-face visits using telehealth appointments. Both home health and hospice have employed telehealth for face-to-face encounters since the COVID-era waiver, which has now been extended several times. The most recent extension, which we anticipated Congress to extend in this budget, expired on September 30th.

All face-to-face encounters occurring after October 1, 2025 must be in person.

According to home health expert Melinda A. Gaboury of Healthcare Provider Solutions says it is unlikely an extension would be retroactive even if Congress includes an extension in the finalized budget.

Payments

Conflicting information on Medicare payments leave us unsure of the actual impact. Some reports say there will be no delay while others mention 10-day holds. It is unclear whether this is in addition to the standard 14-day hold. Either way, we are anticipating (and hoping for) minimal payment disruptions.

Surveys

Initial Medicare certification for home health and hospice as well as recertifications will be delayed. If ACHA, CHAP, or another accrediting body is conducting your survey, however, there should be no delay. These accrediting bodies are continuing without interruption. State agency surbveys will be delayed until after the budget is finalized and the shutdown ends.

Look for continued updates from The Rowan Report as the shutdown and negotiations continue.

–As of October 9, 2025–

The Disagreement

Reporters and spokespoeople from both sides of the debate have suggested various reasons for the shutdown. Equally, both sides claim they are not the holdouts. What we do know for sure is that one of the primary points of contention is the continuation of subsidies for Affordable Care Act Marketplace Insurance plans. One group wants an extension written into the current budget while the other says it’s not necessary since the subsidies currently run through the end of the calendar year.

Push to Extend

The lawmakers who are pushing to get the subsidy issue resolved believe that marketplace users are not going to sign up for insurance in November and do it again in January when the subsidies are fixed. Instead, insurance commissioners warn that without the subsidies, many people will opt not to have insurance at all and others will select substandard plans based on affordability. They will be priced out of the plans they want without the subsidies in place.

Priced Out

In 2025, even with the subsidies, the average family was paying $800 per month on health insurance through the marketplace. When the subsidies expire, those same families will see their existing plan rates jump to $3,000 per month. KFF, the nonpartisan health research organization, estimates that most users will have a 114% rate increase. 

Government Shutdown

Photo Credit – The New York Times

Counter

According to ND insurance commissioner Jon Godfread, lawmakers who oppose the subsidies are actually opposing the cost of health care and insurance across the board. They insist the subsidies aren’t necessary if healthcare and insurance costs drop instead. Proponents of the subsidies agree, but say that is a longer discussion that will take a lot of time to resolve and the subsidies provide an immediate solution to a bigger problem. They are urging the holdouts to include the subsidies in the budget and tackle the rising cost of healthcare later.

Open Enrollment

The clock is ticking. Open enrollment for 2026 begins November first in every state except Idaho, where open enrollment starts next week. Insurers have already locked in their 2026 premium rates, which will likely cause sticker shock for most marketplace users. Most insurers have prepared subsidy and non-subsidy rates, but without the extension, we will only see the much higher non-subsidy rates. These rates are unlikely to change before enrollment starts and the only hope for marketplace buyers is for Congress to extend the subsidies.

Home Health & Hospice

Care at Home Impact

There are several ways in which the shutdown and the loss of the subsidy may impact care at home.

Payment delays are the most pressing risk. Government officials have promised no delay for some essential services like SNAP and WIC. It is likely Medicare and Medicaid payments will be delayed. While those payments will come through eventually, care at home agencies have to operate without payment or hope the

payers will process payments locally while waiting on the government to reopen. The longer the shutdown lasts, the more likely it is that payments will be delayed. The 6th Senate budget vote failed today, sending the shutdown to day 8.

The longer term impact for care at home will come if the subsidies are not renewed. If insurance rates increase by more than 100% on November 1, users will opt for lower priced coverage, which may no longer include care at home benefits. Fewer patients seeking care at home means less money for agencies. Long-term, it also means higher hospital and ER usage and costs, which increases government spending and usually leads to additional care at home cuts to offset the costs.

National Alliance for Care at Home has identifed current and potential implications of the shutdown. Read their analysis here.

This is an ongoing story and we will continue to provide additional information as it happens. 

# # #

Kristin Rowan, Editor

Kristin Rowan has been working at The Rowan Report since 2008. She is the owner and Editor-in-chief of The Rowan Report, the industry’s most trusted source for care at home news, and speaker on Artificial Intelligence and Lone Worker Safety and state and national conferences.

She also runs Girard Marketing Group, a multi-faceted boutique marketing firm specializing in content creation, social media management, and event marketing.  Connect with Kristin directly kristin@girardmarketinggroup.com or www.girardmarketinggroup.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com

 

Can This New Software Eliminate Fraud and Billing Errors?

by Tim Rowan, Editor Emeritus

Software Eliminates Fraud and Errors

Like so many Home Care providers, Aspen Home Care in Kansas City, Missouri was drowning in paper. Two hundred caregivers turned in weekly timesheets every Friday. A large office staff had to go through them, looking for errors, omissions, and unauthorized visits and shifts. Submitting erroneous claims, of course, leads to payment denials, even fines. When an agency submits too many bad claims every week over a long period, a surveyor will soon be knocking at their door.

The Hurdles

On a good week, Aspen completed all necessary payroll and billing tasks and had bills ready to submit by end of business on the following Thursday. Slowing down the process were the usual errors — forgotten check-outs, more hours worked than authorized, and late timesheet submission. Caregivers grew weary of the weekly phone calls asking for clarification, even when the error was their fault. Aspen did have a basic billing system, but paper timesheets fed it too. Electronic Visit Verification was possible, but only via a patient’s landline, using punched-in identification codes.

Then... the call came

“After years of software design, we have completed our replacement for your billing and EVV system. We would like you to switch from the basic system we sold you a few years ago and beta test our better one.”

– Henry (Hank) Schwab, Owner, Compliance Plus

Beta testing is a risky venture, but both owner Ahmed Jara and Office Manager Mohammed Mohammed* trusted Hank and agreed to give it a try. After all, the agency was drowning in paper, they reminded each other.

Dramatic Process Improvements

We took part in a demo of the Compliance Plus system before speaking with Mohammed and hearing Aspen’s experience. We saw a comprehensive, user-friendly system, with a color-coded user interface, that includes scheduling, EVV, and billing for Medicaid, Managed Care, and all other payers an agency contracts with.

Time Tracking

Caregivers clock in and out with an app that is GPS-enabled down to exact longitude and latitude coordinates. Should a patient live in an internet dead zone, caregivers can use their landline. If there is no landline, Aspen will install a “smart fob” in the home. Aspen does not require specific visit start times, but once a check-in is recorded, the app knows the patient’s authorized hours and automatically alerts the caregiver when it is time to clock out.

Verification

Mistakes do happen, of course, but fixing them is not difficult. When the Compliance Plus back end sees a 14-hour visit, it assumes the caregiver forgot to check out. The visit flashes red on the screen, indicating it is not ready to bill, and displays the difference between authorized and recorded hours. The office employee managing exceptions simply calls the caregiver for verification and then manually edits the end time, and compliance is maintained.

Caregiver Feedback

Mohammed told us his caregiving staff is thrilled with the app, though he did say the transition was hard at first. “They learn to use it in about 30 minutes,” he said. “Check-in and check-in take a few seconds and now they are happy to be done with paper forever, not to mention no longer having to deliver paper timesheets to the office.” He added that fake check-ins from the car on the way to a patient’s home have been completely eliminated.

Most importantly, the three-person office staff now completes payroll and billing for 200 caregivers by midday on Tuesday instead of late on Thursday.

The "Plus" of Compliance Plus

Certainly, procedural efficiencies are important, and many scheduling and EVV systems force caregivers to check in and check out in the presence of the patient and alert office staff when a caregiver arrives late or is a no-show. What we saw during our demo, however, we have not seen elsewhere. Compliance Plus automates the tedious task of rooting out EVV, billing, and payroll errors so efficiently, payment denials, aggregator rejections, and incorrect paychecks are virtually eliminated.

Denials are Rare

Mohammed confirmed what we saw in the demo. The file that includes hours, authorizations, patient demographics, and pre-arranged pay rates is prepared and perfected in advance. Then, the system uploads the same corrected file to the aggregator and to state and other payers. “If we need to fix hours or a bill, we do it before uploading to all entities,” he said. “We rarely get rejections from the aggregator or denials from payers.”

Aggregated Data

One of the requirements of payers and EVV aggregators is that all patient and caregiver names and other information must be in their respective databases in advance. Compliance Plus finds missing data and removes a bill from the file before it is uploaded, notifying the user with a red flag. Mohammed added, “We have to make sure all patient data is in system, but that is easy to do.”

Implementation and Training

In every home care agency, there is always a measure of trepidation among the staff when switching from familiar paper to automation. Aspen Home Care was no different when owner Ahmed Jara announced that he had accepted Hank’s invitation to join a beta test. Mohammed told us that his staff’s time from implementation to software expertise took a little less than three months. Compliance Plus customer relationship manager Sara Moore conducted online training of key office staff, a service that is included in Aspen’s monthly fee. Mohammed and a couple others trained the rest of the staff on the full system and then caregivers on the use of the app.

“After a short while, the new system became our normal workflow,” Mohammed commented. “The only speed bump is when they upload new features. We need to spend a little time learning them, but ultimately, the new features improve our workflow. Our caregivers pick up the app in about 30 minutes, including new hires.”

Favorite Features

He added that his 200 caregivers like checking in and out on the app better than the legacy ANI system, which used the patient’s landline for automatic number identification. “English is a second language for some of our caregivers, and they sometimes had trouble with the ANI prompts spoken by the computerized voice,” he explained. “GPS verification is the best feature. If a caregiver checks in from too far away, we see their distance from the patient’s home on a map, and we gently ‘re-educated’ them and it does not happen again. In the past, they would sometimes get away with asking a family member to check in for them from the patient’s landline. Those days are gone.”

He also told us that Aspen does not insist on specific start times. What matters is that visit length matches authorized hours over a billing period. This is especially helpful for waiver and HCBS plans when the caregiver lives in the home. In those arrangements, checking in or out used to be easily forgotten. “I take care of her all day, how do I know when I start and stop?” The Compliance Plus app rings its cell phone loudly to remind visiting and live-in caregivers to check in and then to check out after the authorized number of hours have been reached.

Simplifying Complex Billing

Presently, Aspen exclusively serves Medicaid beneficiaries, though that can mean several managed care payers. With varying reimbursement rates from payers, combined with different caregiver hourly rates, getting a bill to match an authorization used to be a challenge for Office Manager Mohammed and his team.

It's Complicated

In the case of an agency employed family caregiver, there are often days when the family member will spend one hour toileting and feeding, the next hour doing reimbursable homemaking chores, and the third hour running care-related errands. Not only might those tasks be paid at different rates, but they can, and often are, reimbursed by different payers.

Patient Profiles

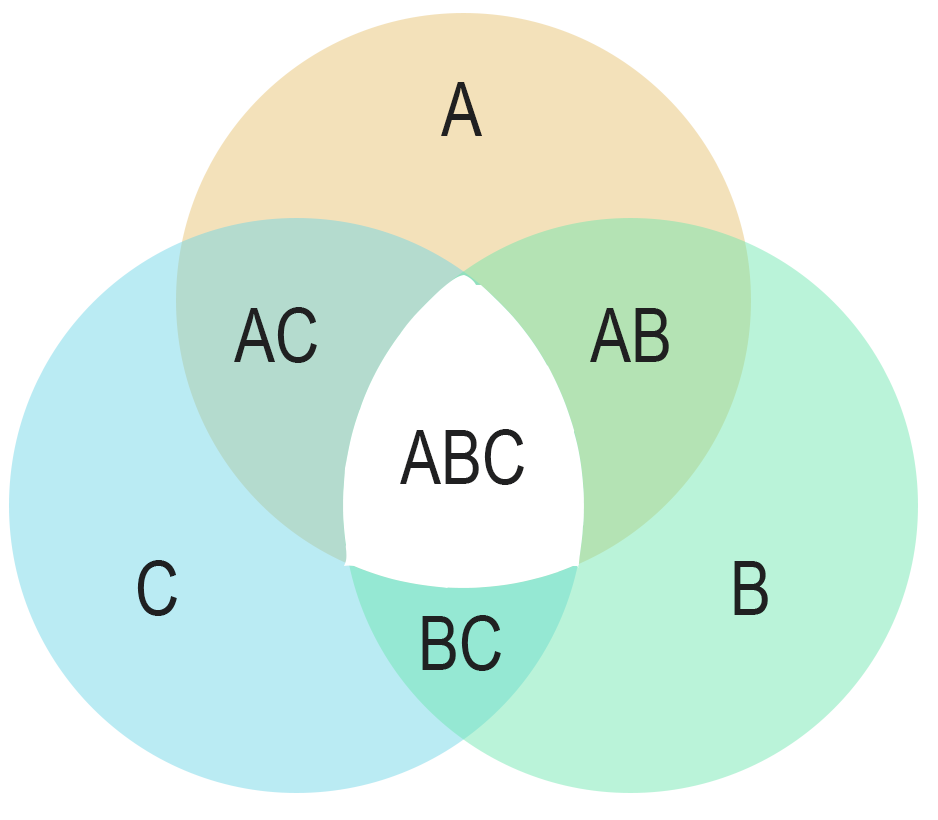
Mohammed emphasized that the way Compliance Plus handles these situations saves considerable time and reduces payer and aggregator rejections. Like in a Venn diagram, every combination of patient, payer, task type, and caregiver creates a “patient profile.” The user created most profiles in advance, based on known payer rates, etc. Occasionally, a patient’s profile is unique, but a user can easily enter the specifics into the system manually. Once a profile is built, the system calculates all of the billing accurately without additional user supervision.

Compliance Plus

Task Rates

If a payer’s rate for a task changes, Mohammed or another office staffer makes the change one time for all affected patients. In that scenario where the live-in caregiver performs three different tasks in one day, he or she checks in and out only once, before the first task and after the last, and designates each task performed. Compliance Plus does the rest.

Company Prospects

Hank Schwab told us that he is confident, after 100 successful beta customers, that Compliance Plus is ready for general release. At $10 to $12 per patient per month, he believes that supplementing word-of-mouth with a modest marketing effort will help him replace paper and strengthen the bottom line for many Medicaid and Personal Care agencies. Hank’s plan is to begin that effort as soon as he identifies an investor or two and hires a marketing director. “I already manage a team of coders and personally pay all the bills,” he laughed. “I’m ready for someone else to take on a few of my jobs.”
https://complianceplus.com/

*No, that is not a typo. We also enjoyed Mohammed Mohammed’s sense of humor. He tells people his parents were too cheap to give him a first name, so they just copied his last name.

# # #

Tim Rowan The Rowan Report
Tim Rowan is a 30-year home care technology consultant who co-founded and served as Editor and principal writer of this publication for 25 years. He continues to occasionally contribute news and analysis articles under The Rowan Report’s new ownership. He also continues to work part-time as a Home Care recruiting and retention consultant. More information: RowanResources.com
Tim@RowanResources.com

©2025 by The Rowan Report, Peoria, AZ. All rights reserved. This article originally appeared in The Rowan Report. One copy may be printed for personal use: further reproduction by permission only. editor@therowanreport.com